The History of Vision Therapy: Orthoptics to VR
Parents often assume vision therapy is new, or that it appeared alongside computers and headsets. It is much older than that. The techniques we use in our Coconut Creek, Boynton Beach and West Palm Beach offices sit at the end of a century-long chain. Eye training began inside hospital ophthalmology, was widened by optometry, and has since been put through a generation of clinical trials that both supported it and set limits on it.
That history is worth knowing, because it explains why you can read one professional body saying vision therapy works and another saying it does not.
Key takeaways
- Modern vision therapy grew out of orthoptics, the eye-training discipline that took shape in ophthalmology clinics in the first half of the twentieth century (Helveston, 2005).
- Optometry expanded the scope, applying visual training well beyond binocular function to uncomfortable vision, reading and academic performance (Helveston, 2005). That expansion is where the professional disagreement begins.
- Frederick Brock applied stereopsis to the diagnosis and treatment of binocular dysfunction (Wittenberg, 1981). The string that carries his name is still in use in our therapy rooms.
- The turning point for our field came in 2008, with the Convergence Insufficiency Treatment Trial (CITT Study Group, 2008); its 2019 follow-up delivered results in both directions (CITT-ART, 2019).
- Digital and virtual reality tools are promising, not proven replacements for established treatment (Pineles et al., 2020).
The nineteenth century made the eye examinable
Before anyone could train binocular vision, they had to be able to see inside the eye and measure how it worked. Helmholtz introduced the ophthalmoscope in 1851, which for the first time let a clinician observe light reflected back from the retina (Berendschot et al., 2003). Instruments for measuring eye alignment, fusion and depth perception followed.
 Helmholtz’s ophthalmoscope, 1851
Some form of visual training has been used for centuries, but the organized, professional version of it is much younger: it took shape in the first half of the twentieth century (Helveston, 2005).
Orthoptics: eye training becomes a profession
The first organized discipline was orthoptics. In the first half of the twentieth century, orthoptists introduced a wide range of training techniques aimed mainly at improving binocular function (Helveston, 2005). Mary Maddox, daughter of the ophthalmologist Ernest Maddox, is generally credited with establishing orthoptics as a distinct healthcare discipline, and founded the first orthoptic clinic at the Royal Westminster Ophthalmic Hospital in London in 1928 (British and Irish Orthoptic Society).
Orthoptics was hospital-based, worked under ophthalmologists, and concentrated on strabismus and fusion. Much of what a therapy room still contains — instruments that show each eye a different image, targets that force the two eyes to work as a pair — descends directly from that era.
One correction is worth making here, because it appears in a lot of online summaries. You will sometimes read that vision therapy began with William H. Bates. We do not tell the story that way, and none of the histories we cite here support it: the procedures in a modern optometric program come from clinical orthoptics and from the optometry of the second half of the twentieth century (Helveston, 2005).
Optometry widens the scope
The other half of the story starts in the same year as Mary Maddox’s clinic. The Optometric Extension Program Foundation says it was founded in 1928 by A.M. Skeffington — whom it calls the father of behavioral optometry — and E.B. Alexander (OEPF).
 A.M. Skeffington
Over the following decades, optometrists and other practitioners took visual training well beyond binocular dysfunction and applied it to a much wider range of conditions (Helveston, 2005). By 2002, a review could describe optometric vision therapy as an established treatment for non-strabismic accommodative and vergence disorders “for nearly 75 years,” argued largely from objective recordings of eye movement and focusing (Ciuffreda, 2002). That review was written by a proponent of the field, and it is fair to read it as an argument rather than a neutral audit.
This is the fork in the road. Ophthalmology largely stayed with the narrow orthoptic use; optometry built a broader discipline. The disagreement you can still read today dates from this period, not from anything recent. If you want the plain-English version of what a program actually involves, start with what vision therapy is.
Brock, and his string
Frederick Brock is one of the few individual clinicians whose name survives in everyday practice. His contribution was to apply stereopsis — depth perception built from two slightly different images — to the diagnosis and treatment of binocular dysfunction (Wittenberg, 1981).
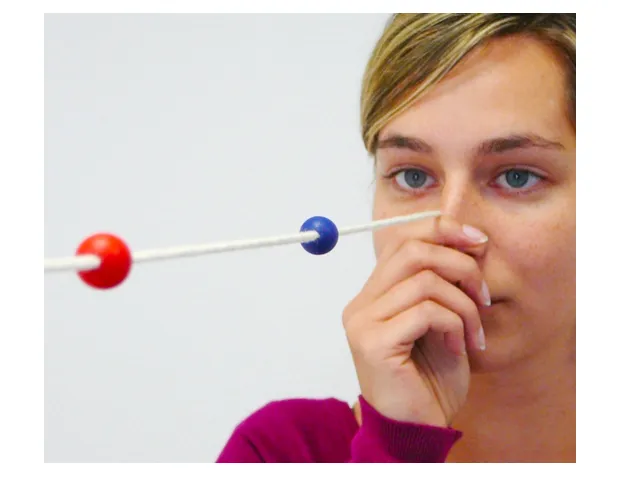 A Brock string
The Brock string is deliberately low-tech. A cord, a few beads, and immediate feedback: when both eyes point at the same bead, the patient sees two strings crossing at it. It is also still being tested. A 2025 randomized trial in 50 patients aged 11 to 30 found that home Brock string exercises after concussion improved near point of convergence by 8.9 cm compared with 3.8 cm under usual care (Trbovich et al., 2025). That trial was small, single-blind, short, and measured the clinical sign rather than symptoms or return to school — but it is a real controlled test of one of the simplest tools in the room. More on the man and the method in who is Brock and why does he string.
The trial era, 2008 onward
The modern chapter of this history is not a device. It is a set of randomized controlled trials.
The Convergence Insufficiency Treatment Trial changed the conversation in 2008. In 221 children aged 9 to 17 with symptomatic convergence insufficiency, 73% were successful or improved after 12 weeks of office-based vergence and accommodative therapy, against 35% with office-based placebo therapy, 43% with pencil push-ups and 33% with home computer therapy (CITT Study Group, 2008). A Cochrane network meta-analysis of 12 trials and 1,289 participants later confirmed the advantage over placebo in children (Scheiman et al., 2020).
 Vectogram work, a standard office-based eye-teaming activity
The follow-up trial is the part that honest histories have to include. CITT-ART, reported in 2019, found that clinical signs improved more with therapy than with placebo — near point of convergence 10.4 versus 6.2 cm, fusional vergence 23.2 versus 8.8 prism diopters — but symptom scores improved about the same in both groups (CITT-ART, 2019). A companion paper found reading comprehension improved 3.7 points with therapy and 3.8 points with placebo, meaning the therapy was no better than placebo for reading (CITT-ART, 2019).
Amblyopia followed a parallel path through the Pediatric Eye Disease Investigator Group, and that work still shapes the amblyopia and strabismus care we plan today. Its 2002 trial in 419 children showed patching and atropine performing similarly, at 3.16 versus 2.84 lines of improvement, and established both as appropriate first-line treatments (PEDIG, 2002). We summarize the whole picture in does vision therapy work: an honest evidence summary and go trial by trial in what the CITT and CITT-ART trials actually found.
The critics, and what they got right
Two positions have run alongside each other for decades, and both belong in this history.
Pediatrics and ophthalmology hold that dyslexia is a language-based disorder, that vision problems can interfere with learning but do not cause it, and that eye exercises, behavioral vision therapy and tinted lenses are not supported for treating learning disabilities (AAP/AAO/AAPOS/AACO, 2009), a position reaffirmed in 2014. Writing in 2005, Helveston concluded that apart from near point of convergence exercises, visual training lacked documented evidence of effectiveness for ophthalmologists (Helveston, 2005).
Optometry’s position, stated jointly in 1997, is that vision problems can and often do interfere with learning, and that optometric care aims to improve visual function as one part of a multidisciplinary approach (AAO/AOA, 1997).
A 2009 review took the middle route and is, in our view, the fairest summary of where things stood. It found reasonable evidence for treating convergence insufficiency, for yoked prisms in neurological patients and for vision rehabilitation after brain injury. Most other behavioral approaches were not evidence-based, largely because the controlled trials had not been done (Barrett, 2009).
Our clinical perspective at Vision & Learning Center is that the critics were right about the claims that outran the data, and that the correct response was the one the field took after 2008: run the trials. Vision therapy is not a treatment for dyslexia or ADHD. In our hands it is aimed at measurable problems with eye teaming and focusing — the two areas where the controlled evidence is strongest (CITT Study Group, 2008; Scheiman et al., 2020) — some of which make reading uncomfortable.
Screens, games and headsets
The newest chapter is digital, and its results are genuinely mixed.
A large trial in children aged 5 to 12 found a binocular iPad game less effective than part-time patching, with only 22% of the game group completing more than three-quarters of the prescribed play (Holmes et al., 2016). A companion trial in 13- to 16-year-olds found the game no better than patching, and possibly worse, with adherence of 13% (Manh et al., 2018). The BRAVO trial found an active binocular game no better than a placebo game (Gao et al., 2018). Reviewing 20 studies, the American Academy of Ophthalmology concluded there was no level I evidence for binocular treatment as a substitute for patching or glasses (Pineles et al., 2020).
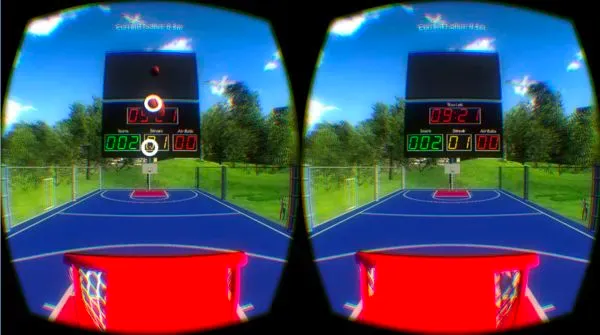 Virtual reality dichoptic training
Then the picture improved. A 2022 pivotal trial of a dichoptic digital therapeutic in 105 children aged 4 to 7 showed 1.8 lines of improvement versus 0.8 lines with glasses alone — although the comparator was glasses, not patching (Xiao et al., 2022). In adults, a small uncontrolled study of VR dichoptic training with a headset reported improvements in acuity and stereoacuity after eight sessions, and the authors called for controlled trials (Ziak et al., 2017).
That is the honest state of the art: a promising delivery system, not a replacement for established treatment. We use these tools inside a program, alongside lenses, prisms and hands-on procedures. More on how we use them in the virtual reality revolution in vision therapy.
What a century of history suggests
The pattern is consistent. Techniques were invented in clinic, spread faster than the evidence, and were then narrowed and confirmed by trials. The parts that survived testing — office-based therapy for symptomatic convergence insufficiency, established amblyopia treatment, targeted work after brain injury — are the parts we lean on hardest, and we try to be as clear about the limits as about the results.
If reading, focus or eye strain is a problem for someone in your family, the useful next step is measurement, not history. A full evaluation is what tells us whether vision therapy is the right tool, and which parts of it. Schedule an evaluation or read what a comprehensive and developmental eye examination involves, and we will tell you what we find.
Common Questions About This Topic
Who invented vision therapy?
No single person did. Organized eye training grew out of orthoptics, which took shape in ophthalmology clinics in the first half of the twentieth century, and optometry then expanded it beyond strabismus into focusing, eye teaming and a much wider range of complaints. Individual clinicians such as Frederick Brock shaped how binocular problems came to be assessed and treated.
Did William H. Bates start vision therapy?
You will see that claim online. We do not tell the story that way, and none of the histories we cite here support it. The procedures used in a modern optometric program descend from clinical orthoptics, which took shape in ophthalmology clinics in the first half of the twentieth century, and from mid-century optometry.
What is the Brock string, and is it still used?
It is a string with colored beads, named for Frederick Brock, that gives a patient direct feedback about where their two eyes are pointing. Yes - we still use it in our offices, and it is still being studied. A 2025 randomized trial of home Brock string exercises after concussion improved near point of convergence more than usual care, although the trial was small and measured the clinical sign rather than symptoms.
When did vision therapy start being tested in clinical trials?
Controlled trials existed earlier, but the turning point for our field was the Convergence Insufficiency Treatment Trial in 2008, which compared office-based therapy with placebo therapy in 221 children. Its follow-up, CITT-ART, reported in 2019 and produced both positive and negative results.
Do virtual reality and video games replace traditional vision therapy?
Not on the current evidence. Binocular and dichoptic games have shown mixed results in large trials, and the American Academy of Ophthalmology concluded in 2020 that binocular treatment cannot substitute for patching or glasses in amblyopia. We use digital tools as part of a program, not as the whole of it.
Where This Information Comes From
- Helveston EM (2005). Visual training: current status in ophthalmology. American Journal of Ophthalmology, 140(5), 903-910. : Traces visual training to orthoptists in the first half of the twentieth century and its later expansion by optometrists; states that ophthalmology's consensus is that, apart from near point of convergence exercises, visual training lacks documented evidence of effectiveness.
- British and Irish Orthoptic Society. History of Orthoptics. : Credits Mary Maddox with establishing orthoptics as a distinct discipline and dates the first orthoptic clinic to 1928 at the Royal Westminster Ophthalmic Hospital, London.
- Berendschot TTJM, DeLint PJ, van Norren D (2003). Fundus reflectance - historical and present ideas. Progress in Retinal and Eye Research, 22(2), 171-200. : States that Helmholtz introduced the ophthalmoscope in 1851, allowing observation of light reflected from the fundus.
- Optometric Extension Program Foundation. About OEPF. : The foundation states it was founded in 1928 by A.M. Skeffington - whom it calls the father of behavioral optometry - and E.B. Alexander.
- Ciuffreda KJ (2002). The scientific basis for and efficacy of optometric vision therapy in nonstrabismic accommodative and vergence disorders. Optometry, 73(12), 735-762. : A proponent's narrative review stating that optometric vision therapy has been used for accommodative and vergence disorders for nearly 75 years, argued from objective oculomotor recordings.
- Wittenberg S (1981). Brock's research in stereopsis. American Journal of Optometry and Physiological Optics, 58(8), 663-666. : Reviews Frederick Brock's contributions to vision training, centered on applying stereopsis to the diagnosis and therapy of binocular dysfunction.
- Trbovich AM, Zynda AJ, Togashi T, et al. (2025). Randomized Controlled Trial of Brock String Vision Therapy for Receded Near Point of Convergence Following Concussion. Journal of Neurotrauma, 42(19-20), 1708-1718. : In 50 patients aged 11-30, home Brock string exercises improved near point of convergence by 8.9 cm versus 3.8 cm with usual care; small, single-blind, short follow-up, and the outcome was the clinical sign rather than symptoms.
- Convergence Insufficiency Treatment Trial Study Group (2008). Randomized clinical trial of treatments for symptomatic convergence insufficiency in children. Archives of Ophthalmology, 126(10), 1336-1349. : In 221 children aged 9-17, 73% were successful or improved after 12 weeks of office-based vergence/accommodative therapy versus 35% with office placebo, 43% with pencil push-ups and 33% with home computer therapy.
- CITT-ART Investigator Group (2019). Treatment of Symptomatic Convergence Insufficiency in Children Enrolled in the CITT-ART: A Randomized Clinical Trial. Optometry and Vision Science, 96(11), 825-835. : Near point of convergence improved 10.4 versus 6.2 cm and fusional vergence 23.2 versus 8.8 prism diopters against placebo, but symptom scores improved similarly in both groups (p = .21).
- CITT-ART Investigator Group (2019). Effect of Vergence/Accommodative Therapy on Reading in Children with Convergence Insufficiency: A Randomized Clinical Trial. Optometry and Vision Science, 96(11), 836-849. : In 310 children, reading comprehension improved 3.7 points with 16 weeks of therapy versus 3.8 points with placebo; therapy was no better than placebo for reading.
- Scheiman M, Kulp MT, Cotter SA, Lawrenson JG, Wang L, Li T (2020). Interventions for convergence insufficiency - a network meta-analysis. Cochrane Database of Systematic Reviews, 12, CD006768. : Across 12 trials and 1,289 participants, office-based therapy with home reinforcement beat placebo in children (RR 3.04, 95% CI 2.32-3.98); the adult evidence is less clear.
- Pediatric Eye Disease Investigator Group (2002). A randomized trial of atropine vs. patching for treatment of moderate amblyopia in children. Archives of Ophthalmology, 120(3), 268-278. : In 419 children under 7, acuity improved 3.16 lines with patching and 2.84 lines with atropine at 6 months; both were judged appropriate first-line treatments.
- American Academy of Pediatrics, American Academy of Ophthalmology, AAPOS, AACO (2009). Joint statement - Learning disabilities, dyslexia, and vision. Pediatrics, 124(2), 837-844. : Holds that dyslexia is language-based, that vision problems can interfere with learning but do not cause dyslexia, and that evidence does not support eye exercises, behavioral vision therapy or tinted lenses for learning disabilities.
- American Academy of Ophthalmology, American Academy of Pediatrics, AAPOS, AACO (2014). Joint Statement: Learning Disabilities, Dyslexia, and Vision - Reaffirmed 2014. : Reaffirms that vision problems are not the cause of primary dyslexia and that behavioral vision therapy and tinted lenses are not endorsed for improving educational performance.
- American Academy of Optometry; American Optometric Association (1997). Vision, learning and dyslexia - a joint organizational policy statement. Journal of the American Optometric Association, 68(5), 284-286. : The optometric position: vision problems can and often do interfere with learning, and optometric care aims to improve visual function as one part of a multidisciplinary approach.
- Barrett BT (2009). A critical evaluation of the evidence supporting the practice of behavioural vision therapy. Ophthalmic and Physiological Optics, 29(1), 4-25. : Finds reasonable evidence for convergence insufficiency treatment, yoked prisms in neurological patients and vision rehabilitation after brain injury, but concludes that most behavioral management approaches are not evidence-based, largely for want of controlled trials.
- Holmes JM, Manh VM, Lazar EL, et al.; Pediatric Eye Disease Investigator Group (2016). Effect of a Binocular iPad Game vs Part-time Patching in Children Aged 5 to 12 Years With Amblyopia. JAMA Ophthalmology, 134(12), 1391-1400. : Acuity improved 1.05 lines with the binocular game versus 1.35 lines with 2 hours a day of patching; only 22.2% of the game group completed more than 75% of prescribed play.
- Manh VM, Holmes JM, Lazar EL, et al.; Pediatric Eye Disease Investigator Group (2018). A Randomized Trial of a Binocular iPad Game Versus Part-Time Patching in Children Aged 13 to 16 Years With Amblyopia. American Journal of Ophthalmology, 186, 104-115. : In 100 teenagers, acuity improved 3.5 letters with the binocular game versus 6.5 letters with patching (adjusted difference -2.7 letters, p = .082); only 13% completed more than 75% of prescribed play.
- Gao TY, Guo CX, Babu RJ, et al.; BRAVO Study Team (2018). Effectiveness of a Binocular Video Game vs Placebo Video Game for Improving Visual Functions in Older Children, Teenagers, and Adults With Amblyopia. JAMA Ophthalmology, 136(2), 172-181. : In 115 participants aged 7 and older, the active binocular game produced no benefit over a placebo game after 6 weeks.
- Pineles SL, Aakalu VK, Hutchinson AK, et al. (2020). Binocular Treatment of Amblyopia: A Report by the American Academy of Ophthalmology. Ophthalmology, 127(2), 261-272. : Reviewing 20 studies, found no level I evidence to support binocular treatment as a substitute for patching or optical treatment.
- Xiao S, Angjeli E, Wu HC, et al.; Luminopia Pivotal Trial Group (2022). Randomized Controlled Trial of a Dichoptic Digital Therapeutic for Amblyopia. Ophthalmology, 129(1), 77-85. : In 105 children aged 4-7, a dichoptic digital therapeutic plus glasses improved acuity 1.8 lines versus 0.8 lines with glasses alone at 12 weeks; the comparator was glasses, not patching.
- Ziak P, Holm A, Halicka J, Mojzis P, Pinero DP (2017). Amblyopia treatment of adults with dichoptic training using the virtual reality Oculus Rift head mounted display: preliminary results. BMC Ophthalmology, 17(1), 105. : In 17 adults with anisometropic amblyopia, 8 sessions of dichoptic VR training improved acuity from 0.58 to 0.43 logMAR and stereoacuity from 263 to 177 arcsec; uncontrolled preliminary study.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.