Learning & Reading

Retained Primitive Reflexes

Primary reflexes are the beginning of a baby's brain development and should only stay active for the first few months of life. When they linger, they can quietly interfere with balance, coordination, attention and the visual system.

Children & adults Assessed as part of a developmental evaluation Coconut Creek · Boynton Beach · Boca Raton · West Palm Beach
Overview

What Primitive Reflexes Are

Primary reflexes — also called primitive reflexes — are automatic, involuntary movements that are fundamental for developing muscle tone, sensory integration, head control and overall development. As a baby grows, these reflexes slowly disappear as the infant’s brain develops and matures and the infant’s movements become more voluntary and controlled.

Movement is crucial for the infant’s brain to integrate the primary reflexes. Vision and movement go hand-in-hand in that process, allowing infants to move through their world as they develop through the early childhood stages of life. From gross motor to fine motor to oculomotor movements, each stage of development is affected by the integration of primary reflexes.

When some reflexes are retained beyond infancy, they can interfere with posture, coordination, attention and the visual system. Retained primary reflexes can result from a problem at birth or during those first few months of life — and they can be noticed from something seemingly minor, like being slow to crawl, to something more severe, like a head injury or a fall.

Causes

Why Reflexes Stay Active

Retained primary reflexes can be caused by issues during the birth process. If there has been a traumatic birth experience or a birth by c-section, this may lead to retained reflexes. They can also be caused by falls, traumas, lack of tummy time, delayed or skipped crawling, chronic ear infections, head trauma and vertebral subluxation.

Many reasons may contribute to primary reflexes being retained or ‘active.’ Retained primary reflexes may be the result of:

  • Stress of the mother and/or baby during pregnancy
  • Lack of movement in utero
  • Restricted body movements, such as the infant spending extended time in car seats, carriers, walkers or jumpers
  • Illness, injury, trauma, chronic stress
  • Other developmental delays

Reflexes that have already integrated may become reactivated later due to trauma, injury, illness or stress — which is why this is worth looking at in teenagers and adults too, not only in young children.

When primary reflexes have not integrated within the appropriate time frame, it is very important to revisit the missed development stages. Those activities can rebuild the foundation and create a new neural pathway.

What We Look At

Five Reflexes and the Signs They Leave Behind

Each retained reflex tends to show up as its own cluster of everyday difficulties. No single item on these lists confirms a retained reflex — the pattern is what a clinician reads.

Moro Reflex

Onset around 28 weeks gestation · normally integrates by about 4–6 months

The Moro reflex is the earliest primary reflex — the whole-body startle response an infant makes when the head drops backwards.

What it affects Vestibular, ocular, motor and visual perceptual skills

Symptoms include

  • Exaggerated startle reflex
  • Motion sickness
  • Eye movement and visual processing problems
  • Poor coordination
  • Poor balance
  • Light sensitivity
  • Frequent infections
  • Inner ear problems
  • Allergies
  • Poor stamina
  • Difficulty with black print on white paper
  • Tense muscle tone
  • Poor auditory discrimination
  • Biochemical and nutritional imbalances
  • Often in “fight or flight” mode
  • Hyperactivity
  • Low self-esteem
Moro reflex diagram: a protective response with onset about 28 weeks gestation that integrates by roughly 4 to 6 months. The stimulus is rapidly dropping the infant’s head backwards; phase 1 is arm extension and abduction, phase 2 is arm flexion and adduction.

Tonic Labyrinthine Reflex (TLR)

The tonic labyrinthine reflex links head position to muscle tone through the balance system, which is why it shows up in posture as much as in vision.

What it affects Ocular, motor, balance, muscle tone and auditory discrimination

Symptoms include

  • Poor posture and/or stooping
  • Weak muscle tone
  • Stiff or jerky movements
  • Toe walking
  • Dislike of sports
  • Eye movement, spatial and visual perceptual problems
  • Motion sickness
  • Poor balance
  • Poor organization skills
  • Poor sequencing skills
  • Poor coordination
  • Poor sense of time

Symmetrical Tonic Neck Reflex (STNR)

Onset around 4–6 months · normally integrates by about 8–12 months

The symmetrical tonic neck reflex ties head movement to what the arms and legs do — the pattern a baby works through on the way to crawling.

What it affects Fixation, focusing from far to near, and crossing the midline

Symptoms include

Symmetrical tonic neck reflex (STNR) diagram: onset about 4 to 6 months, integrating by about 8 to 12 months. Tested in the crawling position — flexing the head makes the arms flex and legs extend, extending the head makes the arms extend and legs bend. Whatever the top half of the body does, the bottom half does the opposite.

Asymmetrical Tonic Neck Reflex (ATNR)

Onset around 37 weeks gestation · normally integrates by about 4–6 months

The asymmetrical tonic neck reflex turns the arm and leg on the side the head faces — the infant pattern that first pairs hand movement with looking.

What it affects Midline issues, eye tracking, balance, handwriting and laterality

Symptoms include

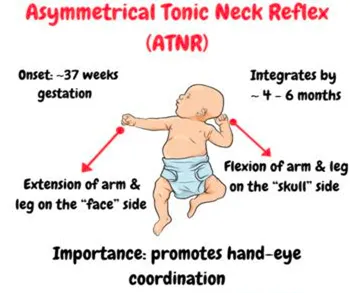
Asymmetrical tonic neck reflex (ATNR) diagram: onset about 37 weeks gestation, integrating by roughly 4 to 6 months. When the head turns, the arm and leg on the face side extend while the arm and leg on the skull side flex. Its role is to promote hand-eye coordination.

Spinal Galant Reflex

The spinal Galant reflex fires when the skin along the lower back is stroked — which is why a waistband or a chair back can keep a child moving all day.

What it affects The ability to sit still, short-term memory and concentration — and it can contribute to bedwetting

Symptoms include

  • Bedwetting
  • Fidgety or wiggly
  • Sensory issues with food texture, or with tags or waistbands in clothing
  • Poor short-term memory
  • Poor concentration
  • ADHD characteristics

If several of these sound familiar, the symptom checklist is a five-minute way to organize what you’re seeing before an appointment, and other signs of a vision problem may fill in the rest of the picture. Retained reflexes are one thread among several — visual-motor integration and developmental delays are often part of the same conversation.

Our Approach

How Vision Therapy Helps

We are proud to assist your child with a primary reflex integration program. It involves the specific movements and patterns that make it possible to retrain the brain and the control center for the reflexes. Reflexes can be integrated using rhythmic movement training techniques that imitate the movements of an infant in development. These repetitive motions develop the reflexes and gradually help develop the frontal and visual cortex of the brain.

Once these reflexes are integrated by the body, many behavioral issues affected by retained primary reflexes become resolved. Because vision is directly linked with the brain and is affected when our brains do not develop as expected, it is important to address the issue. By addressing these reflexes, a vision therapy program provides a comprehensive approach to resolving these problems.

Left unaddressed, retained primary reflexes may be associated with impulsivity, hyperactivity, aggression, developmental delays, anxiety, fear, poor academic performance and poor intellectual development.

At Our Practice

One Piece of the Whole Picture

Dr. Murray has pursued advanced study in primitive reflexes as part of a whole-system view of development. When retained reflexes appear to be contributing, addressing them can be part of an individualized therapy plan.

Reflexes are evaluated as one piece of a comprehensive developmental assessment — alongside eye teaming, focusing, eye movement and visual processing — never in isolation. Where it helps, we coordinate with your child’s occupational therapist, physical therapist or other providers, at our Coconut Creek, Boynton Beach, Boca Raton or West Palm Beach office.

Wondering Whether Reflexes Are Part of the Picture?

A developmental vision evaluation measures how the eyes team, track and focus — and looks at retained primary reflexes where they are relevant — then gives you a clear answer about whether therapy would help.