Common Eye Problems in Children (6-12 Years)
By first grade a child’s eyes take on a job they have never done before. There are hours of near work, copying from board to desk and back, and a screen at school on top of a screen at home. Problems that went unnoticed in preschool surface now, usually as behavior rather than as a complaint. Children rarely say “my eyes hurt.” They say the reading is boring, they lose their place, or they simply stop.
Below are the eight problems we see most often in 6- to 12-year-olds at Vision & Learning Center. For each one we give what the research actually shows, and what is worth a phone call. We have companion guides for ages 2 to 5 and teenagers 13 to 18.
Key takeaways
- Nearsightedness is becoming much more common. About one in three children and teens worldwide is now myopic, up from about one in four in 1990 (Liang et al., 2025).
- Convergence insufficiency means trouble keeping the two eyes aimed at the same close target. It was found in about 13% of fifth- and sixth-graders in a US school study (Rouse et al., 1999). It has the strongest treatment evidence of any binocular condition. Even so, the two big trials disagree about how much of the symptom relief belongs to the therapy itself (CITT, 2008; CITT-ART, 2019).
- Digital eye strain is common once homework moves onto a screen. Blue-light-filtering lenses are not the answer. A Cochrane review of 17 randomized trials in adults found they may make no difference to eye-strain symptoms (Singh et al., 2023). It remains the best evidence we have on these lenses.
- Red-green color vision deficiency was found in 1.4% to 5.6% of boys depending on ancestry, and in 0.5% or fewer girls (Xie et al., 2014).
- Passing a school screening does not rule out a focusing or eye-teaming problem (AOA, 2017).
The first three problems below are refractive errors. That means light does not come to a focus where it should inside the eye. All three are correctable with glasses.
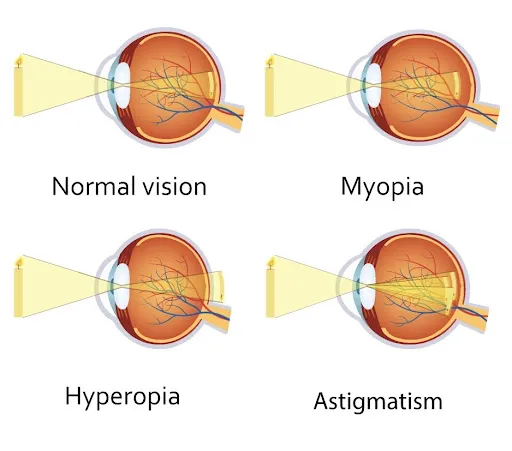
Myopia (nearsightedness)
Myopia develops when the eye grows slightly too long, so distance images land in front of the retina. Close work stays clear; the board goes soft. Watch for squinting at distance, sitting close to the TV, or a child who cannot read the board but reads fine at the desk.
Childhood myopia is climbing. A meta-analysis of 276 studies and 5.4 million participants put prevalence at 24.32% in 1990 and 35.81% in 2023, with 39.80% projected by 2050 (Liang et al., 2025). A separate projection expects about half the world’s population to be myopic by 2050 (Holden et al., 2016).
Screens are often blamed, and the evidence is more modest than the headlines suggest. One systematic review covered 15 studies in 49,789 children and found the picture mixed. Seven of those studies did report a link. But pooling the five that could be combined gave an odds ratio of 1.02, which is effectively none (Lanca & Saw, 2020). A later meta-analysis did find a small association: an odds ratio of 1.26 for smart-device use, rising to 1.77 alongside computer use (Foreman et al., 2021). The studies behind that figure varied widely.
The better-supported lever is daylight. Outdoor time roughly halved the risk of developing myopia in trials, though it did not slow progression once myopia had started (Xiong et al., 2017).
Hyperopia (farsightedness)
In hyperopia the eye is relatively short, so the focusing system works harder. It works hardest of all up close. Small amounts are normal in childhood, but larger amounts make reading tiring even when the eye chart looks fine. Watch for eye rubbing or headaches after 15 to 20 minutes of reading, avoidance of near work, or a child who is bright in discussion and reluctant on the page.
In 492 four- and five-year-olds, children with uncorrected moderate hyperopia scored 4.3 points lower on a preschool early-literacy test than children without it. The gaps were bigger at 4 diopters or more (Kulp et al., 2016). That is an association measured before school age, not proof that glasses raise reading scores. Still, it is a good reason not to dismiss farsightedness as “they see 20/20.”
Astigmatism
Astigmatism means the cornea or lens is shaped more like a football than a basketball. Light then comes to a focus at more than one point instead of a single point on the retina. Print looks smudged or slightly doubled at every distance. Children compensate by squinting, tilting the head, or turning the page at an angle.
In our chairs it is the refractive error parents are least likely to have spotted at home. The blur never lifts, so a child has nothing to compare it with and rarely thinks to mention it. The complaint that reaches us is usually tired eyes or a headache after homework. Measuring it takes a few minutes during the refraction part of an exam, and glasses correct it.
Convergence insufficiency
Convergence insufficiency (CI) is trouble pulling the two eyes inward and holding them on a near target. The eyes drift outward after a few minutes of reading. That produces double or overlapping print, loss of place, or a headache behind the eyes.
CI is not rare. Among 453 fifth- and sixth-graders in a school-based study, 4.2% had definite three-sign CI and another 8.8% were high-suspect, about 13% combined. In the three-sign group, 78.9% also had a focusing (accommodative) problem (Rouse et al., 1999).
It is also the binocular condition with the strongest treatment evidence. The Convergence Insufficiency Treatment Trial randomized 221 children aged 9 to 17. After 12 weeks, 73% of the office-based vergence/accommodative therapy group were successful or improved, versus 35% with office placebo and 33-43% with home programs (CITT, 2008). A Cochrane network meta-analysis of 12 trials confirmed the advantage over placebo in children (Scheiman et al., 2020).
Parents deserve the other half of the story. The larger CITT-ART trial repeated the comparison in 310 children aged 9 to 14, and split the difference. Therapy again beat placebo on the clinical measurements: near point of convergence improved 10.4 cm versus 6.2 cm, and fusional vergence 23.2 versus 8.8 prism diopters. But this time the symptom questionnaire improved about as much in the placebo group, 11.8 versus 10.4 points (P = .21) (CITT-ART treatment results, 2019). Reading comprehension told the same story: up 3.7 points with therapy, 3.8 with placebo (CITT-ART reading results, 2019).
Our position here is a practice view, not a trial result. We think therapy is worth doing when a child has measurable CI and struggles with near work. The eyes get measurably better at the task in every trial, and that is what we treat. We do not promise better grades. We also tell families that in the larger trial the symptom scores improved with placebo attention too. More on our convergence insufficiency page.
Digital eye strain (computer vision syndrome)
Digital eye strain is the cluster of symptoms that follows sustained screen use: aching or burning eyes, headache, intermittent blur, dryness, and neck or shoulder ache. Reviews estimate it affects half or more of screen users (Sheppard & Wolffsohn, 2018). A meta-analysis of 103 studies and 66,577 participants pooled prevalence at 69% (Ccami-Bernal et al., 2024). Those studies varied enormously, and the highest rate was in university students (76.1%) rather than school-age children.
The closest figure we have to this age band comes from a survey of 217 students in online classes during the pandemic. Their mean age was 13, older than most of the children in this guide. In that survey 50.23% reported digital eye strain, as daily device use rose from 1.9 to 3.9 hours (Mohan et al., 2021).
What we suggest at home is unglamorous. Take real breaks away from the screen: we teach the 20-20-20 habit, which is every 20 minutes, look about 20 feet away for 20 seconds. Keep the screen slightly below eye level at roughly arm’s length, light the room well, and remind your child to blink. Treat those as sensible habits rather than proven treatments. One review traced the symptoms mainly to focusing and eye-movement strain plus a drop in blink rate, and concluded that the efficacy of the proposed treatments is unproven (Rosenfield, 2011).
What the trial evidence argues against is blue-light-filtering lenses. A 2023 Cochrane review of 17 randomized trials in adults found they may make no difference to eye-strain symptoms compared with ordinary lenses (Singh et al., 2023). That review covered adults, so it cannot speak directly to a 9-year-old. It is still the best evidence there is on these lenses, and it does not support them. If symptoms persist after habits change, that is our cue to examine focusing and eye teaming rather than blame the screen. See our guides to computer vision syndrome and how much screen time is too much.
Allergic conjunctivitis (eye allergies)
South Florida keeps pollen in the air most of the year, so we see plenty of itchy, watery, pink eyes in this age group. The hallmark is itching in both eyes, with clear discharge and no fever. An infection looks different: it more often starts in one eye, with thicker discharge.
What we suggest at home: limit the trigger, use cool compresses, and consider preservative-free artificial tears or an over-the-counter antihistamine drop. Discourage rubbing. It worsens the reaction, and over years it is one of the habits eye doctors watch for in children with allergic disease. If symptoms are severe, one-sided, painful, light-sensitive or unresponsive to over-the-counter care, have the eye examined rather than treated blind.
Eye injuries and sports eye protection
Children and teenagers account for a large share of sports and recreation eye injuries. The joint American Academy of Pediatrics and American Academy of Ophthalmology statement counted more than 42,000 such injuries in the United States in 2000, 43% of them in people under 15 (AAP/AAO, 2013). That statement also names baseball and basketball as the leaders among 5- to 24-year-olds.
It recommends protective eyewear for every participant in a sport that carries a risk of eye injury. Protection should be mandatory for two groups: athletes who are functionally one-eyed, and athletes whose ophthalmologist recommends eye protection after eye surgery or trauma (AAP/AAO, 2013). Functionally one-eyed means best corrected acuity worse than 20/40 in the poorer-seeing eye. Polycarbonate is the recommended lens material, because it is the most shatter-resistant clear option (AAP/AAO, 2013). Ordinary street-wear glasses are not eye protection.
For an acute injury:
- Flush a chemical splash with clean water or saline, then get seen immediately.
- Shield a possible penetrating injury. Do not patch it and do not press on it.
- Never remove an embedded object.
Sudden pain, light sensitivity, blood in the eye or any change in vision after a hit is an emergency.
Color vision deficiency
Inherited red-green color vision deficiency is carried on the X chromosome, which is why it is overwhelmingly a boys’ condition. In a population-based study of preschoolers, prevalence among boys ran from 1.4% in black children to 5.6% in non-Hispanic white children, with Hispanic at 2.6% and Asian at 3.1% (Xie et al., 2014). In girls it was 0.0% to 0.5%. Because the common forms are inherited, that rate does not change as a child grows. What does change is the classroom consequence, as color-coded worksheets, maps and charts appear.
Most children never mention it, because their colors have always looked that way. Testing takes a couple of minutes at a routine exam. In the same study, testability rose from 57% among 3-year-olds to 89% among 4-year-olds, so most children can be tested reliably from about age 4 (Xie et al., 2014). There is no cure. What changes outcomes is knowing early, telling the teacher, and labeling rather than color-coding. Our guide to spotting color blindness in children walks through the signs.
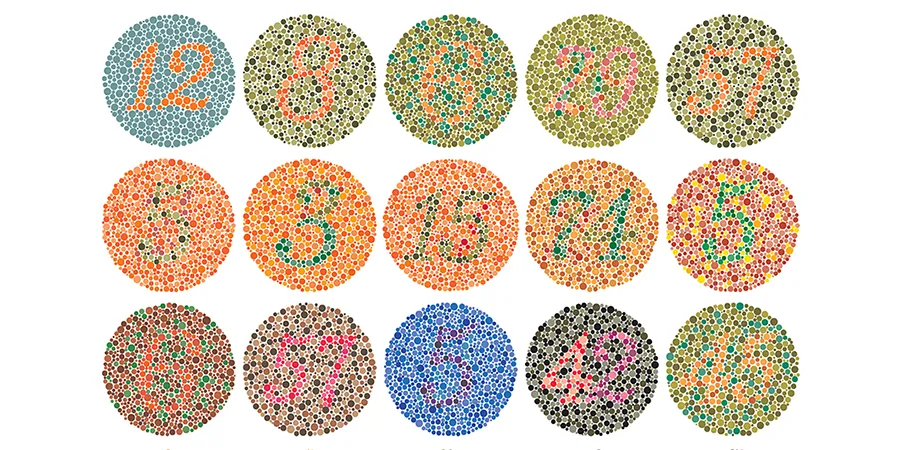
How often should a school-age child be examined?
The US Preventive Services Task Force recommends vision screening at least once between ages 3 and 5, to catch amblyopia and its risk factors (USPSTF, 2017). The American Optometric Association’s pediatric guideline goes further for this age band. It recommends a comprehensive eye examination before first grade, and once a year after that.
The same guideline reports that Snellen acuity testing alone missed 75.5% of the children who turned out to have binocular or eye-movement problems on a full examination (AOA, 2017). It also reports that only 38.7% of children who failed a school screening received follow-up care.
That gap is why we ask parents not to stop at “she passed the screening.” A screening asks whether a child can identify letters at 20 feet. A comprehensive developmental vision evaluation also asks whether the two eyes point at the same word, hold focus for 30 minutes, and move accurately across a line of print.
Is your 6- to 12-year-old avoiding reading, losing place, or complaining of headaches or blur after homework? Has a teacher raised a concern? A full evaluation is the right next step. See what our examinations include or Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
How often should a school-age child have an eye exam?
The American Optometric Association's pediatric guideline recommends a comprehensive eye examination before first grade, then once a year after that for children with no known risk factors. That is more often than the screening-based schedules used in pediatric offices. The US Preventive Services Task Force sets those at least once between ages 3 and 5.
My child passed the school vision screening. Do we still need an exam?
A screening usually checks distance letters only. The AOA guideline reports that Snellen acuity testing alone missed 75.5% of the children later found to have binocular or eye-movement problems on a full examination. It also reports that only 38.7% of children who failed a school screening got follow-up care. Passing a screening is reassuring about distance sight, not about how the two eyes work together up close.
Will limiting screen time stop my child from becoming nearsighted?
Probably not on its own. Reviews of screen time and myopia are mixed. Pooled odds ratios range from 1.02, which is no association at all, to about 1.26. The better-supported lever is time outdoors, which cut the risk of developing myopia by roughly half in trials. It does not slow progression in eyes that are already nearsighted.
Do blue-light glasses help with screen headaches?
A 2023 Cochrane review of 17 randomized trials in adults concluded that blue-light-filtering lenses may make no difference to eye-strain symptoms compared with ordinary lenses. That review covered adults only, so it cannot speak directly to a child. It is still the best evidence available on these lenses, and it does not support them. If a child has symptoms at the screen, we would rather examine the focusing and eye-teaming system than fit a filter.
Which sports need protective eyewear?
The joint American Academy of Pediatrics and American Academy of Ophthalmology statement recommends protective eyewear for every participant in a sport that carries a risk of eye injury. It should be mandatory for two groups: athletes who are functionally one-eyed, and athletes whose ophthalmologist recommends eye protection after eye surgery or trauma. Polycarbonate is the recommended lens material. Baseball and basketball account for the most eye injuries in 5- to 24-year-olds.
Where This Information Comes From
- Liang J, Pu Y, Chen J, et al. (2025). Global prevalence, trend and projection of myopia in children and adolescents from 1990 to 2050: a comprehensive systematic review and meta-analysis. British Journal of Ophthalmology; 109(3):362-371. : Pooled childhood myopia prevalence rose from 24.32% (1990) to 35.81% (2023) across 276 studies and 5.4 million participants, projected at 39.80% by 2050.
- Holden BA, Fricke TR, Wilson DA, et al. (2016). Global Prevalence of Myopia and High Myopia and Temporal Trends from 2000 through 2050. Ophthalmology; 123(5):1036-1042. : Projects that 49.8% of the world population will be myopic by 2050, with high myopia rising from 2.7% to 9.8%.
- Xiong S, Sankaridurg P, Naduvilath T, et al. (2017). Time spent in outdoor activities in relation to myopia prevention and control: a meta-analysis and systematic review. Acta Ophthalmologica; 95(6):551-566. : Outdoor time roughly halved the risk of developing myopia (RR 0.536 in trials) but did not slow progression in already-myopic eyes.
- Lanca C, Saw SM (2020). The association between digital screen time and myopia: A systematic review. Ophthalmic and Physiological Optics; 40(2):216-229. : Across 15 studies of 49,789 children the evidence was mixed: seven studies reported an association, but a meta-analysis of five of them gave a pooled odds ratio of 1.02 (not significant).
- Foreman J, Salim AT, Praveen A, et al. (2021). Association between digital smart device use and myopia: a systematic review and meta-analysis. Lancet Digital Health; 3(12):e806-e818. : Smart-device use was modestly associated with myopia (OR 1.26, 95% CI 1.00-1.60), rising to 1.77 when combined with computer use, with high heterogeneity.
- VIP-HIP Study Group; Kulp MT, Ciner E, Maguire M, et al. (2016). Uncorrected Hyperopia and Preschool Early Literacy. Ophthalmology; 123(4):681-689. : Uncorrected moderate hyperopes scored 4.3 points lower on an early-literacy test than emmetropes, with larger deficits at 4 D or more.
- Rouse MW, Borsting E, Hyman L, et al.; CIRS Group (1999). Frequency of convergence insufficiency among fifth and sixth graders. Optometry and Vision Science; 76(9):643-649. : 13% of 453 fifth- and sixth-graders met a high-suspect or definite CI definition, and 78.9% of three-sign CI children also had accommodative insufficiency.
- Convergence Insufficiency Treatment Trial Study Group (2008). Randomized clinical trial of treatments for symptomatic convergence insufficiency in children. Archives of Ophthalmology; 126(10):1336-1349. : In 221 children aged 9-17, 73% were successful or improved after 12 weeks of office-based therapy versus 35% with office placebo.
- CITT-ART Investigator Group (2019). Treatment of Symptomatic Convergence Insufficiency in Children Enrolled in the Convergence Insufficiency Treatment Trial-Attention & Reading Trial. Optometry and Vision Science; 96(11):825-835. : Therapy beat placebo on the clinical signs (near point of convergence 10.4 vs 6.2 cm; fusional vergence 23.2 vs 8.8 prism diopters) but symptom scores improved similarly in both groups (11.8 vs 10.4 points, P = .21).
- CITT-ART Investigator Group (2019). Effect of Vergence/Accommodative Therapy on Reading in Children with Convergence Insufficiency. Optometry and Vision Science; 96(11):836-849. : Reading comprehension improved 3.7 points with therapy versus 3.8 with placebo in 310 children: therapy was no better than placebo for reading.
- Scheiman M, Kulp MT, Cotter SA, et al. (2020). Interventions for convergence insufficiency: a network meta-analysis. Cochrane Database of Systematic Reviews; 12:CD006768. : Across 12 trials and 1289 participants, office-based therapy with home reinforcement beat placebo in children (RR 3.04); adult evidence is less clear.
- Sheppard AL, Wolffsohn JS (2018). Digital eye strain: prevalence, measurement and amelioration. BMJ Open Ophthalmology; 3(1):e000146. : Estimates that digital eye strain affects 50% or more of screen users, split between focusing/eye-teaming stress and dry-eye symptoms.
- Ccami-Bernal F, Soriano-Moreno DR, Romero-Robles MA, et al. (2024). Prevalence of computer vision syndrome: A systematic review and meta-analysis. Journal of Optometry; 17(1):100482. : Pooled prevalence of computer vision syndrome was 69.0% across 103 studies and 66,577 participants (I2 99.7%), highest in university students at 76.1%.
- Mohan A, Sen P, Shah C, Jain E, Jain S (2021). Prevalence and risk factor assessment of digital eye strain among children using online e-learning during the COVID-19 pandemic (DESK study-1). Indian Journal of Ophthalmology; 69(1):140-144. : 50.23% of 217 students (mean age 13) attending online classes reported digital eye strain; device use rose from 1.9 to 3.9 hours a day.
- Rosenfield M (2011). Computer vision syndrome: a review of ocular causes and potential treatments. Ophthalmic and Physiological Optics; 31(5):502-515. : Attributes computer vision syndrome mainly to focusing/eye-movement strain and dry eye from a reduced blink rate, and states that the efficacy of the proposed treatments is unproven.
- Singh S, Keller PR, Busija L, et al. (2023). Blue-light filtering spectacle lenses for visual performance, sleep, and macular health in adults. Cochrane Database of Systematic Reviews; 8:CD013244. : Across 17 randomized trials in adults, blue-light-filtering lenses may make no difference to eye-strain symptoms versus standard lenses; the review did not cover children.
- American Academy of Pediatrics & American Academy of Ophthalmology (2013). Protective Eyewear for Young Athletes (joint policy statement, as published by the AAO). : Reports more than 42,000 sports and recreation eye injuries in the US in 2000, 43% in people under 15, with baseball and basketball leading at ages 5-24; recommends protective eyewear for all participants in sports with a risk of eye injury; calls it mandatory for functionally one-eyed athletes (best corrected acuity worse than 20/40 in the poorer-seeing eye) and for those whose ophthalmologist recommends it after surgery or trauma; polycarbonate is the recommended lens material.
- Xie JZ, Tarczy-Hornoch K, Lin J, Cotter SA, Torres M, Varma R; MEPEDS Group (2014). Color vision deficiency in preschool children: the Multi-Ethnic Pediatric Eye Disease Study. Ophthalmology; 121(7):1469-1474. : Color vision deficiency in boys was 1.4% (black), 2.6% (Hispanic), 3.1% (Asian) and 5.6% (non-Hispanic white); 0.0-0.5% in girls; testability rose from 57% at 37-48 months to 89% at 49-60 months, so most children are testable from about age 4.
- American Optometric Association (2017). Evidence-Based Clinical Practice Guideline: Comprehensive Pediatric Eye and Vision Examination. : Recommends a comprehensive exam before first grade and annually thereafter; reports that acuity-only screening missed 75.5% of binocular and eye-movement problems and that only 38.7% of screening failures received follow-up.
- US Preventive Services Task Force; Grossman DC, Curry SJ, Owens DK, et al. (2017). Vision Screening in Children Aged 6 Months to 5 Years. JAMA; 318(9):836-844. : Recommends vision screening at least once at ages 3-5 to detect amblyopia and its risk factors; evidence insufficient under age 3.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.