Common Eye Problems in Children (2-5 Years)
Between the ages of two and five, your child is finishing the wiring of a visual system they will use for life — and has no way of telling you when something is wrong. A four-year-old who sees blurry out of one eye assumes everyone does, and says nothing.
That splits preschool eye problems into two groups. Some are loud: a red eye, a swollen lid, a sudden squint into the sun. Others are silent, painless, and found only because somebody looked. The loud ones are usually the easier half. Here are the eight we see most often in our Coconut Creek, Boynton Beach and West Palm Beach offices.
Key takeaways
- Ages 3 to 5 are the window when amblyopia is already established and still most treatable. Children aged 3 to 7 respond better to treatment than children aged 7 to 12 (Holmes et al., 2011).
- Amblyopia is often a glasses problem first. Correction alone improved acuity by two or more lines in 77% of preschoolers with untreated anisometropic amblyopia, and resolved it in 27% (Cotter et al., 2006).
- Farsightedness that nobody has corrected is associated with weaker early-literacy scores at ages 4 and 5 (Kulp et al., 2016).
- Screening at the pediatrician is worth doing and is not the same as an examination (USPSTF, 2017; AOA, 2017).
- Pain, light sensitivity, a sudden eye turn, or an injury are same-day reasons to be seen.
Why ages 2 to 5 are the window that matters
The US Preventive Services Task Force recommends vision screening at least once in every child aged 3 to 5 to detect amblyopia and its risk factors, and notes that 1% to 6% of children under 6 have amblyopia or a risk factor for it; under age 3 it found the evidence insufficient either way (USPSTF, 2017). The American Academy of Pediatrics describes instrument-based screening in the pediatrician’s office from about 12 months, with direct acuity testing often possible by age 4 (Donahue & Nixon, 2016).
Our profession’s guideline asks for more. The American Optometric Association recommends a comprehensive examination at 6 to 12 months, at least once between ages 3 and 5, and again before first grade and annually after that — and reports that acuity testing alone missed 75.5% of the children a complete examination found to have binocular or eye-movement problems, and that only 38.7% of children who failed a school screening ever received follow-up care (AOA, 2017). Those figures are the guideline’s summary of its cited studies, not our own data. Screening is a filter; an examination is a look.
The eight problems we see most in preschoolers
1. Refractive errors: nearsighted, farsighted, astigmatism
The eye’s shape stops light landing sharply on the retina, and the world goes soft — at distance (myopia), up close and eventually everywhere (hyperopia), or in one direction at every distance (astigmatism).
What you might notice: squinting, sitting close to the television, holding books very near, head tilting, eye rubbing, avoiding puzzles and picture books, or nothing at all.
Farsightedness deserves its own note, because a preschooler can often “power through” it and still pass the eye chart. In the VIP-HIP study of 492 four- and five-year-olds, children with uncorrected hyperopia of +3 to +6 D scored 4.3 points lower on a test of early literacy than children without it, and the gap widened at 4 D or more (Kulp et al., 2016). That is an association measured at a single point in time, not proof that glasses raise reading scores — but it is a good reason not to shrug off farsightedness in a child heading for kindergarten.
What to do: glasses are the treatment; there is no home remedy, and none is needed. Outdoor play is still worth protecting: across 25 studies, time outdoors roughly halved the risk of developing myopia, though it did not slow myopia already underway (Xiong et al., 2017).
2. Strabismus: an eye that turns
One eye points somewhere the other is not — in, out, up or down — constantly, or only when your child is tired, sick or concentrating. Pooled across 56 studies, about 1.93% of people have some form of strabismus (Hashemi et al., 2019); in US preschoolers it was 2.4% to 2.5% (MEPEDS, 2008).
What you might notice: a visible turn (photos are useful evidence), head tilting or face turning, closing one eye in bright light, clumsiness, or double vision.
What to do: have it examined promptly. A newborn’s eyes often look crossed or wander out to the side, but by about three months the eyes should be working together to focus and track (American Academy of Ophthalmology) — so a turn that is still there in a preschooler is not something to wait out, and it is one of the main routes to amblyopia. Treatment may involve glasses, prism, patching, vision therapy, surgery or a combination, depending on the type and cause.
3. Amblyopia: the quiet one
Amblyopia — lazy eye — is reduced vision in an otherwise healthy eye, because the brain stopped developing that eye’s input. It affected 1.5% to 2.6% of preschoolers in a large population study, and 78% of those cases were attributable to refractive error (MEPEDS, 2008). It causes no pain, no redness and no complaint.
What you might notice: covering one eye changes how your child reacts; poor depth perception; bumping into things; head tilting; or, very often, nothing.
What to do: the first step is usually glasses, not a patch. In a PEDIG study of 84 children aged 3 to under 7 with previously untreated anisometropic amblyopia, spectacle correction alone improved the amblyopic eye by two lines or more in 77% of children and fully resolved the amblyopia in 27% (Cotter et al., 2006). If a gap remains, patching is added — and less of it is needed than parents expect: 2 hours a day produced the same 2.40 lines of improvement as 6 hours in children under 7 with moderate amblyopia (Repka et al., 2003).
Starting early pays. Pooled PEDIG data show children aged 3 to 7 respond better than children aged 7 to under 13 (Holmes et al., 2011), and by age 15, 59.9% of children treated before age 7 saw 20/25 or better in the amblyopic eye — though 48.3% still had a two-line difference between their eyes, so a good outcome is not always a perfect one (Repka et al., 2014). Depth perception matures over exactly these years, from about 100 arcsec at age 3 to 60 arcsec by age 5 (Birch et al., 2008). More on our lazy eye page.
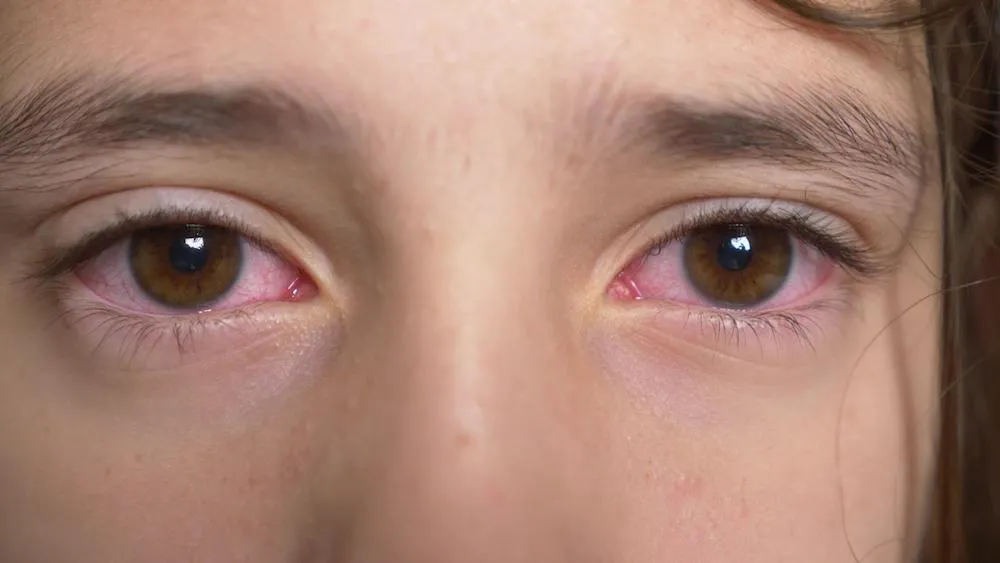
4. Pink eye (infectious conjunctivitis)
Inflammation of the clear membrane over the white of the eye. Viral conjunctivitis is the most common infectious form and needs supportive care rather than antibiotics; uncomplicated bacterial conjunctivitis clears on its own in one to two weeks, though topical antibiotics shorten it. Lids stuck together on waking, without itching, point toward a bacterial cause (Azari & Barney, 2013).
At home: wipe from the inner corner outward with a clean warm cloth, wash hands often, and keep towels and pillowcases separate.
Be seen if: there is eye pain, light sensitivity, blurred vision, heavy swelling, thick yellow-green discharge that keeps returning, or no improvement in a few days.
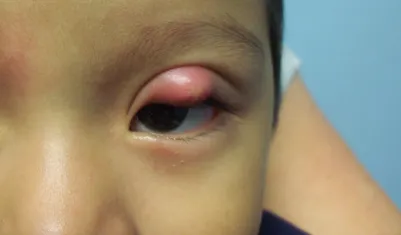
5. Chalazia and styes
A stye is an infected oil gland at the lid margin: red, tender, pointing outward. A chalazion is a blocked oil gland further back in the lid: firmer, rounder, generally painless.
At home: a warm compress for 10 to 15 minutes, three or four times a day, plus gentle lid cleaning. The warmth does the real work — it softens the blocked oil so the gland can drain. Never squeeze or pop it.
Be seen if: it has not settled in about a week, it is growing, the redness spreads across the lid or cheek, your child has a fever, or the lump is big enough to press on the eye. A large chalazion can blur the vision underneath it, and at this age that matters.
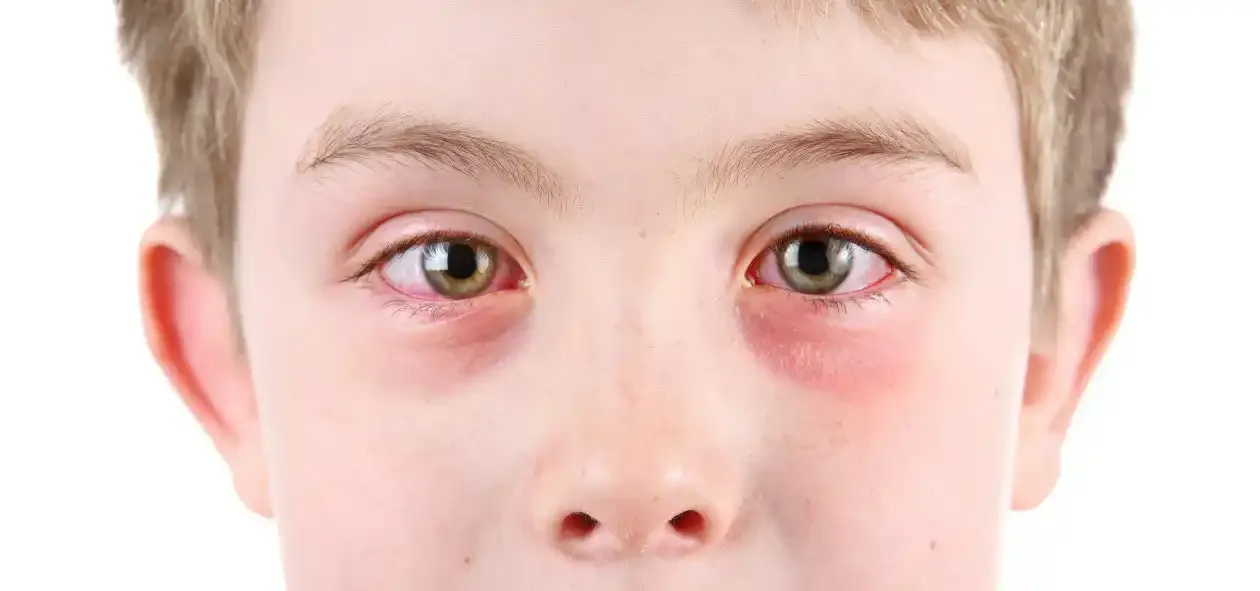
6. Allergic conjunctivitis
Pollen, dust, mold or pet dander set off an allergic reaction in the eye. It is extremely common — the JAMA review puts allergic conjunctivitis at up to 40% of the population and identifies itching as its most consistent feature (Azari & Barney, 2013). In South Florida it tends to be year-round rather than seasonal.
What you might notice: itching above all, watery eyes, puffy lids, constant rubbing, and both eyes involved rather than one.
At home: cool compresses, preservative-free artificial tears to rinse the allergen away, washing hair and face after outdoor play, and reducing exposure where you can. Over-the-counter antihistamine or mast-cell drops made for children help many kids.
Be seen if: rubbing is relentless, drops are not controlling it, or vision seems affected. Hard, sustained eye rubbing is worth stopping — it is hard on the cornea over time.
7. Light sensitivity (photophobia)
Squinting in bright light, tearing outdoors, wanting the blinds down. Often it is ordinary — pale eyes and bright Florida sun are enough. Sometimes it signals an irritated eye surface, inflammation inside the eye, or an uncorrected prescription making focusing harder.
At home: a wide-brimmed hat and UV-blocking sunglasses.
Be seen if: the sensitivity is new, one-sided or severe, or comes with redness, pain, tearing or changed vision. Persistent photophobia in a preschooler should be examined, not just shaded.
8. Something in the eye
Sand, an eyelash, a fleck of dirt — usually minor, usually self-resolving.
At home: stop the rubbing first; that is what turns a speck into a scratch. Wash your hands, then flush the eye with clean lukewarm water or sterile saline for several minutes, tilting the head so water runs away from the other eye.
Go to urgent or emergency care if: anything struck the eye at speed, a chemical splashed in (flush for 15 minutes on the way), the object is embedded or metallic, there is blood in the colored part of the eye, the pupil looks an odd shape, or pain, light sensitivity or blurred vision persist after it is out. Never try to remove an embedded object yourself.
When to call us the same day
- A new or worsening eye turn
- A white or hazy pupil, or a white reflection in a photograph instead of red-eye
- Eye pain, or light sensitivity that is new
- Sudden double vision, or a new head tilt
- An eye injury, chemical splash or embedded object
- A red eye with pain and blurred vision, rather than itch and discharge
What a preschool examination actually involves
Nobody has to read letters. We test acuity with pictures, matching cards or tumbling-E, measure the prescription with lights and lenses instead of “which is better, one or two,” check alignment and eye teaming, measure depth perception, look at focusing, and examine eye health. To a three-year-old most of it looks like a game, and it takes less time than the paperwork.
Our clinical perspective is simple: the problems of this age group are highly treatable, and the window is open now. Finding a farsighted prescription at four is a pair of glasses. Finding it at nine is often a much longer conversation.
If anything here sounds like your child — or if it has simply been a while — schedule an evaluation at any of our four offices, or read what to expect at a comprehensive eye examination. Companion guides: babies 0 to 18 months, children 6 to 12 years, and how much screen time is too much.
Common Questions About This Topic
When should a preschooler have their eyes checked?
The US Preventive Services Task Force recommends vision screening at least once between ages 3 and 5 to catch amblyopia and its risk factors, and the American Academy of Pediatrics describes instrument-based screening in the pediatrician's office from about 12 months. The American Optometric Association goes further and recommends a full comprehensive eye examination at 6 to 12 months, at least once between 3 and 5 years, and before first grade and annually after that. Sooner if anything worries you.
My child passed the vision screening at their check-up. Is that enough?
A passed screening is reassuring for amblyopia and large refractive errors, which is what screening is designed to find. It is not the same as an examination. The AOA guideline notes that Snellen acuity testing alone missed 75.5% of children later found on a full examination to have binocular or eye-movement problems, and that only 38.7% of children who failed a school screening received follow-up care.
Can amblyopia be treated with glasses alone?
Often it improves a great deal. In a PEDIG study of 84 children aged 3 to under 7 with previously untreated anisometropic amblyopia, glasses alone improved the amblyopic eye by two lines or more in 77% of children and resolved the amblyopia in 27%. That is why we usually start with the correct prescription and re-measure before adding patching.
How long does my child need to wear a patch each day?
Less than most parents expect. A PEDIG randomized trial in children under 7 with moderate amblyopia found 2 hours of daily patching produced the same 2.40-line improvement as 6 hours. Your doctor will set the dose based on how deep the amblyopia is and how your child responds.
Is pink eye in a preschooler always contagious?
No. Red eyes can be viral, bacterial or allergic. Itching that dominates the picture points toward allergy; eyelids stuck together on waking, without itching, points toward a bacterial cause. Most uncomplicated bacterial conjunctivitis clears on its own in one to two weeks, though antibiotic drops shorten it. Pain, light sensitivity, blurred vision or no improvement in a few days should be examined.
Where This Information Comes From
- US Preventive Services Task Force; Grossman DC, Curry SJ, Owens DK, et al. (2017). Vision Screening in Children Aged 6 Months to 5 Years: US Preventive Services Task Force Recommendation Statement. JAMA; 318(9):836-844. : Recommends screening at least once at ages 3-5 for amblyopia and its risk factors (B recommendation); evidence insufficient under age 3; 1-6% of children under 6 have amblyopia or its risk factors.
- Donahue SP, Nixon CN; AAP Section on Ophthalmology, Committee on Practice and Ambulatory Medicine, AAO, AAPOS, AACO (2016). Visual System Assessment in Infants, Children, and Young Adults by Pediatricians. Pediatrics; 137(1):28-30. : Instrument-based screening should be attempted between 12 months and 3 years and at annual well-child visits; direct acuity testing can often begin by age 4; children who fail should be referred.
- American Optometric Association (2017). Evidence-Based Clinical Practice Guideline: Comprehensive Pediatric Eye and Vision Examination. St. Louis: AOA. : Recommends a comprehensive examination at 6-12 months, at least once between 3 and 5 years, and before first grade and annually after; reports that acuity-only screening missed 75.5% of binocular and oculomotor problems and that only 38.7% of screening failures got follow-up care.
- Multi-ethnic Pediatric Eye Disease Study Group (2008). Prevalence of amblyopia and strabismus in African American and Hispanic children ages 6 to 72 months. Ophthalmology; 115(7):1229-1236.e1. : In 6,014 preschoolers, strabismus affected 2.4-2.5% and amblyopia 1.5-2.6%; 78% of amblyopia was attributable to refractive error.
- Hashemi H, Pakzad R, Heydarian S, et al. (2019). Global and regional prevalence of strabismus: a comprehensive systematic review and meta-analysis. Strabismus; 27(2):54-65. : Across 56 studies and 229,396 participants, pooled prevalence of any strabismus was 1.93% (exotropia 1.23%, esotropia 0.77%).
- American Academy of Ophthalmology (2026). Vision Development: Newborn to 12 Months. EyeSmart patient education page. : Babies' eyes may appear crossed or wander for the first 2 months, but at 3 months the eyes should work together to focus and track objects.
- Cotter SA, Edwards AR, Wallace DK, et al.; Pediatric Eye Disease Investigator Group (2006). Treatment of anisometropic amblyopia in children with refractive correction. Ophthalmology; 113(6):895-903. : In 84 children aged 3 to under 7 with untreated anisometropic amblyopia, glasses alone improved acuity by 2 or more lines in 77% and resolved the amblyopia in 27%.
- Repka MX, Beck RW, Holmes JM, et al.; Pediatric Eye Disease Investigator Group (2003). A randomized trial of patching regimens for treatment of moderate amblyopia in children. Archives of Ophthalmology; 121(5):603-611. : In 189 children under 7 with moderate amblyopia, 2 hours and 6 hours of daily patching each produced 2.40 lines of improvement at 4 months (62% success in both groups).
- Holmes JM, Lazar EL, Melia BM, et al.; Pediatric Eye Disease Investigator Group (2011). Effect of age on response to amblyopia treatment in children. Archives of Ophthalmology; 129(11):1451-1457. : Pooled individual data from 4 PEDIG trials: children aged 7 to under 13 responded less well than children aged 3-7, though some older children still responded markedly.
- Repka MX, Kraker RT, Holmes JM, et al.; Pediatric Eye Disease Investigator Group (2014). Atropine vs patching for treatment of moderate amblyopia: follow-up at 15 years of age. JAMA Ophthalmology; 132(7):799-805. : At age 15, 59.9% of children treated before age 7 saw 20/25 or better in the amblyopic eye, but 48.3% still had a 2-line or greater difference between eyes.
- VIP-HIP Study Group; Kulp MT, Ciner E, Maguire M, et al. (2016). Uncorrected Hyperopia and Preschool Early Literacy: Results of the VIP-HIP Study. Ophthalmology; 123(4):681-689. : Uncorrected hyperopes (+3 to +6 D) aged 4-5 scored 4.3 points lower on an early-literacy test than emmetropes; an association, not proof that glasses raise literacy scores.
- Birch E, Williams C, Drover J, et al. (2008). Randot Preschool Stereoacuity Test: normative data and validity. Journal of AAPOS; 12(1):23-26. : In 4,355 normally sighted children, average stereoacuity improved from 100 arcsec at age 3 to 60 arcsec by age 5 and 40 arcsec by age 7.
- Azari AA, Barney NP (2013). Conjunctivitis: a systematic review of diagnosis and treatment. JAMA; 310(16):1721-1729. : Viral is the most common infectious conjunctivitis and needs supportive care; uncomplicated bacterial cases resolve in 1-2 weeks; allergic conjunctivitis affects up to 40% of the population, with itching the most consistent sign.
- Xiong S, Sankaridurg P, Naduvilath T, et al. (2017). Time spent in outdoor activities in relation to myopia prevention and control: a meta-analysis and systematic review. Acta Ophthalmologica; 95(6):551-566. : Outdoor time protected against myopia onset (risk ratio about 0.54) but did not slow progression in eyes that were already myopic.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.