Common Eye Problems in Babies (0-18 Months)
Babies change fast in the first 18 months, and their vision changes with them. Most of what worries parents about a baby’s eyes turns out to be common and self-limiting. A few findings are not. Below are the eight problems families ask us about most, what the research shows about each, and the signs that mean call today rather than wait.
Key takeaways
- Watery, crusty eyes in a comfortable baby are usually a blocked tear duct, and most clear on their own in the first year (MacEwen & Young, 1991).
- Occasional crossing or drifting is common in the first two to three months, while infantile esotropia presents before six months (AAO, 2023). Our own rule is that a constant turn at any age, or any turn still there after about four months, gets examined rather than watched.
- Amblyopia affects roughly 1.5-2.6% of US preschoolers and strabismus about 2.4-2.5%, so neither is rare (MEPEDS, 2008).
- Call the same day for a white or gray pupil, which means an abnormal red reflex (AAP et al., 2008); an eye that looks larger or hazier than the other, which can be congenital glaucoma (Faiq et al., 2013); or a baby not yet focusing and following, which the eyes should be doing together by about three months (AAO, 2026).
- The AOA recommends a first comprehensive infant assessment between 6 and 12 months (AOA, 2017); pediatricians screen from the nursery onward (Donahue & Nixon, 2016).
What normal looks like
Knowing the milestones makes the problems easier to spot. For roughly the first two months a baby’s eyes often do not work together well and may appear to cross or wander; by about three months they should focus and follow together, and depth perception develops more fully around five months (American Academy of Ophthalmology, 2026; AOA, Infant Vision). For more on what your baby is actually seeing, see what can my baby see.
1. Blocked tear duct (nasolacrimal duct obstruction)
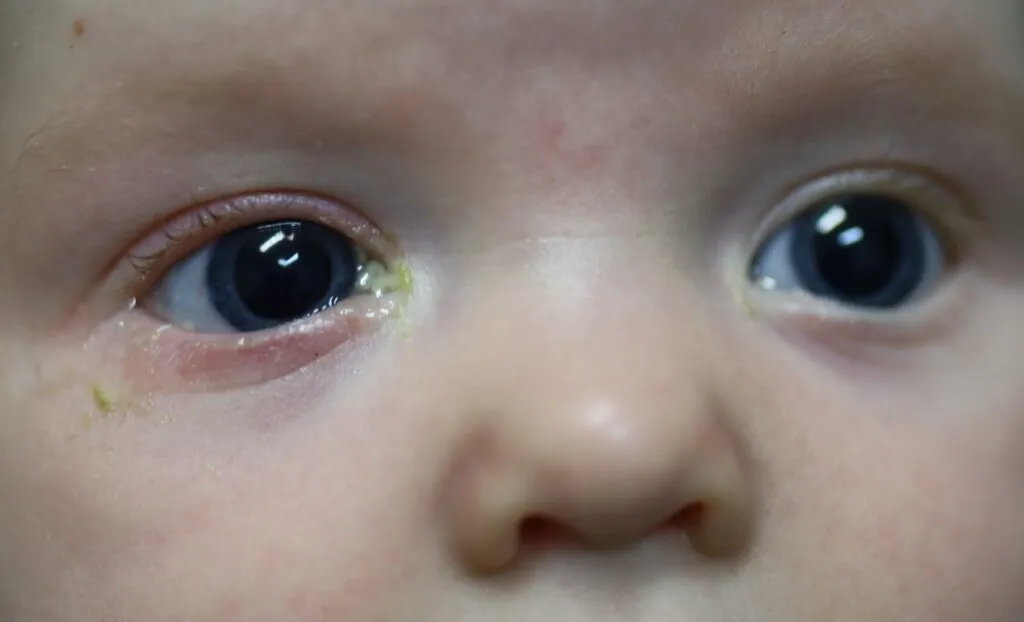
The duct that drains tears into the nose is often not fully open at birth. The eye waters constantly and lashes crust after sleep, but the white of the eye stays white and the baby is comfortable.
This is common, and it usually resolves. In a cohort of 4,792 infants, 20% showed poor tear drainage at some point in the first year, 95% of them in the first month, and 96% resolved before the first birthday (MacEwen & Young, 1991). Even among babies still blocked at 6 to under 10 months, a Pediatric Eye Disease Investigator Group trial found 66% of eyes resolved within six months with massage and antibiotic drops as needed, without surgery (PEDIG, 2012).
At home: gentle massage between the inner corner of the eye and the nose several times a day, and a warm damp cloth to wipe discharge, using a fresh cloth for each eye.
Call your doctor if: the eye itself turns red, the lid swells, your baby seems in pain, there is fever, or the tearing has not settled by the first birthday.
2. Eye infections and newborn conjunctivitis
Conjunctivitis in babies can be viral, bacterial or irritant: pink whites of the eye, swollen lids, discharge that glues the lashes shut. Age matters more than anything else here. In an older baby with a mild pink eye, gentle cleaning and a call to the pediatrician is a reasonable first step. In the first month of life we treat a red eye with discharge as urgent rather than watchful. That is our clinical rule rather than a research finding: newborn eyes have little margin, and we would far rather see a baby who turns out to be fine. Thick yellow or green discharge, a markedly swollen lid, pain, or a baby off feeds warrants a same-day call at any age.
3. Infantile cataract
A cataract is a clouding of the eye’s lens. It is uncommon, with a pooled prevalence of about 4.24 per 10,000 people, but it remains a leading treatable cause of childhood blindness (Wu et al., 2016). Signs are a white or gray pupil, wobbling eye movements, or a baby who does not fix on and follow faces.
This is why the red reflex check matters. A joint policy of the American Academy of Pediatrics, AAPOS, the AAO and AACO holds that red reflex testing is an essential part of the newborn, infant and child physical examination, and sets out when to refer (AAP et al., 2008). Any white pupil, or a reflex that differs between the eyes, is a same-day referral. There is no home remedy.
4. Strabismus (an eye turn)
Strabismus means the eyes point in different directions: one may turn in, out, up or down. Pooled across 56 studies, about 1.93% of people have some form of it (Hashemi et al., 2019), and US preschool studies put it at 2.4-2.5% (MEPEDS, 2008).
Timing is the key. The AAO’s Preferred Practice Pattern notes that intermittent esotropia in the first three months of life may occur and does not necessarily predict constant strabismus, while infantile esotropia presents before six months and is unlikely to resolve on its own (Sprunger et al., 2023). The same panel adds that some babies whose turn is intermittent, variable or small can still straighten by their first birthday. Some babies also have pseudoesotropia, where a wide nasal bridge makes straight eyes look crossed. Only an examination separates the two.
Get it checked if: the turn is constant at any age, it is still there after about four months, it is new, or your baby consistently tilts or turns the head to look at things.
5. Amblyopia (lazy eye)
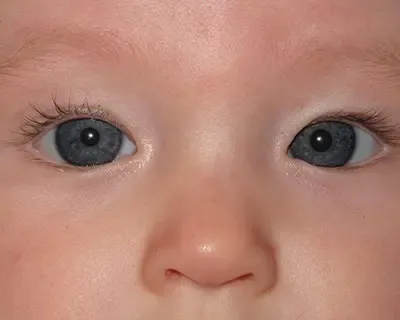
Amblyopia develops when the brain does not learn to use one eye normally, usually because of an eye turn, an unequal glasses prescription, or something blocking the visual pathway. Globally about 1.44% of people are affected, around 2.41% in North America (Fu et al., 2020); in US preschoolers it runs 1.5-2.6%, and 78% traces back to refractive error (MEPEDS, 2008). Babies rarely show obvious symptoms, which is why it is found on examination rather than at home.
The treatment evidence is strong and worth stating plainly. Glasses alone improve acuity, and most moderate amblyopia responds to about two hours a day of patching or weekend atropine drops (AAO Amblyopia PPP, 2023); in a 419-child randomized trial, patching gave 3.16 lines of improvement and atropine 2.84 lines at six months (PEDIG, 2002). That same AAO panel found no convincing evidence that eye exercises treat amblyopia itself. Our clinical view: glasses and patching or atropine come first, and binocular vision therapy has a role later, for the teaming and depth-perception skills that often remain once acuity improves. More on our lazy eye page.
6. Ptosis (a drooping eyelid)
Congenital ptosis is a droop of the upper lid that can cover part of the pupil. Watch for a lid sitting noticeably lower on one side, a chin-up head posture, or a baby who favors one eye. The reason to have it measured rather than monitored at home is amblyopia risk: in a population-based series of 107 children with ptosis, 14.9% developed amblyopia, roughly one in seven, and only about half of that came from the lid blocking vision. Most of the rest came from associated refractive error and strabismus (Griepentrog et al., 2013). That is not something you can see from the outside.
7. Styes and chalazia
A stye is a tender red bump at the lid margin from an infected oil gland. A chalazion is a firmer, usually painless lump from a blocked gland. Both are common and usually settle with a warm compress for a few minutes several times a day. Do not squeeze or pop it.
Call your doctor if it is not improving after a week or two, it is growing, the whole lid becomes red and swollen, or your baby is clearly uncomfortable. In our experience a large chalazion can press on the eye and blur the image enough to matter at this age, which is why we would rather look at one that is not settling.
8. Light sensitivity (photophobia)
Squinting in bright Florida sun is normal, and a wide-brimmed hat plus shade is sensible for every baby. Persistent, marked light sensitivity indoors is different.
Primary congenital glaucoma appears at birth or within the first year and classically presents as a triad of watering, light sensitivity and forceful eyelid squeezing (Faiq et al., 2013). It is rare, but it is time-critical. Light sensitivity together with constant tearing, eyelid squeezing, or an eye that looks larger or hazier than its partner is a same-day call.
Red flags: call the same day
- A white, gray or unusually bright pupil, in person or in flash photos
- One eye looking larger, cloudier or hazier than the other
- Light sensitivity with tearing and forceful eyelid squeezing
- A red, painful eye with discharge in a baby under one month
- A new or constant eye turn, or eyes that shake or wobble
- No steady eye contact or face-following by about three months
- Any eye injury or chemical splash
When should my baby have an eye exam?
Families get two different answers, and it is fairer to give you both. The AOA’s evidence-based pediatric guideline recommends a comprehensive in-person eye and vision assessment for infants between 6 and 12 months (AOA, 2017). Pediatrics and ophthalmology describe screening instead: red reflex and inspection from the nursery, instrument-based screening from about 12 months (Donahue & Nixon, 2016), at least one screening between ages 3 and 5 with evidence judged insufficient under age 3 (USPSTF, 2017), and the position that a comprehensive exam is not necessary for a healthy child who passes screening (Hutchinson et al., 2023).
We follow the AOA guideline: an infant assessment between 6 and 12 months, and sooner if anything on the red-flag list appears or there is a family history of eye turns, high prescriptions or childhood eye disease. An infant exam asks nothing of your baby: we check the red reflex, alignment, fixation and following, pupils, eye health and the refractive error using retinoscopy, all with lights and toys. See our examinations page, what changes next in our guide for ages 2-5, and, for the stage after that, our complete screen-time guide for parents.
The bottom line
Most baby eye worries are ordinary, and most blocked ducts and mild irritations settle without treatment. The conditions that carry real cost, amblyopia, strabismus, cataract and glaucoma, are the quiet ones, and they respond best when found early. If anything here describes your baby, or you simply want a baseline while the visual system is developing, schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
Is it normal for a newborn's eyes to cross?
Brief, occasional crossing or drifting is common in the first two to three months while the eye muscles and the brain's teaming system are still calibrating. The American Academy of Ophthalmology notes that by about three months the eyes should work together to focus and follow. Our own rule, rather than a published cut-off, is that a turn which is constant at any age, or any turn still present after about four months, gets examined rather than watched.
My baby's eye is always watery and crusty. Do we need antibiotics?
Usually not. Persistent tearing with crusting in an otherwise comfortable, white eye is most often a blocked tear duct. In a cohort of 4,792 infants, 20% showed signs of poor tear drainage at some point in the first year and 96% resolved before the first birthday. Redness of the eye itself, swelling, pain or fever is a different picture and needs to be seen.
When should my baby have a first eye exam?
The American Optometric Association recommends a comprehensive infant eye and vision assessment between 6 and 12 months of age. Pediatricians also screen at well-child visits starting in the newborn nursery. Ophthalmology's position is that a comprehensive exam is not required for a healthy baby who passes screening, so families see a range of advice; we are happy to explain what an infant exam involves so you can decide.
Can an eye problem be found before a baby can read a chart?
Yes. Infant eye examinations do not depend on a child naming letters. We assess the red reflex, eye alignment, how each eye fixes and follows, pupil responses, eye health, and the refractive error using retinoscopy, which needs no answers from your baby.
Which baby eye signs are emergencies?
Call the same day for a white or gray pupil, an eye that looks larger or hazier than the other, marked light sensitivity with tearing and eyelid squeezing, a red painful eye with discharge in a newborn, a sudden new eye turn, or a baby who is not looking at faces by about three months.
Where This Information Comes From
- MacEwen CJ, Young JD (1991). Epiphora during the first year of life. Eye (London). : In 4,792 infants, 20% had evidence of defective tear drainage during the first year, 95% of them in the first month, and 96% resolved before age one.
- Pediatric Eye Disease Investigator Group (2012). Resolution of congenital nasolacrimal duct obstruction with nonsurgical management. Archives of Ophthalmology. : Among infants aged 6 to under 10 months managed with massage and antibiotics as needed, 66% of eyes resolved without surgery within 6 months.
- American Academy of Pediatrics Section on Ophthalmology, AAPOS, AAO, AACO (2008). Red reflex examination in neonates, infants, and children. Pediatrics. : Policy statement holding that red reflex testing is an essential component of the neonatal, infant and child physical examination, with criteria for specialist referral.
- Wu X, Long E, Lin H, Liu Y (2016). Prevalence and epidemiological characteristics of congenital cataract: a systematic review and meta-analysis. Scientific Reports. : Pooled prevalence of congenital cataract across 27 studies was 4.24 per 10,000 people; it remains a leading treatable cause of childhood blindness.
- Sprunger DT, Lambert SR, Hercinovic A, et al. (2023). Esotropia and Exotropia Preferred Practice Pattern. Ophthalmology. : States that intermittent esotropia during the first 3 months of life may occur and does not necessarily predict constant strabismus, while infantile esotropia presents before age 6 months and is unlikely to resolve.
- Hashemi H, Pakzad R, Heydarian S, et al. (2019). Global and regional prevalence of strabismus: a comprehensive systematic review and meta-analysis. Strabismus. : Pooled prevalence of any strabismus was 1.93% across 56 studies and 229,396 participants.
- Multi-ethnic Pediatric Eye Disease Study Group (2008). Prevalence of amblyopia and strabismus in African American and Hispanic children ages 6 to 72 months. Ophthalmology. : In 6,014 preschool children, strabismus was found in 2.4-2.5% and amblyopia in 1.5-2.6%, with 78% of amblyopia attributable to refractive error.
- Fu Z, Hong H, Su Z, Lou B, Pan CW, Liu H (2020). Global prevalence of amblyopia and disease burden projections through 2040. British Journal of Ophthalmology. : Pooled global amblyopia prevalence was 1.44%, and 2.41% in North America, across 60 studies.
- Griepentrog GJ, Diehl N, Mohney BG (2013). Amblyopia in childhood eyelid ptosis. American Journal of Ophthalmology. : In a population-based series of 107 children with ptosis, amblyopia occurred in 14.9%, roughly 1 in 7, only about half of it from lid droop alone.
- Faiq M, Sharma R, Dada R, Mohanty K, Saluja D, Dada T (2013). Genetic, biochemical and clinical insights into primary congenital glaucoma. Journal of Current Glaucoma Practice. : Primary congenital glaucoma appears at birth or within the first year and presents with tearing, light sensitivity and eyelid squeezing, plus an enlarged eyeball and hazy cornea.
- American Optometric Association (2017). Evidence-Based Clinical Practice Guideline: Comprehensive Pediatric Eye and Vision Examination. : Evidence-based action statement recommending an in-person comprehensive eye and vision assessment for infants between 6 and 12 months of age (Grade B, Strong).
- American Optometric Association. Infant Vision: Birth to 24 Months of Age (patient education page). : States that depth perception is not present at birth and the eyes become capable of working together for three-dimensional vision at around the fifth month.
- American Academy of Ophthalmology (2026). Vision Development: Newborn to 12 Months (EyeSmart patient education page). : For the first 2 months the eyes may appear to cross or wander; by 3 months they should work together to focus and track; depth perception is more developed around 5 months.
- Donahue SP, Nixon CN; AAP Section on Ophthalmology, AAO, AAPOS, AACO (2016). Visual System Assessment in Infants, Children, and Young Adults by Pediatricians. Pediatrics. : AAP policy that visual assessment begins in the newborn nursery with inspection and red reflex, with instrument-based screening attempted from 12 months.
- US Preventive Services Task Force; Grossman DC, Curry SJ, Owens DK, et al. (2017). Vision Screening in Children Aged 6 Months to 5 Years. JAMA. : Recommends screening at least once at ages 3-5 for amblyopia and its risk factors, and finds the evidence insufficient to assess screening under age 3.
- Hutchinson AK, Morse CL, Hercinovic A, et al. (2023). Pediatric Eye Evaluations Preferred Practice Pattern. Ophthalmology. : Ophthalmology's position that comprehensive eye examinations are not necessary for healthy asymptomatic children who have passed an acceptable vision screening.
- Cruz OA, Repka MX, Hercinovic A, et al. (2023). Amblyopia Preferred Practice Pattern. Ophthalmology. : Optical correction alone improves acuity (good evidence) and most moderate amblyopia responds to about 2 hours a day of patching or weekend atropine; the panel found no convincing evidence for eye exercises as an amblyopia treatment.
- Pediatric Eye Disease Investigator Group (2002). A randomized trial of atropine vs. patching for treatment of moderate amblyopia in children. Archives of Ophthalmology. : In 419 children under 7, acuity improved 3.16 lines with patching and 2.84 lines with atropine at 6 months; both are appropriate first-line treatments.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.