What Can My Baby See? Vision in the First Year
“What can my baby actually see?” is one of the questions we hear most often at Vision & Learning Center. It is easy to picture a newborn going from the warm darkness of the womb into a loud, bright, blurry world and being overwhelmed by it. The research paints a calmer picture. Babies arrive with a small but working set of visual skills, and they start using them right away. How a baby uses those skills — whether they look, follow and hold a gaze — is one of the first things we pay attention to.
Here is what the first twelve months actually look like, and what is worth a phone call along the way.
Key takeaways
- Newborns see light, motion and bold light-dark patterns, and they follow face-shaped patterns from the first minutes of life.
- Detail vision is poor at birth and improves fast, reaching close to adult levels of grating resolution by around 8 months on some measures.
- Color discrimination builds gradually across the first three months.
- Depth perception from the two eyes working together (stereopsis) appears around 4 months and keeps refining for years.
- Most babies are not born with blue eyes, and most babies are farsighted, not nearsighted.
- The AOA recommends a first comprehensive eye examination between 6 and 12 months.
The newborn weeks: light, contrast and faces
A newborn detects light, gross shapes and movement. Fine detail is not there yet, and neither is much contrast sensitivity — which is exactly why babies stare at bold black-and-white patterns and at the high-contrast outline of a face against hair. Both resolution and contrast sensitivity climb steeply over the first three months (Banks & Salapatek, 1978).
Faces get special treatment from the very start. In a classic study, forty newborns with a median age of nine minutes turned their eyes and heads to follow a proper face pattern more than they followed scrambled versions of the same features (Goren et al., 1975). Your face, held close, is the most interesting thing in the room.
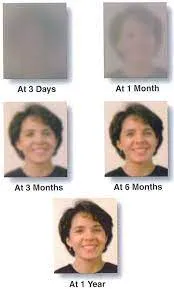 How a scene looks as acuity develops over the first year
How sharp is newborn vision, really?
Acuity in a baby is measured in one of two ways. One records the brain’s response to striped patterns. The other simply watches which way a baby chooses to look.
Those brain recordings put grating acuity at roughly 4.5 cycles per degree in the first month. Cycles per degree describes how fine a striped pattern the visual system can still make out, and a bigger number means finer stripes: at 4.5, only bold wide bars register; at 20, the pattern can be far finer. By 8 to 13 months babies reached about 20 cycles per degree — and by 8 months they were statistically indistinguishable from adults tested on the same equipment (Norcia & Tyler, 1985). Behavioral looking tests are the clinical counterpart. Teller Acuity Cards, which we use to check babies who cannot read a chart, have published norms running from 1 month to 4 years of age (Mayer et al., 1995). Whichever method is used, the direction is the same: blurry at birth, dramatically better within months.
One correction to a very common claim. Babies are usually farsighted, not nearsighted. In 514 healthy term-born children, hyperopia (farsightedness) was the norm and declined steadily with age. Myopia turned up in only 3%, and astigmatism of a diopter or more was most common in infancy (Mayer et al., 2001). Early blur is mostly an immature retina and visual brain, not a mismatched eyeball.
Focusing is imprecise early on too. In 1- to 3-month-olds the limits come mainly from sensory immaturity and a wide depth of focus, not from a weak focusing muscle (Banks, 1980). In practice that means a broad range of near distances all look about the same to a young baby. Holding your face close is still good advice; it is just not a precise eight-inch rule.
Two to four months: eyes team up, hands join in
Now a baby holds gaze longer, follows moving faces and objects with both eyes together, scans between several targets, and starts moving the eyes independently of the head. The American Optometric Association puts the milestone plainly. Babies should begin to follow moving objects with their eyes, and reach for things, at around three months. Eye-hand coordination develops as the infant tracks a moving object and reaches for it (AOA, Infant Vision). The aim is poor at first — that is normal. Looking, reaching and grasping train each other.
Alignment matters here. The American Academy of Ophthalmology notes that for the first two months the eyes often do not work together well, and may appear to cross or wander. By three months they should be working together to focus on and track an object (AAO, Vision Development: Newborn to 12 Months). A drift that persists after about four months, or an eye that always turns, is worth checking rather than waiting out.
Color arrives gradually
Color vision is not a switch that flips. Researchers test it with habituation: a baby is shown one color until interest fades, then shown a new one, and the researchers watch whether the change wins that attention back. The colors are matched for brightness so a baby cannot pass by noticing that one patch is simply lighter or darker. Tested this way, one-month-olds could tell red from green, but not either of those from yellow. Two-month-olds added green from yellow, and only at three months did red from yellow appear (Adams & Courage, 1995). A broader review concluded that color vision improves greatly across the first three postnatal months, and that most typical three-month-olds have at least some color vision. Much of the early limitation comes down to general insensitivity to contrast rather than to color itself (Brown, 1990).
Four to six months: depth perception arrives
Two eyes pointing at the same spot give the brain the small disparity it needs to build a three-dimensional view. Stereopsis first became demonstrable at a mean age of 16 weeks. By a mean of 21 weeks, stereoacuity reached 1 minute of arc or better (Held et al., 1980). A minute of arc is one sixtieth of a degree: a very small mismatch between what the two eyes see. On this scale, a smaller number means a finer sense of depth. The AOA puts it similarly: depth perception is not present at birth, and it is around the fifth month that the eyes become capable of a three-dimensional view (AOA, Infant Vision).
 The visual cliff, the classic laboratory test of infant depth perception
The famous visual cliff is often described as showing that babies “learn” depth once they crawl. The stronger finding is the opposite. Infants younger than crawling age produced reliable heart-rate deceleration when placed on the deep side, and not on the shallow side (Campos et al., 1970). In other words, they could already tell the two sides apart. They simply had no way to crawl away from the drop yet.
Depth perception is not finished in infancy, either. Stereoacuity keeps sharpening from about 100 arcseconds at age 3 to 40 arcseconds by age 7 (Birch et al., 2008). An arcsecond is one sixtieth of a minute of arc, so the average 7-year-old is picking up depth differences about two and a half times smaller than the average 3-year-old. Better stereoacuity also tracks with better fine-motor performance on tasks such as pegboards and bead threading (O’Connor et al., 2010). That is one reason we care how the two eyes work together, not only how each one reads a chart.
Six to twelve months: seeing to move
In the second half of the first year, vision becomes a whole-body activity. To look at something a baby has to orient the trunk, turn the head and point the eyes. Sitting, crawling and walking each change what is reachable and what is visible — eye height and head mobility literally change the view. The AOA marks the same shift: crawling at about 8 months “helps further develop eye-hand-foot-body coordination,” and by 9 to 12 months babies “can now judge distances fairly well and throw things with precision” (AOA, Infant Vision). This is where vision, balance and movement begin negotiating with each other, and it is the foundation for the visual-motor skills we assess later in childhood (more in our post on visual milestones).
About those blue eyes
Here is the myth we correct most often: babies are not all born blue-eyed. Among 192 healthy full-term newborns photographed with a standardized camera, 63.0% had brown irises, 20.8% blue, 5.7% green or hazel and 9.9% indeterminate (Ludwig et al., 2016).
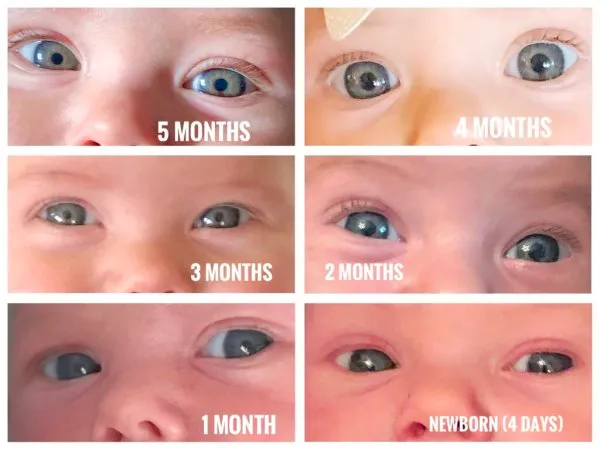 The same baby’s eyes from four days old to five months
What is true is that iris color can change over the first months as melanin is laid down. The AAO’s newborn-to-12-months guide says that at about 9 months a baby’s eye color is probably final, while adding that slight changes later are not uncommon (AAO, Vision Development). Longitudinal data adds a larger caveat. Most people had stable eye color by age 6, but 10 to 15% of the white subjects in the Louisville Twin Study changed further through adolescence and adulthood (Bito et al., 1997). And the old “two blue-eyed parents can’t have a brown-eyed child” rule is not how the genetics work. Iris color is polygenic, with roughly 74% of the variance traced to a single region of chromosome 15 (Sturm & Larsson, 2009). We go deeper in the evolution of eye color in babies.
When should a baby’s eyes be examined?
Two schedules coexist, and it helps to know which is which.
- Pediatrician screening. Under AAP policy, visual assessment starts in the nursery with external inspection and the red reflex. Instrument-based screening is then attempted between 12 months and 3 years and at annual well-child visits, and a child who fails is referred on (Donahue & Nixon, 2016). The US Preventive Services Task Force recommends screening at least once at ages 3 to 5 for amblyopia and its risk factors. It found the evidence insufficient to recommend screening under age 3 (USPSTF, 2017).
- Comprehensive examination. The AOA recommends a first comprehensive eye and vision examination between 6 and 12 months. After that it recommends another between 3 and 5 years, one before first grade, and annual exams from then on (AOA pediatric guideline, 2017).
Our clinical perspective at Vision & Learning Center is that both belong in a child’s life. Screening catches a great deal, and a full examination looks at things a screening is not designed to find. A baby exam does not require reading a chart. We check fixation and following, eye alignment, pupil responses and eye health, and we measure the focus of each eye with retinoscopy while the child sits on a parent’s lap.
Signs worth a call before the next milestone
- A white, dull or unusual reflection in the pupil in photographs
- An eye that consistently turns in or out after about four months
- No following of faces or objects by three months
- Constant tearing, crusting, redness or strong light sensitivity
- A droopy eyelid that covers part of the pupil
- Shaking or jerking eye movements
- A family history of childhood strabismus, amblyopia, cataract or retinoblastoma
The AOA lists several of these as signs of possible eye and vision problems in infants: excessive tearing, red or encrusted eyelids, constant eye turning, extreme sensitivity to light, and the appearance of a white pupil (AOA, Infant Vision).
None of these means something is wrong; each means we would rather look. For context, in a Los Angeles population study of African American and Hispanic/Latino children aged 6 to 72 months, strabismus was found in 2.4 to 2.5% and amblyopia in 1.5 to 2.6%. Most of the amblyopia — 78% of it — was traced to refractive error (MEPEDS, 2008). Those two conditions, an eye that turns and an eye that does not develop clear sight, are what our amblyopia and strabismus care is built around. Age does matter for amblyopia treatment, though not as a cliff. Pooling four randomized trials, children aged 7 to under 13 were significantly less responsive than younger children, and yet “some children show a marked response to treatment” at that age (Holmes et al., 2011). In a trial of 507 children aged 7 to 17, 53% of the 7- to 12-year-olds responded to patching plus near activities, versus 25% given glasses alone (PEDIG, 2005). Earlier is easier; later is not hopeless. Our parent’s guide to common eye problems in babies 0-18 months covers each in more detail, and milestones for visual-spatial development covers what comes next.
If your baby is between 6 and 12 months, or if anything on the list above sounds familiar at any age, we would be glad to take a look. Learn what happens at a comprehensive eye examination, or Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
Can newborns see anything at all?
Yes. Newborns detect light, movement and bold light-dark patterns, and they will turn their eyes and head to follow a face-shaped pattern within minutes of birth (Goren et al., 1975). Fine detail comes much later.
Is it normal for my baby's eyes to cross or drift?
In the first two months an infant's eyes often do not work together well and may look crossed or wander, according to the American Academy of Ophthalmology. By about three months the eyes should work together to focus and follow. Eye turning that persists past that, or an eye that always turns, should be examined.
Are all babies born with blue eyes?
No. In a study of 192 healthy full-term newborns, 63% had brown irises and only about 21% were blue (Ludwig et al., 2016). Eye color is polygenic, and while most children settle on a color early, 10 to 15% of the white participants in the Louisville Twin Study changed further through adolescence and adulthood (Bito et al., 1997).
When should my baby have a first eye exam?
The American Optometric Association recommends a first comprehensive eye and vision examination between 6 and 12 months of age, then again between 3 and 5 years, and before first grade. Pediatrician screening begins in the nursery with inspection and the red reflex (AAP, 2016); our clinical perspective at Vision & Learning Center is that a screening and a full examination do different jobs, so both belong in a child's life.
What signs should make me call sooner?
A white or dull pupil in photos, an eye that consistently turns in or out after about four months, constant tearing or light sensitivity, a droopy lid covering the pupil, shaking eyes, no following of faces or toys by three months, or a family history of childhood eye disease. Any of these deserves a prompt evaluation.
Where This Information Comes From
- Norcia AM, Tyler CW (1985). Spatial frequency sweep VEP: visual acuity during the first year of life. Vision Research. : In 197 infants, VEP grating acuity rose from about 4.5 cycles/degree in the first month to about 20 cycles/degree at 8-13 months, near adult levels by 8 months.
- Mayer DL, Beiser AS, Warner AF, et al. (1995). Monocular acuity norms for the Teller Acuity Cards between ages one month and four years. Investigative Ophthalmology & Visual Science. : Clinical grating-acuity norms from 460 children aged 1 month to 4 years, the basis for testing acuity in babies who cannot read a chart.
- Banks MS, Salapatek P (1978). Acuity and contrast sensitivity in 1-, 2-, and 3-month-old human infants. Investigative Ophthalmology & Visual Science. : Cut-off spatial frequency rose from 2.4 to 4.0 cycles/degree between 1 and 3 months, with overall contrast sensitivity improving across the same window.
- Goren CC, Sarty M, Wu PY (1975). Visual following and pattern discrimination of face-like stimuli by newborn infants. Pediatrics. : Forty newborns of median age 9 minutes followed a proper face pattern with eyes and head more than scrambled or blank versions of it.
- Banks MS (1980). The development of visual accommodation during early infancy. Child Development. : Focusing accuracy in 1- to 3-month-olds is limited mainly by sensory immaturity and a large depth of focus rather than by the focusing muscle itself.
- Mayer DL, Hansen RM, Moore BD, Kim S, Fulton AB (2001). Cycloplegic refractions in healthy children aged 1 through 48 months. Archives of Ophthalmology. : In 514 healthy term-born children, hyperopia (farsightedness) declined with age; myopia was rare at 3% and astigmatism of 1 D or more was most common in infancy.
- Adams RJ, Courage ML (1995). Development of chromatic discrimination in early infancy. Behavioural Brain Research. : Chromatic discrimination emerges gradually: red from green at 1 month, green from yellow at 2 months, red from yellow only at 3 months.
- Brown AM (1990). Development of visual sensitivity to light and color vision in human infants: a critical review. Vision Research. : Color vision improves greatly over the first three postnatal months and most normal 3-month-olds have at least some color vision; general contrast insensitivity explains much of the early limitation.
- Held R, Birch E, Gwiazda J (1980). Stereoacuity of human infants. Proceedings of the National Academy of Sciences USA. : Stereopsis first became demonstrable at a mean age of 16 weeks and reached 1 minute of arc or better by a mean of 21 weeks.
- Campos JJ, Langer A, Krowitz A (1970). Cardiac responses on the visual cliff in prelocomotor human infants. Science. : Infants younger than crawling age showed reliable heart-rate deceleration on the deep side of the visual cliff, showing they discriminate depth before they can crawl away from it.
- O'Connor AR, Birch EE, Anderson S, Draper H (2010). The functional significance of stereopsis. Investigative Ophthalmology & Visual Science. : In 143 people aged 10-30, pegboard and bead-threading performance tracked stereoacuity, with normal stereo performing best on every task.
- Birch E, Williams C, Drover J, et al. (2008). Randot Preschool Stereoacuity Test: normative data and validity. Journal of AAPOS. : In 4,355 children, mean stereoacuity improved from 100 arcsec at age 3 to 40 arcsec by age 7 - depth perception keeps refining well past infancy.
- Ludwig CA, Callaway NF, Fredrick DR, Blumenkranz MS, Moshfeghi DM (2016). What colour are newborns' eyes? Prevalence of iris colour in the Newborn Eye Screening Test (NEST) study. Acta Ophthalmologica. : Among 192 healthy full-term newborns, iris colour was 63.0% brown, 20.8% blue, 5.7% green/hazel and 9.9% indeterminate.
- Bito LZ, Matheny A, Cruickshanks KJ, Nondahl DM, Carino OB (1997). Eye color changes past early childhood. The Louisville Twin Study. Archives of Ophthalmology. : Most of 1513 twins reached stable eye color by age 6, but 10-15% of white subjects changed further through adolescence and adulthood.
- Sturm RA, Larsson M (2009). Genetics of human iris colour and patterns. Pigment Cell & Melanoma Research. : Eye colour is polygenic, with roughly 74% of variance explained by one region of chromosome 15 containing OCA2 and the HERC2 variant rs12913832.
- American Academy of Ophthalmology. Vision Development: Newborn to 12 Months. aao.org EyeSmart patient education page. : For the first 2 months the eyes may appear crossed or wander; by 3 months they should work together to focus and track; at about 9 months eye color is probably final, though slight later changes are not uncommon.
- American Optometric Association. Infant Vision: Birth to 24 Months of Age. aoa.org patient education page. : Depth perception is not present at birth and the eyes are not capable of a three-dimensional view until around the fifth month; a first thorough eye examination is recommended at about 6 months.
- American Optometric Association (2017). Evidence-Based Clinical Practice Guideline: Comprehensive Pediatric Eye and Vision Examination. : Recommends a comprehensive eye examination at 6-12 months, at least once between 3 and 5 years, and before first grade with annual exams thereafter.
- Donahue SP, Nixon CN; AAP Section on Ophthalmology and partner organizations (2016). Visual System Assessment in Infants, Children, and Young Adults by Pediatricians. Pediatrics. : AAP policy: visual assessment begins in the nursery with inspection and red reflex, with instrument-based screening attempted from 12 months to 3 years and at annual well-child visits.
- US Preventive Services Task Force; Grossman DC, Curry SJ, Owens DK, et al. (2017). Vision Screening in Children Aged 6 Months to 5 Years. JAMA. : Recommends screening at least once at ages 3-5 for amblyopia and its risk factors (B), and finds evidence insufficient to screen children under 3 (I statement).
- Multi-ethnic Pediatric Eye Disease Study Group (2008). Prevalence of amblyopia and strabismus in African American and Hispanic children ages 6 to 72 months. Ophthalmology. : In 6014 African American and Hispanic/Latino children aged 6-72 months in Los Angeles County, strabismus was present in 2.4-2.5% and amblyopia in 1.5-2.6%, with 78% of amblyopia attributable to refractive error.
- Holmes JM, Lazar EL, Melia BM, et al.; Pediatric Eye Disease Investigator Group (2011). Effect of age on response to amblyopia treatment in children. Archives of Ophthalmology. : Pooling four randomized trials, children aged 7 to under 13 responded less well to amblyopia treatment than younger children, though some older children still showed a marked response.
- Scheiman MM, Hertle RW, Beck RW, et al.; Pediatric Eye Disease Investigator Group (2005). Randomized trial of treatment of amblyopia in children aged 7 to 17 years. Archives of Ophthalmology. : In 507 children aged 7-17, 53% of 7- to 12-year-olds responded to patching plus near activities versus 25% treated with optical correction alone.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.