BVD in School-Aged Children: A Guide for Parents
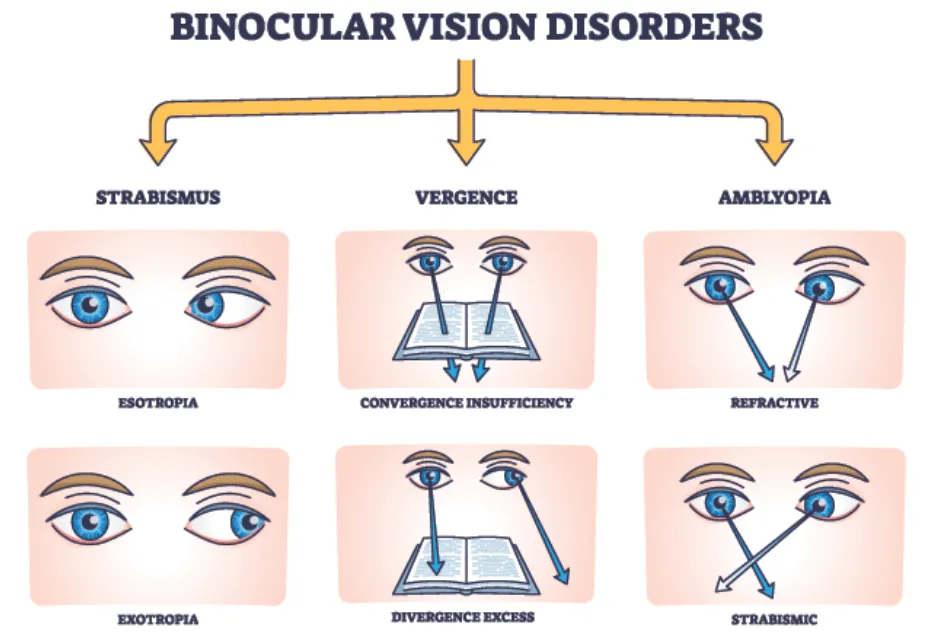
Every school year we meet children who are bright, curious and genuinely trying, and who still dread reading. They lose their place, rub their eyes, get a headache by mid-afternoon, or hand in half a worksheet. Sometimes the explanation is not effort or attention at all. It is that the two eyes are not working together comfortably at near.
Clinicians group those problems under the umbrella term binocular vision dysfunction, or BVD. Our complete guide to binocular vision dysfunction covers the whole picture; this article is written for the people who see a school-aged child every day, at the kitchen table and in the classroom.
Key takeaways
- BVD is an umbrella for several measurable eye-teaming and focusing problems, not one diagnosis. There is no dependable prevalence figure for the umbrella, so we do not quote one.
- Its best-studied member is convergence insufficiency: about 13% of fifth- and sixth-graders in a school-based US study met a high-suspect or definite definition (Rouse et al., 1999).
- The symptoms overlap with inattention, and children with convergence insufficiency report more school-behavior problems even when nobody has mentioned ADHD (Rouse et al., 2009).
- Office-based vision therapy has strong placebo-controlled evidence for symptomatic convergence insufficiency in children (CITT, 2008) and, in the larger CITT-ART trial, no symptom advantage over placebo (CITT-ART, 2019) and no proven benefit for reading scores (CITT-ART, 2019). Both facts belong in the same conversation.
- Classroom accommodations reduce the visual load. They are supports, not treatment, and only an examination can say what is actually going on.
What binocular vision dysfunction means
Each eye sends the brain a slightly different image, and the brain fuses the two into one. That fusion is what makes print sit still and look single. Most children have a small resting misalignment the system corrects automatically. Trouble starts when holding the two images together at reading distance costs more effort than the system can comfortably supply.
Under the BVD umbrella sit several conditions an examination can actually measure: convergence insufficiency (the eyes struggle to turn in and hold a near target), accommodative insufficiency or infacility (focusing is weak or slow to shift), vertical heterophoria (a small up-and-down misalignment), and ocular motor dysfunction (inaccurate tracking across a line of print). They travel together often. In the CITT trial, 74% of children with symptomatic convergence insufficiency also had an accommodative problem (Scheiman et al., 2011).
BVD is also not the same as needing glasses: a child can read the 20/20 line on the wall chart and still be miserable eight inches from a book.
Signs parents and teachers notice
Children rarely say “my eyes will not team.” They say homework is boring, or say nothing at all, because the way they see is the only way they have ever seen. What adults notice instead:
- Eye rubbing, squinting, or one eye closing or covering during near work
- Headaches, especially late in the school day or after reading
- Losing place, skipping lines, using a finger long after peers stopped
- Words that blur, swim, or briefly go double
- Avoiding reading, homework or fine detail, or fatiguing quickly at it
- Clumsy handwriting spacing, poor copying from the board, motion sickness or dizziness in busy rooms
Researchers score these with the Convergence Insufficiency Symptom Survey, which separated children with CI (mean 30.8) from children with normal binocular vision (mean 8.4) at a cut-off of 16 (Borsting et al., 2003). It is a validated research measure, not a home diagnostic test. If the list sounds like your child, that is a reason to be examined, not a conclusion.
Why it gets mistaken for an attention problem
From the front of a classroom, a child who cannot hold a near target comfortably and a child who will not stay on task can look like the same child. Three separate studies show how often the two turn up together. A pediatric ophthalmology practice reviewed 266 charts of patients with convergence insufficiency and found that 26 of them, 9.8%, had been diagnosed with ADHD at some point in their care; running the search the other way put CI at 15.9% of the ADHD records (Granet et al., 2005). A national survey of 75,171 children aged 4 to 17 found current ADHD reported for 15.6% of the children whose parents described a vision problem that glasses or contacts could not correct, against 8.3% of children with normal vision, an association that held at an odds ratio of 1.8 after adjusting for other factors (DeCarlo et al., 2016). And when CITT researchers asked parents about schoolwork behaviors, the children who had symptomatic CI but no reported ADHD still scored higher than children with normal binocular vision, 11.7 against 8.7 on a 24-point scale (Rouse et al., 2009).
None of that shows vision causes ADHD; it shows the two travel together. Vision therapy is not a treatment for ADHD, and a vision evaluation does not stand in for a developmental or psychological one. What the overlap does argue for is measuring how the eyes work at near before “won’t pay attention” is accepted as the whole story, which we walk through in vision problems versus ADHD.
What the treatment evidence shows, and what it does not
For symptomatic convergence insufficiency in children, the evidence is unusually good. In the 221-child CITT, 73% were successful or improved after 12 weeks of office-based vergence and accommodative therapy with home reinforcement, versus 35% on office placebo (CITT, 2008). Of those who became asymptomatic, 84.4% of the office-therapy group still were a year later (CITT, 2009), and a Cochrane review of 12 trials, six of them in children, reached the same conclusion (Scheiman et al., 2020).
The later, larger CITT-ART trial complicates that picture, and parents deserve it in full. Clinical signs improved much more with therapy than placebo, but symptom scores improved about equally in both groups (CITT-ART, 2019), and reading comprehension improved 3.7 points with therapy versus 3.8 with placebo: no reading benefit at all (CITT-ART, 2019).
The wider reading question is genuinely contested. The AAP, AAO, AAPOS and AACO joint statement holds that dyslexia is language-based and that vision therapy is not supported for learning disabilities (AAP et al., 2009), and a 5,822-child cohort found four of five severely impaired readers had normal ophthalmic function (Creavin et al., 2015). The optometric bodies read the same landscape differently, holding that vision problems can and often do interfere with learning and that optometric care is one part of a multidisciplinary approach (AAO/AOA, 1997). Our position, offered as clinical perspective rather than trial evidence: vision problems do not cause dyslexia and we do not treat reading, but some struggling readers also have a treatable eye-teaming or focusing problem that makes near work uncomfortable, and finding that is our job.
Classroom supports that lower the visual load
These help a child cope while the underlying question is sorted out. They are accommodations, not treatment.
- Extra time on reading assignments and tests, so speed does not penalize comfort.
- Scheduled breaks from near work, looking across the room between tasks.
- Print and seating: larger type, wider line spacing, a clear line of sight to the board.
- Audio and text-to-speech to carry content while reading instruction continues at full strength.
- Movement and coordination activities, which most children benefit from anyway.
Getting an answer
School screenings are worth doing and are not the whole story. The AOA’s pediatric guideline recommends a comprehensive examination before first grade and annually after, and reports that distance acuity testing alone missed 75.5% of children later found to have binocular and oculomotor problems (AOA, 2017). A developmental evaluation adds eye teaming, focusing, tracking and depth measurements to the acuity and health check.
If reading, headaches or attention at school have you wondering, a comprehensive developmental vision evaluation is the way to find out what is true for your child. Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
How common is binocular vision dysfunction in school-aged children?
There is no reliable prevalence figure for BVD as a category, so we do not quote one. The best-studied member of the group is convergence insufficiency: in a school-based US study of 453 fifth- and sixth-graders, about 13% met a high-suspect or definite CI definition, and 78.9% of those with three-sign CI also had an accommodative (focusing) problem.
Can my child have 20/20 eyesight and still have BVD?
Yes. An acuity chart measures how small a letter one eye can resolve at distance. It does not measure how the two eyes team up, how well focusing holds at reading distance, or how accurately the eyes track a line of print. That is why a comprehensive examination looks at more than the letters on the wall.
Is BVD the same thing as ADHD, or does it cause ADHD?
No. The two overlap statistically but they are separate. Children with convergence insufficiency are more likely to carry an ADHD diagnosis, and children with a vision problem that glasses cannot correct are reported to have ADHD roughly twice as often as children without one. These are associations, not causes, and vision therapy is not a treatment for ADHD.
Does treating convergence insufficiency improve my child's reading scores?
The evidence says no. CITT-ART, a 310-child randomized trial, found reading comprehension improved 3.7 points with office-based vision therapy and 3.8 points with placebo therapy. We treat eye teaming and focusing so near work is more comfortable; reading instruction still belongs to teachers and reading specialists.
What should I do if the school screening said my child passed?
A passed screening is reassuring but not conclusive. The AOA's pediatric guideline reports that distance acuity testing alone missed 75.5% of children later found to have binocular and oculomotor problems on a full examination. If the symptoms persist, ask for a comprehensive developmental vision evaluation.
Where This Information Comes From
- Rouse MW, Borsting E, Hyman L, et al.; CIRS Group (1999). Frequency of convergence insufficiency among fifth and sixth graders. Optometry and Vision Science. : In 453 fifth- and sixth-graders, 4.2% had definite and 8.8% high-suspect convergence insufficiency (about 13% combined); 78.9% of three-sign CI children also had accommodative insufficiency.
- Borsting EJ, Rouse MW, Mitchell GL, et al.; CITT Group (2003). Validity and reliability of the revised convergence insufficiency symptom survey in children aged 9 to 18 years. Optometry and Vision Science. : Mean CISS score 30.8 in children with CI versus 8.4 in children with normal binocular vision; a cut-off of 16 gave 96% sensitivity and 88% specificity as a research outcome measure.
- Rouse M, Borsting E, Mitchell GL, et al.; CITT Study Group (2009). Academic behaviors in children with convergence insufficiency with and without parent-reported ADHD. Optometry and Vision Science. : Parents reported ADHD in 16% of 212 children with symptomatic CI versus 6% of 49 controls; children with CI but no reported ADHD still scored higher on the 24-point Academic Behavior Survey than children with normal binocular vision (11.7 vs 8.7, p=0.036).
- Granet DB, Gomi CF, Ventura R, Miller-Scholte A (2005). The relationship between convergence insufficiency and ADHD. Strabismus. : Of 266 CI patients, 9.8% carried an ADHD diagnosis, and CI was found in 15.9% of ADHD records; a retrospective chart review describing association, not causation.
- DeCarlo DK, Swanson M, McGwin G, Visscher K, Owsley C (2016). ADHD and vision problems in the National Survey of Children's Health. Optometry and Vision Science. : In 75,171 children aged 4-17, ADHD was reported in 15.6% of those with a vision problem not correctable with glasses or contacts versus 8.3% of those without (adjusted odds ratio 1.8); parent-reported and cross-sectional.
- Convergence Insufficiency Treatment Trial Study Group (2008). Randomized clinical trial of treatments for symptomatic convergence insufficiency in children. Archives of Ophthalmology. : In 221 children aged 9-17, 73% were successful or improved after 12 weeks of office-based vergence/accommodative therapy versus 35% with office placebo and 33-43% with home programs.
- Convergence Insufficiency Treatment Trial Study Group (2009). Long-term effectiveness of treatments for symptomatic convergence insufficiency in children. Optometry and Vision Science. : Among children who became asymptomatic on the 12-week program, 84.4% of the office-based therapy group were still asymptomatic one year later; only responders were followed.
- CITT-ART Investigator Group (2019). Treatment of symptomatic convergence insufficiency in children enrolled in the CITT-Attention & Reading Trial. Optometry and Vision Science. : In 311 children, near point of convergence and fusional vergence improved far more with therapy than placebo, but symptom scores improved similarly in both groups (11.8 vs 10.4 points, p=.21).
- CITT-ART Investigator Group (2019). Effect of vergence/accommodative therapy on reading in children with convergence insufficiency: a randomized clinical trial. Optometry and Vision Science. : In 310 children with symptomatic CI, reading comprehension improved 3.7 points with 16 weeks of office-based therapy versus 3.8 points with placebo therapy: no reading benefit.
- Scheiman M, Kulp MT, Cotter SA, Lawrenson JG, Wang L, Li T (2020). Interventions for convergence insufficiency: a network meta-analysis. Cochrane Database of Systematic Reviews. : Across 12 trials and 1,289 participants, office-based vergence/accommodative therapy with home reinforcement beat placebo in children (risk ratio 3.04); adult evidence is less clear.
- Scheiman M, Cotter S, Kulp MT, et al.; CITT Study Group (2011). Treatment of accommodative dysfunction in children: results from a randomized clinical trial. Optometry and Vision Science. : 74% of CITT children with symptomatic CI also had accommodative dysfunction; accommodative amplitude rose 9.9 D with office-based therapy versus 2.2 D with placebo.
- Creavin AL, Lingam R, Steer C, Williams C (2015). Ophthalmic abnormalities and reading impairment. Pediatrics. : In 5,822 children aged 7-9, four of every five with severe reading impairment had normal ophthalmic function, with no association found for convergence or accommodation.
- American Academy of Pediatrics, American Academy of Ophthalmology, AAPOS, AACO (2009). Joint statement: learning disabilities, dyslexia, and vision. Pediatrics. : Holds that dyslexia is language-based, that vision problems can interfere with learning but do not cause dyslexia, and that evidence does not support vision therapy as a treatment for learning disabilities.
- American Academy of Optometry; American Optometric Association (1997). Vision, learning and dyslexia: a joint organizational policy statement. Journal of the American Optometric Association. : The optometric position: vision problems can and often do interfere with learning, and optometric care is one part of a multidisciplinary approach; a professional policy statement, not an evidence review.
- American Optometric Association (2017). Evidence-based clinical practice guideline: comprehensive pediatric eye and vision examination. : Recommends a comprehensive examination before first grade and annually thereafter, and reports that Snellen acuity alone missed 75.5% of children found to have binocular and oculomotor problems.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.