Migraines and Binocular Vision Dysfunction: The Link
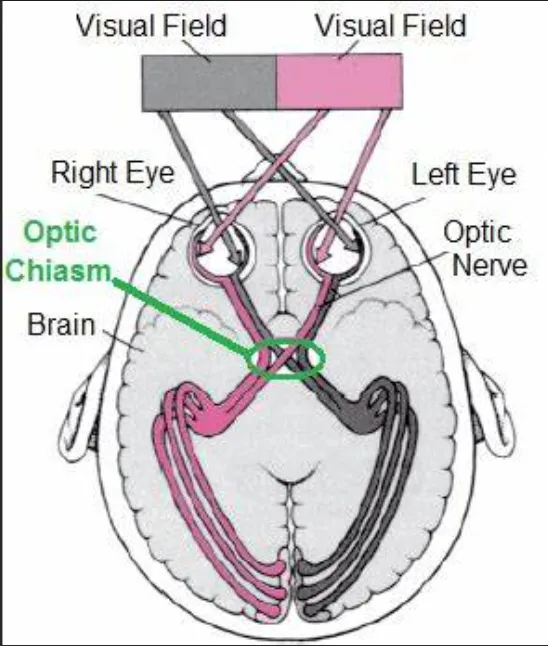
Migraine is common and genuinely disabling. A large review of population studies put the global prevalence of migraine at 14.0%, with some form of active headache disorder affecting about 52% of people and 15.8% of the world’s population reporting a headache on any given day (Stovner et al., 2022). So when someone with frequent migraines asks whether their eyes might be involved, it is a fair question — and it deserves a fair answer rather than a sales pitch.
Key takeaways
- Migraine is a neurological disorder. Binocular vision dysfunction (BVD) does not cause it, and we do not claim otherwise.
- People with migraine do show small differences in eye teaming compared with controls, but the researchers who measured them concluded the differences were too subtle to justify binocular vision treatment on the strength of a migraine diagnosis alone (Harle & Evans, 2006).
- Visual triggers are real. Patterns, glare and flicker cluster together as one of the main trigger groups in migraine (Harle et al., 2006), and light sensitivity between attacks is well documented (Hayne & Martin, 2019).
- Astigmatism and uncorrected prescriptions turn up more often in people with migraine, which is a good reason to keep your glasses current (Harle & Evans, 2006).
- Prism evidence for vertical heterophoria is retrospective and uncontrolled. Treat it as promising, not proven.
What binocular vision dysfunction means
Each eye sends the brain a slightly different picture, and the brain fuses the two into one comfortable, three-dimensional image. Most people have a small resting misalignment that the eye-teaming system corrects without you noticing. Trouble starts when holding those images together takes more effort than the system can supply comfortably.
Inside the BVD umbrella sit several problems an examination can actually measure:
- Convergence insufficiency — the eyes struggle to turn inward and stay there for near work. It is the best-studied member of the group.
- Accommodative dysfunction — the focusing system is weak, slow, or hard to sustain.
- Vertical heterophoria — a small vertical misalignment between the two eyes.
- Ocular motor dysfunction — inaccurate tracking and eye jumps.
- Strabismus and amblyopia — a visible eye turn, or one eye that never developed normal vision, both of which disrupt teamwork.
Our complete guide to binocular vision dysfunction walks through each of these in more detail, and vertical heterophoria has its own page.
How eye strain and head pain interact
The plausible mechanism is straightforward. When the eyes need constant extra effort to stay aligned and focused, near work becomes uncomfortable, and that discomfort is typically described as sitting around and behind the eyes, across the forehead, or in the temples. Adults with symptomatic convergence insufficiency score dramatically higher on a validated symptom questionnaire than people with normal eye teaming — an average of 37.3 versus 11.0 (Rouse et al., 2004) — and headache and eye ache are among the survey’s items. Screens raise the stakes: digital eye strain affects roughly half or more of computer users, and its symptoms split into a focusing-and-eye-teaming group and a dry-eye group (Sheppard & Wolffsohn, 2018).
What we cannot honestly say is that this strain generates a migraine. That is where the popular version of this story gets ahead of the evidence.
What the research actually shows
Binocular differences in migraine are real but subtle
The best test of the idea is a masked case-control study that compared people with migraine to controls using standard clinical binocular vision tests. Heterophoria and fixation disparity were somewhat more common in the migraine group, stereopsis was slightly reduced, and an aligning prism — the small amount of prism used on a clinical test to neutralise a fixation disparity — was measured more often. That is a measurement, not a prescription. But the differences were modest, correlations did not establish causation, and the authors’ own conclusion was that the evidence does not justify prescribing binocular vision treatment on the basis of a migraine diagnosis alone (Harle & Evans, 2006). We think that is the honest headline, and we say so even though we are the people who provide the treatment.
Prescription matters more than most people expect
The same researchers compared refractive error between groups and found higher degrees of astigmatism — measured both objectively and subjectively — along with more uncorrected astigmatism in the migraine group. Anisometropia, a difference in prescription between the two eyes, only trended in that direction and did not reach statistical significance (p = 0.06); astigmatism was the paper’s clearest finding. Their practical recommendation was simply that people with migraine see their optometrist regularly so that refractive errors stay properly corrected (Harle & Evans, 2006).
The international headache classification takes a similar line. It recognises a diagnosis of headache attributed to refractive error, typically provoked by prolonged visual tasks and relieved by correcting the error, while noting plainly that refractive error is “much less commonly a cause of headache than is generally believed” (ICHD-3, 2018). Worth knowing: the classification’s eye-related headache category covers glaucoma, refractive error, ocular inflammation and trochlear headache — there is no listed category for headache attributed to eye misalignment.
Visual triggers, glare and pattern sensitivity
Where vision clearly earns a place in the migraine conversation is as a trigger. In a study of pattern glare and visual stress, people with migraine reported significantly more distortion and discomfort when viewing striped patterns, more often chose coloured filters (usually in the blue-to-green range), and showed subtle colour-vision differences. A principal component analysis of common headache triggers produced five roughly equal groups: food, visual triggers, alcohol, stress and tiredness, and the environment (Harle et al., 2006). Visual triggers, in other words, sit alongside the classic ones rather than beneath them.
Blurry vision, eye pain and sensitivity to light
Blurred or doubled vision late in the day, aching around or behind the eyes, and light that feels punishing are the three complaints people most often bring us after a migraine work-up has come back clear.
Blur and eye ache respond well to measurement. If the focusing system fatigues or the eyes drift apart at near, blur that comes and goes with effort is expected, and an examination can quantify it.
Light sensitivity is different. Photophobia is a core migraine feature, and it persists between attacks for many people. In a study of 491 participants, headache patients with photophobia reported significantly greater everyday light sensitivity than headache patients without photophobia and than controls, and the same pattern held for flicker and glare as triggers, although visual aura did not follow suit (Hayne & Martin, 2019). So when light bothers you, migraine itself is the most likely explanation. Eye strain may lower your tolerance further; it is rarely the whole story.
How we evaluate eye teaming
A standard eye exam checks whether each eye sees clearly. A developmental vision evaluation adds the questions a migraine work-up does not ask:
- Cover test and phoria measurement — how the eyes align at distance and near, horizontally and vertically.
- Near point of convergence and fusional vergence ranges — how far in the eyes can converge and how much stress the fusion system tolerates.
- Accommodative amplitude and facility — how strongly and how quickly focus shifts.
- Stereoacuity — depth perception, which was mildly reduced in the migraine group above.
- Tracking and saccades — accuracy of pursuit and eye jumps.
- A careful refraction — including small astigmatic and anisometropic corrections that get skipped elsewhere.
If your headaches began after a head injury, that history changes the evaluation. The AAP and its ophthalmology partners note that most children recover from concussion within about four weeks, and that those who do not warrant a vision-specific history and examination covering convergence and accommodation (Master et al., 2022).
Treatment, and what each option can honestly claim
Vision therapy. For symptomatic convergence insufficiency in children, office-based vergence and accommodative therapy has the strongest evidence in this field: 73% successful or improved at 12 weeks versus 35% with office placebo therapy (CITT, 2008), confirmed by a Cochrane network meta-analysis (Scheiman et al., 2020). Two honest caveats belong beside it: in the later CITT-ART trial the clinical signs improved much more with therapy but symptom scores improved about equally in the therapy and placebo groups (CITT-ART, 2019), and the adult evidence is thinner. We are aware of no controlled trial testing vision therapy as a migraine treatment.
Prism. Base-in prism reading lenses beat placebo lenses in a small randomized crossover trial of presbyopic adults (Teitelbaum et al., 2009) but were no better than placebo in children (Scheiman et al., 2005). The widely publicised vertical-prism results — a 71.8% drop in symptom burden in 43 brain-injury patients (Doble et al., 2010) and 19.1–60.8% reductions on headache, dizziness and anxiety measures in 38 post-concussion patients (Rosner et al., 2016) — come from retrospective, uncontrolled series at a single private practice, which also developed the questionnaire used to select patients (Feinberg et al., 2021). We compare what each approach is actually for in prism glasses vs vision therapy.
Getting the prescription right. Given the astigmatism findings above, an accurate, current correction is the cheapest thing worth trying.
Working conditions. Regular breaks from sustained near work, better task lighting, reduced glare and screen contrast that suits you address the visual-trigger side directly.
Our clinical perspective
Here is how we hold all of this at Vision & Learning Center. Migraine belongs to your physician or neurologist, and a new, sudden, severe or unfamiliar headache needs medical attention before anything else. Our job is narrower and, we think, useful: to find out whether a measurable focusing, eye-teaming or prescription problem is adding avoidable visual strain on top of a migraine pattern — and to treat that, on its own merits, without claiming the migraines were an eye problem all along. Some people leave with a small lens change, some with a therapy plan, and some with a clear answer that their eyes are not the issue. All three are good outcomes.
If headaches, blurry vision or light sensitivity keep interrupting your work, your reading or your family life, learn more about headaches and vision and binocular vision dysfunction in adults, then schedule a comprehensive developmental vision evaluation so we can measure what is actually happening. Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
Can binocular vision dysfunction cause migraines?
No study shows that it causes them. Migraine is a primary neurological disorder. What the research does show is that people with migraine have slightly more heterophoria, fixation disparity and reduced stereopsis than controls, and that the authors of that study concluded the differences were too small to justify treating binocular vision on the basis of a migraine diagnosis alone. An uncorrected or uncompensated eye problem can still add a second, separate headache on top of migraine, and that part is worth checking.
Why does light bother me so much between migraine attacks?
Interictal light sensitivity is well described in migraine itself. In a study of 491 people, those with photophobia reported significantly higher everyday light sensitivity than headache patients without photophobia and than controls, and the same pattern held for flicker and glare as headache triggers. Eye strain can make bright or flickering environments harder to tolerate, but light sensitivity in migraine is largely a migraine phenomenon.
Will prism glasses stop my migraines?
We cannot promise that, and no controlled trial supports it. Base-in prism reading lenses helped presbyopic adults with convergence insufficiency in a small randomized crossover trial, but did no better than placebo lenses in children. The prism evidence in vertical heterophoria comes from retrospective, uncontrolled case series from a single private practice. Prism is a reasonable thing to trial for the right findings; it is not a migraine treatment.
Could my prescription be part of the problem?
It is worth ruling out. A masked case-control study found higher degrees of astigmatism and more uncorrected astigmatism in people with migraine; anisometropia (a difference in prescription between the two eyes) showed only a non-significant trend (p = 0.06). The authors recommended regular optometric care so that refractive errors stay properly corrected. The international headache classification also recognises headache attributed to refractive error, while noting it is a less common cause than most people assume.
Should I see a neurologist or an eye doctor?
For migraine, both roles are legitimate and neither replaces the other. Migraine diagnosis and medical management belong with your physician or neurologist. A developmental vision evaluation answers a narrower question: is there a measurable focusing, eye-teaming or prescription problem adding to your visual discomfort? A new, sudden, severe or unusually different headache needs urgent medical attention first.
Where This Information Comes From
- Stovner LJ, Hagen K, Linde M, Steiner TJ (2022). The global prevalence of headache: an update, with analysis of the influences of methodological factors on prevalence estimates. The Journal of Headache and Pain; 23(1):34. : Estimated global prevalence of active headache disorder 52.0% and of migraine 14.0%; 15.8% of the world's population has headache on any given day.
- Harle DE, Evans BJW (2006). Subtle binocular vision anomalies in migraine. Ophthalmic and Physiological Optics; 26(6):587-596. : Masked case-control study: heterophoria, fixation disparity and aligning prism were slightly more prevalent and stereopsis slightly reduced in migraine, but differences were small and the authors did not support binocular vision interventions prescribed solely on the basis of migraine.
- Harle DE, Evans BJW (2006). The correlation between migraine headache and refractive errors. Optometry and Vision Science; 83(2):82-87. : Masked case-control study finding higher degrees of astigmatism (p = 0.01-0.05) and more uncorrected astigmatism in the migraine group; anisometropia was a non-significant trend (p = 0.06). Recommends regular optometric care.
- Harle DE, Shepherd AJ, Evans BJW (2006). Visual stimuli are common triggers of migraine and are associated with pattern glare. Headache; 46(9):1431-1440. : People with migraine reported more pattern glare and preferred coloured filters; principal component analysis grouped headache triggers into food, visual triggers, alcohol, stress and tiredness, and the environment.
- Hayne DP, Martin PR (2019). Relating Photophobia, Visual Aura, and Visual Triggers of Headache and Migraine. Headache; 59(3):430-442. : In 491 participants, headache patients with photophobia reported significantly higher interictal light sensitivity than those without photophobia and than controls (P < .001); flicker and glare followed the same pattern, visual aura did not.
- Headache Classification Committee of the International Headache Society (2018). ICHD-3, 11.3.2 Headache attributed to refractive error. Cephalalgia; 38(1):1-211. : Recognises headache caused by uncorrected or miscorrected refractive error, generally after prolonged visual tasks, while stating it is 'much less commonly a cause of headache than is generally believed.'
- Rouse MW, Borsting EJ, Mitchell GL, Scheiman M, Cotter SA, Cooper J, Kulp MT, London R, Wensveen J; CITT Group (2004). Validity and reliability of the revised convergence insufficiency symptom survey in adults. Ophthalmic and Physiological Optics; 24(5):384-390. : In adults aged 19-30, mean symptom score was 37.3 with symptomatic convergence insufficiency versus 11.0 in normals; a cut-off of 21 gave 97.8% sensitivity and 87% specificity.
- Sheppard AL, Wolffsohn JS (2018). Digital eye strain: prevalence, measurement and amelioration. BMJ Open Ophthalmology; 3(1):e000146. : Review estimating digital eye strain may affect 50% or more of computer users, split into accommodative/binocular symptoms and dry-eye symptoms.
- Convergence Insufficiency Treatment Trial Study Group (2008). Randomized clinical trial of treatments for symptomatic convergence insufficiency in children. Archives of Ophthalmology; 126(10):1336-1349. : In 221 children aged 9-17, office-based vergence/accommodative therapy gave a successful or improved outcome in 73% after 12 weeks versus 35% with office placebo therapy.
- CITT-ART Investigator Group (2019). Treatment of Symptomatic Convergence Insufficiency in Children Enrolled in the Convergence Insufficiency Treatment Trial-Attention & Reading Trial: A Randomized Clinical Trial. Optometry and Vision Science; 96(11):825-835. : In 311 children, clinical signs improved far more with therapy than placebo, but symptom scores improved similarly in both groups (11.8 vs 10.4 points, p = .21).
- Scheiman M, Kulp MT, Cotter SA, Lawrenson JG, Wang L, Li T (2020). Interventions for convergence insufficiency: a network meta-analysis. Cochrane Database of Systematic Reviews; 12:CD006768. : Across 12 trials and 1,289 participants, office-based vergence/accommodative therapy beat placebo in children (RR 3.04); in adults the evidence for non-surgical treatment is less clear.
- Teitelbaum B, Pang Y, Krall J (2009). Effectiveness of base in prism for presbyopes with convergence insufficiency. Optometry and Vision Science; 86(2):153-156. : Randomized crossover trial in 29 presbyopic adults: symptom score fell from 30.2 to 13.4 with base-in prism progressives versus 23.6 with placebo progressives.
- Scheiman M, Cotter S, Rouse M, Mitchell GL, Kulp M, Cooper J, Borsting E; CITT Study Group (2005). Randomised clinical trial of the effectiveness of base-in prism reading glasses versus placebo reading glasses for symptomatic convergence insufficiency in children. British Journal of Ophthalmology; 89(10):1318-1323. : In 72 children, base-in prism reading glasses were no better than placebo reading glasses on any outcome.
- Doble JE, Feinberg DL, Rosner MS, Rosner AJ (2010). Identification of binocular vision dysfunction (vertical heterophoria) in traumatic brain injury patients and effects of individualized prismatic spectacle lenses in the treatment of postconcussive symptoms: a retrospective analysis. PM&R; 2(4):244-253. : Retrospective series of 43 brain-injury patients: subjective symptom burden fell 71.8% after individualized prismatic lenses; uncontrolled, unblinded, single private practice.
- Rosner MS, Feinberg DL, Doble JE, Rosner AJ (2016). Treatment of vertical heterophoria ameliorates persistent post-concussive symptoms: A retrospective analysis utilizing a multi-faceted assessment battery. Brain Injury; 30(3):311-317. : In 38 post-concussion patients with vertical heterophoria, prismatic lenses were followed by 19.1-60.8% reductions on headache, dizziness and anxiety measures; retrospective, no control group.
- Feinberg DL, Rosner MS, Rosner AJ (2021). Validation of the Binocular Vision Dysfunction Questionnaire (BVDQ). Otology & Neurotology; 42(1):e66-e74. : Retrospective case series of 126 vertical heterophoria patients; the questionnaire was developed and validated by the practice that markets the treatment, with no independent validation.
- Master CL, Bacal D, Grady MF, et al.; AAP Section on Ophthalmology, American Academy of Ophthalmology, AAPOS, AACO (2022). Vision and Concussion: Symptoms, Signs, Evaluation, and Treatment. Pediatrics; 150(2):e2021056047. : Most children recover from concussion within about 4 weeks; those who do not warrant a vision-specific history and examination including convergence and accommodation.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.