Ocular Motor Dysfunction: Eye Movements Explained
Every time you read a sentence, catch a ball or scan a parking lot, you are running three separate eye-movement systems. Most people never think about them — until one quietly stops doing its job.
Ocular motor dysfunction is the term for eye movements that are inaccurate, slow or effortful. The eyes are healthy, the chart can read 20/20, and the aiming system underneath is still working far harder than it should. That extra work is what a child feels as “reading is boring” and an adult feels as “I lose my place by the end of the day.”
Key takeaways
- Three eye movements do almost all the work: fixations (holding steady), saccades (jumping) and pursuits (following).
- Reading is built almost entirely from saccades and fixations, so small inefficiencies show up first as poor reading stamina.
- Tracking deficits appear more often in children with dyslexia and in people recovering from concussion — associations from selected samples, not proof of cause.
- Vision problems do not cause dyslexia. We treat eye movements that are inefficient and uncomfortable, not reading disability.
The three eye movements you use every day
Fixations: holding still on purpose
A fixation is holding your eyes steady on something that isn’t moving — a word, a face, a stop sign. It is the foundation for everything else: you cannot follow an object or jump accurately to a new one without locking onto it first.
When fixation is unstable, a person drifts off the target and comes back without realising it, so it does not feel like looking away. Because it looks like inattention, it is sometimes mistaken for ADHD. The overlap is real in the data: ADHD is reported in 15.6% of children with vision problems versus 8.3% of those without, an adjusted odds ratio of about 1.8 (DeCarlo et al., 2016). That is an association, not a cause — a vision evaluation rules a visual contribution in or out, it does not replace an ADHD assessment.
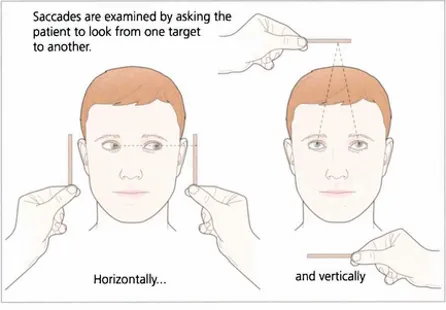
Saccades: jumping from one target to the next
Saccades are the fast jumps between targets, the workhorse of daily vision: reading, scanning a room, checking mirrors while driving, copying from a whiteboard.
Reading is essentially a long chain of them. Skilled readers pause an average of roughly 250 milliseconds per fixation while the fixated word and, to some extent, the upcoming word are processed (Degno & Liversedge, 2020), and each forward jump covers only about six to ten letter spaces (Rayner et al., 2010). These patterns track moment-to-moment thinking, which is why they shift with both the reader and the text (Rayner, 1998). Ask someone with an ocular motor dysfunction to look from one target to the next and the eyes may overshoot, undershoot, or take an extra beat to find the target at all. Multiply that by a page and reading becomes slow and tiring even when comprehension is fine.
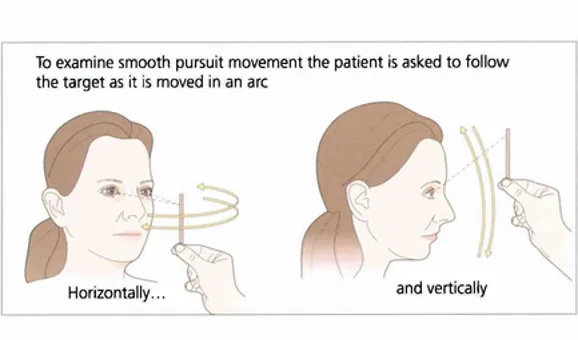
Pursuits: following something that moves
Pursuits let you follow a moving object smoothly — a ball, a car, a finger moving along a line of text. When pursuits are weak the movement looks choppy, visual attention slips off the target, and fast movements can bring on nausea.
What it looks like in reading, sport and daily life
- Reading: losing the place, skipping or re-reading lines, using a finger long past the usual age, fading fast on longer passages — the pattern we describe in why children lose their place while reading.
- Sport: trouble judging a ball in flight, late reactions, clumsy hand-eye timing. Training oculomotor skills for sport is plausible but unevenly evidenced, so we call it skill training, not a promised performance gain (Appelbaum & Erickson, 2018).
- Daily life: copying from the board, finding an item on a crowded shelf, getting through screen work without the words swimming.
How common are tracking problems?
In children who struggle with reading. Comparing 29 children with developmental dyslexia and 33 typical readers, tracking deficits were found in 62% versus 15% and any visual deficit in 79% versus 33% — though the authors were explicit that the cause and clinical relevance remain uncertain (Raghuram et al., 2018). Balance that against a cohort of 5822 children, where four of every five severely impaired readers had normal ophthalmic function and no association was found with convergence or accommodation (Creavin et al., 2015). Both are true: tracking problems turn up more often in clinics that see struggling readers, and most struggling readers do not have them.
After a concussion or brain injury. Among 100 adolescents in a concussion program, 69% had a vision diagnosis and 29% had saccadic dysfunction (Master et al., 2016). At 4 to 12 weeks post-injury, 70% of 113 adolescents had at least one oculomotor diagnosis, and physician screening missed many (Scheiman et al., 2021). In a specialty brain-injury clinic, 90% of traumatic brain injury patients had an oculomotor dysfunction (Ciuffreda et al., 2007). Two caveats: these are referral samples, so the percentages run higher than across everyone who takes a knock to the head, and most people recover on their own — of children with an abnormal near point of convergence after concussion, 46% recovered with standard care, a further 41% recovered after vestibular therapy, and only 13% went on to office-based vision therapy (Storey et al., 2017). AAP and AAO guidance is to arrange a vision-specific examination, pursuits and saccades included, when symptoms have not settled by about four weeks (Master et al., 2022).
Where the professions disagree, and where we stand
Pediatric and ophthalmology bodies hold that dyslexia is language-based, that vision problems can interfere with learning but do not cause it, and that tracking exercises are not supported treatments for learning disabilities (AAP/AAO/AAPOS/AACO, 2009; Handler & Fierson, 2011). Optometric bodies hold that vision problems can and often do interfere with learning, and that optometric care belongs inside a multidisciplinary plan (AAO/AOA, 1997). The largest trial to test the reading question found vergence and accommodative therapy no better than placebo for reading comprehension (CITT-ART, 2019).
Our own position is deliberately narrow. We do not treat dyslexia and we do not promise better grades. We find and treat eye movements that are inefficient or uncomfortable, and leave reading instruction to the reading specialists and teachers.
How we assess eye movements
- Direct observation. We watch fixations, saccades and pursuits against standardized targets, grading accuracy, head movement and attention.
- The Developmental Eye Movement (DEM) test. A timed number-naming test comparing vertical with horizontal performance. Its limits are published: in 158 children the DEM did not correlate with objectively recorded saccades, though it did correlate with reading ability and processing speed (Ayton et al., 2009). We use it as a screening measure, not a read-out of eye movements.
- Objective recording while reading. Recording gives fixation counts, fixation duration, regressions and reading rate on real text; recorded fixation duration and reading rate related to standardized reading scores where DEM outcomes did not (Webber et al., 2011). That is what our ReadAlyzer assessment measures.
Eye movements are never assessed alone. They sit inside a full binocular vision workup, because eye teaming and focusing problems cause many of the same complaints — see our guide to convergence insufficiency and our page on ocular motor dysfunction.
How we treat it
Office-based vision therapy for eye movements works like any motor training: graded tasks that build accuracy first, then speed, then the ability to hold both while something else competes for attention. Fixation work comes before saccade work; saccades and pursuits are then loaded with balance, sound, memory or reading demands so the skill survives a real classroom.
We are candid about the evidence. The strongest randomized support in this field is for office-based vergence and accommodative therapy in symptomatic convergence insufficiency (Cochrane review, 2020). Therapy aimed specifically at eye movements rests on smaller, uncontrolled work, such as post-concussion case series in which most patients who finished therapy improved (Gallaway et al., 2017). So we measure what we treat, re-test on a schedule, and say plainly if the numbers are not moving.
If reading is exhausting, if the page will not stay still, or if your child’s reading symptoms sound like the ones above, the next step is a comprehensive developmental vision evaluation that includes eye movements. Schedule an evaluation or see what our examinations include.
Originally written by Kelsey Smith, Vision Therapist, Vision & Learning Center.
Common Questions About This Topic
What is ocular motor dysfunction?
It is a term for eye movements that are inaccurate, slow or effortful — poor fixation, saccades that overshoot or undershoot, or jerky pursuits — in eyes that are otherwise healthy and may see 20/20. It is diagnosed on an eye-movement examination, not on an eye chart.
Does poor eye tracking cause dyslexia?
No. Pediatric and ophthalmology bodies state clearly that dyslexia is language-based and that vision problems do not cause it, and the largest randomized trial of office-based vergence and accommodative therapy in children with convergence insufficiency found no reading benefit over placebo. Some children with reading difficulty do also have tracking or focusing problems that make near work uncomfortable, and those are worth finding and treating on their own merits.
How do you test eye movements?
We watch fixations, saccades and pursuits directly, use a standardized visual-verbal test such as the Developmental Eye Movement (DEM) test, and where it helps we record eye movements objectively while a child reads. Each method answers a different question, so we interpret them together with the rest of the binocular vision examination.
Can eye movements improve after a concussion?
Many people recover on their own. In one large pediatric series of children with an abnormal near point of convergence after concussion, about half (46%) recovered with standard care, most of the rest recovered after vestibular therapy, and only 13% needed office-based vision therapy. National guidance is to arrange a vision-specific examination when symptoms have not settled by about four weeks.
Is vision therapy for eye movements evidence-based?
The strongest evidence is for office-based vergence and accommodative therapy in symptomatic convergence insufficiency. Eye-movement-specific therapy has far less trial evidence, so we describe it as our clinical approach, measure the signs we are treating, and are honest about what has and has not been proven.
Where This Information Comes From
- Degno F, Liversedge SP (2020). Eye Movements and Fixation-Related Potentials in Reading: A Review. Vision (Basel); 4(1):11. : Fixations during reading last on average about 250 ms, during which the fixated word and, to some extent, the upcoming word are processed.
- Rayner K, Slattery TJ, Belanger NN (2010). Eye movements, the perceptual span, and reading speed. Psychonomic Bulletin & Review; 17(6):834-839. : Mean forward saccade lengths in reading ranged from roughly 6 to 10 letter spaces across conditions.
- Rayner K (1998). Eye movements in reading and information processing: 20 years of research. Psychological Bulletin; 124(3):372-422. : Landmark review concluding eye-movement data reflect moment-to-moment cognitive processing during reading.
- Raghuram A, Gowrisankaran S, Swanson E, Zurakowski D, Hunter DG, Waber DP (2018). Frequency of Visual Deficits in Children With Developmental Dyslexia. JAMA Ophthalmology; 136(10):1089-1095. : Tracking deficits in 62% of children with dyslexia versus 15% of typical readers; the authors call the cause and clinical relevance uncertain.
- Creavin AL, Lingam R, Steer C, Williams C (2015). Ophthalmic abnormalities and reading impairment. Pediatrics; 135(6):1057-1065. : In 5822 children, four of five with severe reading impairment had normal ophthalmic function and no association was found with convergence or accommodation.
- Handler SM, Fierson WM; AAP Section on Ophthalmology, Council on Children with Disabilities, AAO, AAPOS, AACO (2011). Learning disabilities, dyslexia, and vision. Pediatrics; 127(3):e818-e856. : Technical report stating dyslexia is phonologic in origin and that tracking exercises and vision training are not supported as treatments for learning disabilities.
- American Academy of Pediatrics, AAO, AAPOS, AACO (2009). Joint statement - Learning disabilities, dyslexia, and vision. Pediatrics; 124(2):837-844. : Joint statement: vision problems can interfere with learning but do not cause dyslexia, and vision therapy is not supported for learning disabilities.
- American Academy of Optometry; American Optometric Association (1997). Vision, learning and dyslexia: a joint organizational policy statement. Journal of the American Optometric Association; 68(5):284-286. : Optometric position that vision problems can and often do interfere with learning and that optometric care is one part of multidisciplinary management.
- CITT-ART Investigator Group (2019). Effect of Vergence/Accommodative Therapy on Reading in Children with Convergence Insufficiency: A Randomized Clinical Trial. Optometry and Vision Science; 96(11):836-849. : In 310 children, reading comprehension improved 3.7 points with therapy versus 3.8 with placebo - no reading benefit.
- Master CL, Scheiman M, Gallaway M, Goodman A, Robinson RL, Master SR, Grady MF (2016). Vision Diagnoses Are Common After Concussion in Adolescents. Clinical Pediatrics; 55(3):260-267. : Of 100 adolescents in a concussion program, 69% had a vision diagnosis, including saccadic dysfunction in 29%.
- Scheiman M, Grady MF, Jenewein E, Shoge R, Podolak OE, Howell DH, Master CL (2021). Frequency of oculomotor disorders in adolescents 11 to 17 years of age with concussion, 4 to 12 weeks post injury. Vision Research; 183:73-80. : 70% of 113 adolescents had at least one oculomotor diagnosis 4-12 weeks after concussion, and physician screening missed many.
- Ciuffreda KJ, Kapoor N, Rutner D, Suchoff IB, Han ME, Craig S (2007). Occurrence of oculomotor dysfunctions in acquired brain injury: a retrospective analysis. Optometry; 78(4):155-161. : 90% of traumatic brain injury outpatients at a vision-rehabilitation clinic had an oculomotor dysfunction (referral sample).
- Master CL, Bacal D, Grady MF, et al.; AAP Section on Ophthalmology, AAO, AAPOS, AACO (2022). Vision and Concussion: Symptoms, Signs, Evaluation, and Treatment. Pediatrics; 150(2):e2021056047. : Clinical report: most children recover by 4 weeks; those who do not warrant examination of pursuits, saccades, convergence and accommodation.
- Storey EP, Master SR, Lockyer JE, Podolak OE, Grady MF, Master CL (2017). Near Point of Convergence after Concussion in Children. Optometry and Vision Science; 94(1):96-100. : Of 67 children with abnormal near point of convergence after concussion, 46% recovered with standard care, 41% after vestibular therapy and 13% after office-based vision therapy.
- Ayton LN, Abel LA, Fricke TR, McBrien NA (2009). Developmental eye movement test: what is it really measuring? Optometry and Vision Science; 86(6):722-730. : In 158 children, DEM scores did not correlate with objectively recorded saccades but did correlate with reading ability and visual processing speed.
- Webber A, Wood J, Gole G, Brown B (2011). DEM test, Visagraph eye movement recordings, and reading ability in children. Optometry and Vision Science; 88(2):295-302. : Recorded fixation duration and reading rate related to standardized reading scores; DEM outcomes did not.
- Appelbaum LG, Erickson G (2018). Sports vision training: A review of the state-of-the-art in digital training techniques. International Review of Sport and Exercise Psychology; 11(1):160-189. : Reviews the rationale for training visual and oculomotor skills in sport and notes the supporting research is uneven.
- DeCarlo DK, Swanson M, McGwin G, Visscher K, Owsley C (2016). ADHD and Vision Problems in the National Survey of Children's Health. Optometry and Vision Science; 93(5):459-465. : ADHD was reported in 15.6% of children with vision problems versus 8.3% without (adjusted OR 1.8) - an association only.
- Scheiman M, Kulp MT, Cotter SA, Lawrenson JG, Wang L, Li T (2020). Interventions for convergence insufficiency: a network meta-analysis. Cochrane Database of Systematic Reviews; 12:CD006768. : Office-based vergence/accommodative therapy with home reinforcement beat placebo in children with convergence insufficiency (RR 3.04).
- Gallaway M, Scheiman M, Mitchell GL (2017). Vision Therapy for Post-Concussion Vision Disorders. Optometry and Vision Science; 94(1):68-73. : Private-practice series of 218 post-concussion records: 82% had an oculomotor diagnosis and most completers improved; uncontrolled.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.