Amblyopia Therapy: A Vision Therapist's Perspective
Amblyopia, often called “lazy eye,” is reduced vision in one eye (occasionally both) that glasses alone do not fully correct. The eye usually looks healthy and the child rarely complains, so most families first hear the word at a screening or an eye exam.
Below is how the vision therapists at Vision & Learning Center structure an amblyopia program, and where that program sits relative to standard medical care. The staged approach is our clinical perspective; standard care is glasses first, then patching or atropine drops, and that is where the strongest research sits.
Key takeaways
- Amblyopia is a developmental problem in the visual brain, not a weak eye muscle: the brain favors one eye and suppresses (ignores) the other (AAO Amblyopia PPP, 2023).
- Treatment starts with an accurate prescription. Glasses alone improved vision by two or more lines in 77% of young children with anisometropic amblyopia (Cotter et al., 2006).
- Patching and atropine work about equally well, and two hours of daily patching matched six for moderate amblyopia (PEDIG, 2002; Repka et al., 2003).
- Binocular video games are promising but have not beaten patching head to head (Pineles et al., 2020).
- The American Academy of Ophthalmology finds “no convincing evidence” that antisuppression, vergence, accommodation or eye-hand exercises treat amblyopia. We offer those activities alongside standard care, never instead of it.
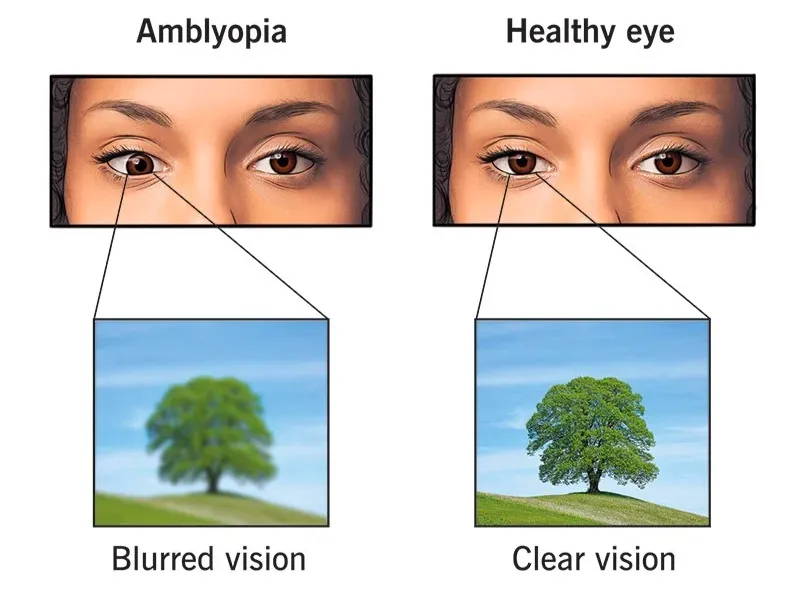 How the same scene can look through an amblyopic eye and a healthy eye
What amblyopia is, and what it is not
The AAO Preferred Practice Pattern describes amblyopia as a reduction of best-corrected visual acuity “that usually occurs in the setting of an otherwise normal eye,” and calls it “a developmental disorder of the central nervous system that results from the abnormal processing of visual images” (AAO Amblyopia PPP, 2023).
That is why “lazy eye” is a misleading name: neither the eye nor its muscles are weak. When the two eyes send mismatched pictures early in life, the brain leans on the clearer or straighter eye and suppresses the other, and the suppressed eye’s sharpness never fully develops. Depth perception takes the same hit: impaired stereoscopic depth perception is the most common deficit in amblyopia under ordinary two-eyed viewing (Levi et al., 2015). Suppression is what we work on most, because a patient who cannot notice when an eye has switched off cannot learn to keep it on.
Amblyopia affects roughly 1.4% of people worldwide and about 2.4% in North America (Fu et al., 2020). In a large Los Angeles population study of African American and Hispanic/Latino preschoolers, amblyopia was found in 1.5% to 2.6% of children, and 78% of those cases were attributable to refractive error (MEPEDS, 2008). Two types come through our doors most often:
- Refractive (anisometropic) amblyopia. A large difference in prescription between the eyes means the blurrier eye never delivers a sharp image to the fovea, so the brain favors the clearer eye and suppression follows.
- Strabismic amblyopia. One eye turns in, out, up or down, so the brain never gets two matching images to fuse and learns to ignore the deviated eye. Because several deficits stack up at once, comfortable two-eyed vision takes longer to build. Our lazy eye page covers both in more depth.
Standard care comes first: glasses, then patching or atropine
The AAO guideline states that treating refractive error alone is the initial step in care at every age from 0 through 17 (AAO Amblyopia PPP, 2023). PEDIG showed why: in 84 children aged 3 to under 7 with untreated anisometropic amblyopia, glasses alone improved acuity by two or more lines in 77% and resolved the amblyopia in 27%, with improvement continuing for up to 30 weeks (Cotter et al., 2006).
When glasses are not enough, the stronger eye is penalized so the brain has to use the weaker one. PEDIG’s trials set the doses:
- Patching and atropine drops are about equally effective. In 419 children under 7 with moderate amblyopia, patching improved acuity 3.16 lines and atropine 2.84 lines at six months (PEDIG, 2002).
- Two hours a day equals six for moderate amblyopia. Both schedules produced the same 2.40-line gain at four months when paired with an hour of near activities (Repka et al., 2003).
- Six hours equals full-time patching for severe amblyopia. Children seeing 20/100 to 20/400 gained 4.8 versus 4.7 lines (Holmes et al., 2003).
Several PEDIG patching regimens paired patching with an hour of near activities, but PEDIG went on to test that ingredient head to head and it made no difference: in 425 children, patching with near activities gave 2.5 lines of improvement versus 2.6 lines with distance activities, an adjusted difference of 0.0 lines (PEDIG, 2008). So we do not claim our activities make patching work better on the eye chart; our reasons for using them are different, and we set them out below. For more, read The Role of Eye Patches in Vision Therapy and our guide to Amblyopia Treatment Options: What the PEDIG Trials Show.
Does age close the door?
Age matters, but less than families are often told. Pooling four PEDIG trials, children aged 7 to under 13 responded less than 3- to 7-year-olds, though some older children still improved markedly (Holmes et al., 2011). In 507 patients aged 7 to 17, 53% of the 7-to-12 group responded to a regimen of patching, near activities and atropine drops, versus 25% on glasses alone. Among the 103 teenagers aged 13 to 17, who were prescribed patching and near activities without atropine, response rates overall were no better than glasses alone (25% versus 23%, P = .22); only among teenagers never treated before did 47% respond versus 20% (Scheiman et al., 2005). Residual deficits are common: at age 15, about 60% of children treated before age 7 saw 20/25 or better in the amblyopic eye, while 48% still had a two-line gap between the eyes (Repka et al., 2014). The AAO’s position is that “treatment may be offered to children regardless of age, including older children and teenagers, especially if they have not been treated previously” (AAO Amblyopia PPP, 2023).
Younger patients usually move through a program faster, and adults need more time and patience after compensating for one weak eye for decades. That is our observation, not a trial result.
Binocular and dichoptic games: promising, not a replacement
Dichoptic games show a strong image to the amblyopic eye and a weakened one to the fellow eye, so a player has to use both eyes to succeed. Results are mixed:
- In 385 children aged 5 to 12, a binocular iPad game improved acuity 1.05 lines versus 1.35 lines with two hours of daily patching, and only 22% finished more than three-quarters of the prescribed play (Holmes et al., 2016).
- In older children, teens and adults, an active binocular game did no better than a placebo game (Gao et al., 2018).
- A dichoptic streaming-video treatment gained 1.8 lines versus 0.8 with glasses alone in children aged 4 to 7, but was never compared with patching (Xiao et al., 2022).
Reviewing 20 studies, the AAO found no level I evidence that binocular treatment can substitute for patching or optical correction (Pineles et al., 2020), and its 2023 guideline concludes that “the evidence remains limited to recommend binocular therapy for treatment of amblyopia” (AAO Amblyopia PPP, 2023). Our reading is the same: worth watching, not a replacement.
Where vision therapy fits, and what the evidence says
Here we have to be candid. The AAO amblyopia guideline groups the tools we use, “antisuppression and vergence activities, accommodation, and eye-hand coordination exercises and perceptual learning,” and concludes: “There is no convincing evidence for treatment success with these activities for amblyopia” (AAO Amblyopia PPP, 2023).
We take that seriously. Controlled trials have not shown these activities improve acuity beyond what glasses and patching achieve, so we never offer them in place of the prescription, patching or drops your eye doctor recommends, and we do not promise an acuity outcome. Our aims are different: helping a patient notice suppression, sense where each eye is pointing, and build the eye control, focusing and localization that make two-eyed vision usable day to day. Whether that produces measurable long-term gains is a question the research has not answered. This is our clinical perspective, offered alongside standard care.
How our therapists structure amblyopia therapy
Whatever the type of amblyopia, we work through three stages, training eye control, accommodation (focusing) and localization (judging where things sit in space) throughout.
Stage 1: Monocular
We start one eye at a time so the patient becomes aware of each eye separately and evens out how well each one localizes an object. Pointing at or touching targets with the amblyopic eye alone gives instant feedback about how well that eye judges position.
Stage 2: Biocular
Next, both eyes stay open but each sees a different target, so the patient learns to feel when the amblyopic eye is on or off.
Superimposition is a favorite. The patient holds a mirror against the nose at a 45-degree angle, so one eye looks into the mirror while the other looks straight ahead. We work in a corner of the room with a picture on each wall, such as a butterfly and a circle. The patient attends first to the butterfly and sees mainly that image, then switches to the circle. Once each eye’s picture can be called up on demand, the goal is to see both together, and changing the targets builds the awareness the task needs.
Stage 3: Binocular
Once both eyes are used consistently, we move to binocular activities, still watching for suppression. Red and green glasses make suppression visible: with Binocular Accommodative Rock (BAR), a red/green Hart chart of letters that each eye sees differently, or anti-suppression cards, part of the picture disappears the moment an eye switches off. Free-space fusion cards let the patient check the same thing without filters.
Tranaglyphs and vectograms are especially useful. To see the three-dimensional picture, the eyes have to team at one particular spot in space; if the patient suppresses, nothing pops out or sinks in and the image looks flat. Sliding the cards apart or together makes the eyes converge or diverge, whichever the patient needs, and dials the task up or down.
Tailoring the program
Strabismic amblyopia calls for more proprioceptive work, so the patient can feel where the turned eye is aimed. Refractive amblyopia calls for more accommodation-based activities, so the patient learns to notice and adjust focus.
Treatment runs for months and depends on active participation, so we send home activities to reinforce each session. Activities with built-in visual feedback matter most, and the patient’s own feedback tells us when to make a program harder, easier, or to change approach entirely.
When to have your child evaluated
Because amblyopia rarely causes complaints, an examination is how it gets found. If you have noticed an eye turn, a strong preference for one eye, clumsy depth judgment, or a big difference between the two prescriptions, read about our amblyopia and strabismus care and book a comprehensive developmental vision evaluation. Schedule an evaluation at any of our four South Florida offices.
Common Questions About This Topic
Is amblyopia a problem with the eye muscles?
No. The American Academy of Ophthalmology describes amblyopia as a developmental disorder of the central nervous system, in an eye that is otherwise normal. Some patients also have an eye turn (strabismus), which can cause amblyopia, but the reduced sharpness itself comes from how the brain processes that eye's picture, not from a weak muscle.
Does vision therapy replace glasses or patching for amblyopia?
No. Standard care is glasses first, then patching or atropine drops, and those carry the strongest evidence. The AAO states there is no convincing evidence that antisuppression, vergence, accommodation or eye-hand activities treat amblyopia. We use in-office activities as an adjunct to what your eye doctor prescribes, never as a substitute.
Is it too late to treat amblyopia after age 7?
Not necessarily. Children aged 7 to 12 respond less on average than younger children, but in a PEDIG trial 53% of 7- to 12-year-olds improved on a regimen of patching, near activities and atropine drops, compared with 25% on glasses alone. Teenagers in that trial were prescribed patching without atropine, and overall they did no better than glasses alone (25% versus 23%); only among those never treated before did 47% respond, versus 20%. Gains are usually smaller and slower, and some residual difference between the eyes is common.
Do binocular iPad or VR games cure lazy eye?
Results are mixed. A large trial found a binocular iPad game less effective than two hours of daily patching, and another found an active game no better than a placebo game. A newer dichoptic video treatment beat glasses alone in young children but was never compared with patching. The AAO considers the evidence too limited to recommend binocular therapy as standard treatment.
How long does amblyopia treatment take?
Months, not weeks. Vision kept improving on glasses alone for up to 30 weeks in one PEDIG study, and the patching trials measured results at four to six months. Programs vary with the type of amblyopia, the patient's age and how consistently home activities get done, so we adjust as we go rather than promise a timeline.
Where This Information Comes From
- Cruz OA, Repka MX, Hercinovic A, et al.; American Academy of Ophthalmology Preferred Practice Pattern Pediatric Ophthalmology/Strabismus Panel (2023). Amblyopia Preferred Practice Pattern. Ophthalmology, 130(3):P136-P178. : Defines amblyopia as a developmental disorder of the central nervous system; refractive correction is the initial step at every age; states there is no convincing evidence for antisuppression, vergence, accommodation or eye-hand exercises for amblyopia; evidence for binocular therapy remains limited; treatment may be offered regardless of age.
- Cotter SA, Edwards AR, Wallace DK, et al.; Pediatric Eye Disease Investigator Group (2006). Treatment of anisometropic amblyopia in children with refractive correction. Ophthalmology, 113(6):895-903. : In 84 children aged 3 to under 7, glasses alone improved acuity by 2 or more lines in 77% and resolved the amblyopia in 27%; improvement took up to 30 weeks to stabilize.
- Pediatric Eye Disease Investigator Group (2002). A randomized trial of atropine vs. patching for treatment of moderate amblyopia in children. Archives of Ophthalmology, 120(3):268-278. : 419 children under 7 with moderate amblyopia: patching improved acuity 3.16 lines and atropine 2.84 lines at 6 months; both judged appropriate first-line treatments.
- Repka MX, Beck RW, Holmes JM, et al.; Pediatric Eye Disease Investigator Group (2003). A randomized trial of patching regimens for treatment of moderate amblyopia in children. Archives of Ophthalmology, 121(5):603-611. : 189 children under 7: 2 hours and 6 hours of daily patching, each paired with 1 hour of near activities, produced the same 2.40-line improvement at 4 months.
- Holmes JM, Kraker RT, Beck RW, et al.; Pediatric Eye Disease Investigator Group (2003). A randomized trial of prescribed patching regimens for treatment of severe amblyopia in children. Ophthalmology, 110(11):2075-2087. : 175 children under 7 with severe amblyopia (20/100 to 20/400): 6 hours of daily patching improved acuity 4.8 lines versus 4.7 lines with full-time patching at 4 months.
- Scheiman MM, Hertle RW, Beck RW, et al.; Pediatric Eye Disease Investigator Group (2005). Randomized trial of treatment of amblyopia in children aged 7 to 17 years. Archives of Ophthalmology, 123(4):437-447. : 53% of 7- to 12-year-olds responded versus 25% with glasses alone; in 13- to 17-year-olds there was no overall benefit (25% vs 23%, P = .22), but 47% vs 20% among the never-treated; most were left with a residual deficit.
- Pediatric Eye Disease Investigator Group (2008). A randomized trial of near versus distance activities while patching for amblyopia in children aged 3 to less than 7 years. Ophthalmology, 115(11):2071-2078. : In 425 children aged 3 to under 7, near activities during patching gave 2.5 lines of improvement versus 2.6 lines for distance activities (adjusted difference 0.0 lines): no added acuity benefit.
- Holmes JM, Lazar EL, Melia BM, et al.; Pediatric Eye Disease Investigator Group (2011). Effect of age on response to amblyopia treatment in children. Archives of Ophthalmology, 129(11):1451-1457. : Meta-analysis of 4 PEDIG trials: children aged 7 to under 13 were less responsive than children aged 3 to 7, though some older children still showed a marked response.
- Repka MX, Kraker RT, Holmes JM, et al.; Pediatric Eye Disease Investigator Group (2014). Atropine vs patching for treatment of moderate amblyopia: follow-up at 15 years of age of a randomized clinical trial. JAMA Ophthalmology, 132(7):799-805. : At age 15, 59.9% of children treated before age 7 saw 20/25 or better in the amblyopic eye, while 48.3% still had a 2-line or greater difference between the eyes; results did not differ by original treatment.
- Holmes JM, Manh VM, Lazar EL, et al.; Pediatric Eye Disease Investigator Group (2016). Effect of a Binocular iPad Game vs Part-time Patching in Children Aged 5 to 12 Years With Amblyopia: A Randomized Clinical Trial. JAMA Ophthalmology, 134(12):1391-1400. : 385 children: the binocular iPad game improved acuity 1.05 lines versus 1.35 lines with 2 hours of daily patching; only 22.2% completed more than 75% of prescribed play.
- Gao TY, Guo CX, Babu RJ, et al.; BRAVO Study Team (2018). Effectiveness of a Binocular Video Game vs Placebo Video Game for Improving Visual Functions in Older Children, Teenagers, and Adults With Amblyopia: A Randomized Clinical Trial. JAMA Ophthalmology, 136(2):172-181. : In 115 participants aged 7 and older, the active binocular game was no better than a placebo game over 6 weeks.
- Pineles SL, Aakalu VK, Hutchinson AK, et al. (2020). Binocular Treatment of Amblyopia: A Report by the American Academy of Ophthalmology. Ophthalmology, 127(2):261-272. : Review of 20 studies found no level I evidence that binocular treatment can substitute for patching or optical treatment; two large randomized trials showed it inferior to patching.
- Xiao S, Angjeli E, Wu HC, et al.; Luminopia Pivotal Trial Group (2022). Randomized Controlled Trial of a Dichoptic Digital Therapeutic for Amblyopia. Ophthalmology, 129(1):77-85. : In 105 children aged 4 to 7, a dichoptic digital treatment plus glasses improved acuity 1.8 lines versus 0.8 lines with glasses alone at 12 weeks; the comparator was glasses, not patching.
- Levi DM, Knill DC, Bavelier D (2015). Stereopsis and amblyopia: A mini-review. Vision Research, 114:17-30. : Identifies impaired stereoscopic depth perception as the most common deficit in amblyopia under ordinary binocular viewing.
- Fu Z, Hong H, Su Z, Lou B, Pan CW, Liu H (2020). Global prevalence of amblyopia and disease burden projections through 2040: a systematic review and meta-analysis. British Journal of Ophthalmology, 104(8):1164-1170. : Pooled global amblyopia prevalence 1.44%, and 2.41% in North America, across 60 studies.
- Multi-ethnic Pediatric Eye Disease Study Group (2008). Prevalence of amblyopia and strabismus in African American and Hispanic children ages 6 to 72 months: the Multi-ethnic Pediatric Eye Disease Study. Ophthalmology, 115(7):1229-1236. : Population-based Los Angeles study of 6014 African American and Hispanic/Latino children aged 6 to 72 months: amblyopia in 1.5% to 2.6%, with 78% of cases attributable to refractive error.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.