Depth Perception: How It Develops and What Affects It
Depth perception is how you know the glass is within reach, how far the curb is, and whether the ball is arriving now or in half a second. It feels automatic — which is exactly why a problem with it goes unnoticed for years. A child has nothing to compare it to, and an adult losing it slowly blames clumsiness or tiredness instead.
Key takeaways
- Depth perception comes from two eyes aiming at the same target and the brain comparing the small difference between the two images. That fine, two-eyed depth sense is called stereopsis.
- It is not present at birth. The eyes become capable of forming a three-dimensional view at around five months (AOA; AAO), and precision keeps improving into the school years.
- Amblyopia, strabismus and less obvious eye-teaming problems all reduce it — and the most common deficit in amblyopia is reduced stereo depth, not just reduced letter acuity (Levi et al., 2015).
- Treatment depends on the cause. Depth perception can sometimes be recovered, including in adults, but no honest clinician promises a specific result.
What depth perception actually is
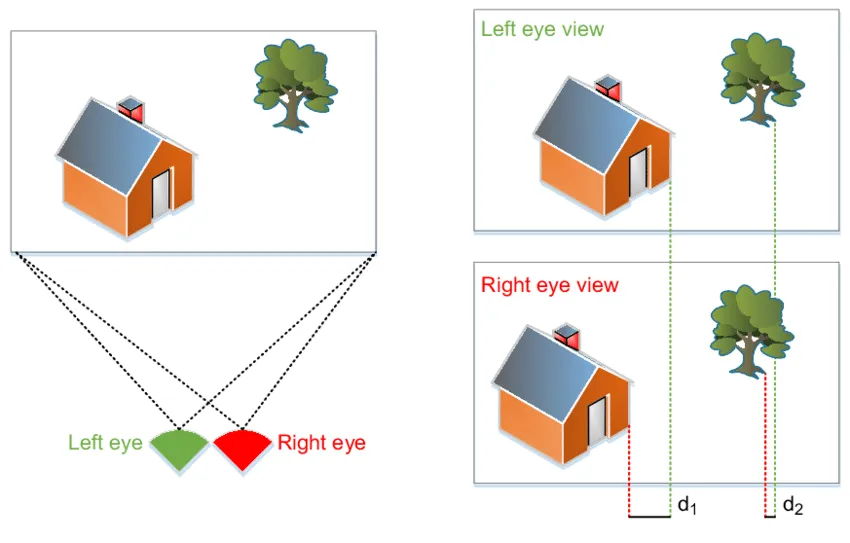
Your eyes sit about two and a half inches apart, so each sees the world from a slightly different angle. The brain measures that difference — binocular disparity — and turns it into a sense of solid, three-dimensional space. Stereopsis is the top level of that skill, above simultaneous perception and fusion in the three grades of binocular vision.
The brain also has one-eyed backup cues: relative size, overlap, shadow, perspective, and the way near things sweep past faster than far things when you move your head. That is why someone with no stereopsis still gets around. But the backup cues are coarser, and the gap shows up most within arm’s reach. In 143 people aged 10 to 30, performance on pegboard and bead-threading tasks tracked stereoacuity, and those with normal stereoacuity performed best on every test (O’Connor et al., 2010).
Seeing in 3D: what stereoscopic movies borrow from your eyes
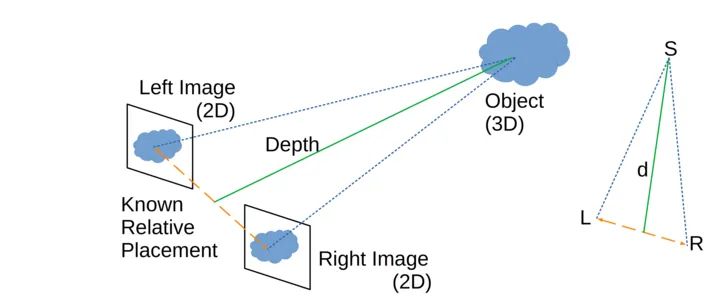
3D films, 3D games and virtual-reality headsets borrow the same trick your visual system uses — deliver a slightly different image to each eye and let the brain build the depth. Polarized or shuttered glasses simply keep the two images separate on one screen.
That does not make a 3D movie a vision test. When researchers degraded binocular vision in stages in 57 people aged 16 to 62, depth identification on a handheld 3D console stayed at 100% until one eye was genuinely suppressed, and the compelling 3D effect held up just as long — because motion on screen supplies depth information a static clinical test does not (Tidbury et al., 2015). The useful signal runs the other way: if 3D films look flat, or leave you with headaches, eye strain or nausea, mention it at your next eye exam.
How depth perception develops
Depth perception is built, not issued. In the first two months a baby’s eyes often do not work together well and may appear to cross or wander; by three months they should focus and track together; and depth perception has developed more fully at around five months (American Academy of Ophthalmology). The American Optometric Association puts it the same way — depth perception is not present at birth, the eyes become capable of forming a three-dimensional view at about the fifth month, and eye-hand coordination and depth perception should be well developed by age two (AOA).
Precision then keeps sharpening for years. On the Randot Preschool test, average stereoacuity in normally sighted children improves from about 100 arcseconds at age three to 60 by age five and 40 by age seven (Birch et al., 2008).

Two cautions come from the same literature. Very young children often cannot do a stereo test at all — testability is about 65% at age two, 92% at three and near 100% after that — and while the test rarely flags normal children incorrectly, its sensitivity for picking up visual problems is under 50% (Read et al., 2019). One stereo card is not a screening program. The AOA recommends comprehensive eye examinations at 6 to 12 months, once between ages three and five, and before first grade and annually after (AOA, 2017).
Conditions that reduce depth perception
Amblyopia (lazy eye)
In amblyopia, one eye does not develop normal vision and the brain leans on the other. Pooled global prevalence is about 1.4%, and about 2.4% in North America (Fu et al., 2020); US preschool studies found 1.5% to 2.6%, with 78% of cases attributable to refractive error (MEPEDS, 2008). Under ordinary two-eyed viewing, the most common deficit in amblyopia is impaired stereoscopic depth perception, and it can affect motor coordination, sport and mobility (Levi et al., 2015). More on our lazy eye page.
Strabismus (eye turns)
When the eyes do not point at the same place, the brain gets two conflicting images and often suppresses one — removing the raw material stereopsis needs. Pooled global prevalence of any strabismus is about 1.9% (Hashemi et al., 2019); US preschool studies report 2.1% to 3.3% (MEPEDS, 2008; Baltimore Pediatric Eye Disease Study, 2009).
Phorias: esophoria and exophoria
Phorias are subtle misalignments the brain holds in check most of the time, showing up under fatigue or sustained near work rather than constantly. In our clinical experience, patients with esophoria (an inward drift) often describe near objects seeming to jump closer than expected, while patients with exophoria (an outward drift) misjudge the other way — reaching short, or feeling unsure in busy spaces. Both patterns commonly come with eye strain and headaches at the end of a reading or screen session.
The best-studied version of this is convergence insufficiency, where the eyes will not hold their inward aim at reading distance. Among the 453 fifth- and sixth-graders with complete data in a US school-based study, about 13% met a definite or high-suspect definition (Rouse et al., 1999).
What treatment can and cannot do
Amblyopia. Glasses come first. In 84 children aged 3 to under 7 with untreated anisometropic amblyopia, optical correction alone improved acuity by two or more lines in 77% and resolved the amblyopia in 27% (Cotter et al., 2006). If vision is still behind after glasses, patching and atropine drops are both reasonable next steps — in 419 children under seven with moderate amblyopia the two produced improvement of similar magnitude, and the trial called both appropriate initial treatments (PEDIG, 2002). Older children still respond: among 7- to 12-year-olds, 53% responded to patching, near activities and atropine, versus 25% with glasses alone (PEDIG, 2005) — where “responded” meant a gain of at least 10 letters rather than a cure, and most were left with a residual deficit. Younger children respond better on average (Holmes et al., 2011). Binocular “dichoptic” games are promising but not a replacement: reviewing 20 studies, the American Academy of Ophthalmology found no level I evidence that they can substitute for patching or optical treatment (Pineles et al., 2020), and the later trial that did show benefit compared the game with glasses alone, not with patching (Xiao et al., 2022). Recovering letter acuity also does not guarantee recovering fine stereo depth.
Eye-teaming problems. For symptomatic convergence insufficiency in children, office-based vergence and accommodative therapy with home reinforcement beat placebo therapy — 73% successful or improved versus 35% (CITT, 2008) — and a Cochrane network meta-analysis confirmed superiority to placebo in children (Scheiman et al., 2020). The limit matters just as much: the largest follow-up trial found the same therapy did not improve reading comprehension more than placebo (CITT-ART, 2019). It treats the eye-teaming problem, not reading itself.
Teenagers and adults. The old assumption that adult realignment is purely cosmetic has not held up. In a prospective series of 23 patients aged 14 to 85 with strabismus acquired after binocular vision had matured, 96% achieved measurable stereoacuity after successful realignment, with better results when the turn had been present 12 months or less and alignment afterwards was precise (Fawcett et al., 2004). In 15 people aged 12 to 40 with longstanding strabismus and acuity of 20/60 or better, none suppressed six weeks after surgery, 13 fused at near and 13 showed stereopsis on Titmus testing (Fatima et al., 2009). These are small, uncontrolled series — grounds for real hope, not a guarantee.
Sport. Depth judgment obviously matters in sports vision. Training programs rest on the plausible idea that demanding visual tasks sharpen how fast you process and respond to what you see, but the supporting research is uneven, as its own reviewers note (Appelbaum & Erickson, 2018).
How we approach it at Vision & Learning Center
A depth perception complaint is a symptom, not a diagnosis. Our job is to find which part of the system is producing it: refractive error, a suppressed eye, an eye turn, an eye-teaming or focusing problem, or something that needs a medical referral. That means measuring alignment at distance and near, fusional ranges, focusing and stereoacuity — not just reading a letter chart. What we find decides the plan: glasses, amblyopia and strabismus care, vision therapy, a co-managed surgical referral, or simply reassurance and a recheck. For the wider picture of how the two eyes work as a team, start with our guide to binocular vision dysfunction.
If you or your child bumps into doorframes, misjudges stairs or a poured glass, finds catching hard, or cannot see the effect in a 3D movie, a comprehensive developmental vision evaluation is the place to start. Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
At what age should a child have depth perception?
It is not present at birth. The American Optometric Association describes the eyes becoming capable of working together to form a three-dimensional view at around the fifth month, and eye-hand coordination and depth perception being well developed by age two. The American Academy of Ophthalmology similarly says depth perception has developed more fully at about five months. Fine detail keeps improving for years: on the Randot Preschool test, average stereoacuity goes from about 100 arcseconds at age three to 40 arcseconds by age seven.
Can you have depth perception with only one working eye?
You can judge depth, but less precisely. The brain also uses one-eyed cues such as relative size, overlap, shading, perspective and motion. People who lose stereo vision usually adapt, though fine tasks within arm's reach - pouring a glass, threading a needle, placing small pegs - tend to stay harder. In one study of 143 people aged 10 to 30, pegboard, bead-threading and water-pouring performance tracked stereoacuity, and those with normal stereoacuity did best on every task. A review of amblyopia and stereopsis adds that reduced stereo depth may also make sport and moving about safely harder.
Does watching a 3D movie tell me whether my depth perception is normal?
No. When researchers degraded binocular vision step by step in 57 people aged 16 to 62, depth identification on a handheld 3D game stayed at 100% until one eye was actually suppressed, because motion on screen supplies depth cues that a static clinical test does not. Enjoying a 3D film does not rule out a stereo problem - and finding 3D films flat, uncomfortable or headache-inducing is worth mentioning at an eye exam.
Can an adult regain depth perception after an eye turn is straightened?
Sometimes, and more often than was once assumed. In a prospective series of 23 patients aged 14 to 85 with strabismus acquired after binocular vision had matured, 96% achieved measurable stereoacuity after successful realignment, with better results when the eye turn had been present 12 months or less and alignment was precise. A separate series of 15 people aged 12 to 40, median age 18, with longstanding strabismus found most regained fusion and some stereopsis six weeks after successful surgery - so that second series was partly adolescent, not purely adult. These are small studies, and results vary from person to person.
Will vision therapy fix poor depth perception?
It depends on the cause. For symptomatic convergence insufficiency in children, office-based vergence and accommodative therapy with home reinforcement beat placebo therapy in a randomized trial (73% successful or improved versus 35%), and a Cochrane network meta-analysis confirmed superiority to placebo in children. It is not a substitute for glasses, patching or surgery when those are what the eye needs, and the largest trial of the same therapy found no benefit for reading scores over placebo.
Where This Information Comes From
- O'Connor AR, Birch EE, Anderson S, Draper H; FSOS Research Group (2010). The functional significance of stereopsis. Investigative Ophthalmology & Visual Science. : In 143 participants aged 10-30, pegboard and bead-threading performance was related to stereoacuity, with normal-stereo participants performing best on all tests.
- Tidbury LP, Black RH, O'Connor AR (2015). Clinical Assessment of Stereoacuity and 3-D Stereoscopic Entertainment. Strabismus. : In 57 participants aged 16 to 62 with binocular vision degraded in steps, depth identification on a Nintendo 3DS stayed at 100% until one eye was suppressed; motion in stereoscopic video supplies depth cues that static clinical tests do not.
- American Optometric Association. Infant Vision: Birth to 24 Months of Age. aoa.org patient education page. : States depth perception is not present at birth, that the eyes become capable of working together to form a three-dimensional view at around the fifth month, and that eye-hand coordination and depth perception should be well developed by age two.
- American Academy of Ophthalmology (Boyd K, reviewed by Lipsky SN). Vision Development: Newborn to 12 Months. aao.org EyeSmart patient education page. : In the first two months the eyes may appear to cross or wander; by three months they should work together to focus and track; depth perception has developed more fully at around five months.
- Birch E, Williams C, Drover J, et al. (2008). Randot Preschool Stereoacuity Test: normative data and validity. Journal of AAPOS. : In 4,355 normally sighted children aged 3-18, mean stereoacuity improved from 100 arcsec at age 3 to 60 arcsec by age 5 and 40 arcsec by age 7.
- Read JCA, Rafiq S, Hugill J, et al. (2019). Characterizing the Randot Preschool stereotest: Testability, norms, reliability, specificity and sensitivity in children aged 2-11 years. PLoS ONE. : Testability was 65% at age 2, 92% at age 3 and about 100% thereafter; specificity exceeded 95% but sensitivity for detecting visual problems was under 50%.
- Fu Z, Hong H, Su Z, Lou B, Pan CW, Liu H (2020). Global prevalence of amblyopia and disease burden projections through 2040: a systematic review and meta-analysis. British Journal of Ophthalmology. : Pooling 60 studies, global amblyopia prevalence was 1.44% (95% CI 1.17-1.78), and 2.41% in North America.
- Multi-ethnic Pediatric Eye Disease Study Group (2008). Prevalence of amblyopia and strabismus in African American and Hispanic children ages 6 to 72 months. Ophthalmology. : In 6,014 Los Angeles preschoolers, strabismus was found in 2.4-2.5% and amblyopia in 1.5-2.6%; 78% of amblyopia was attributable to refractive error.
- Levi DM, Knill DC, Bavelier D (2015). Stereopsis and amblyopia: A mini-review. Vision Research. : Impaired stereoscopic depth perception is the most common deficit in amblyopia under ordinary binocular viewing and can affect motor coordination, sport and mobility.
- Hashemi H, Pakzad R, Heydarian S, et al. (2019). Global and regional prevalence of strabismus: a comprehensive systematic review and meta-analysis. Strabismus. : Across 56 articles and 229,396 participants, pooled prevalence of any strabismus was 1.93% (exotropia 1.23%, esotropia 0.77%).
- Friedman DS, Repka MX, Katz J, et al. (2009). Prevalence of amblyopia and strabismus in white and African American children aged 6 through 71 months: the Baltimore Pediatric Eye Disease Study. Ophthalmology. : Manifest strabismus was found in 3.3% of white and 2.1% of African American Baltimore preschoolers.
- Rouse MW, Borsting E, Hyman L, et al.; CIRS Group (1999). Frequency of convergence insufficiency among fifth and sixth graders. Optometry and Vision Science. : Among 453 fifth- and sixth-graders, 4.2% had definite and 8.8% high-suspect convergence insufficiency (about 13% combined).
- Cotter SA, Edwards AR, Wallace DK, et al.; Pediatric Eye Disease Investigator Group (2006). Treatment of anisometropic amblyopia in children with refractive correction. Ophthalmology. : In 84 children aged 3 to under 7 with untreated anisometropic amblyopia, spectacles alone improved acuity by 2 or more lines in 77% and resolved the amblyopia in 27%.
- Pediatric Eye Disease Investigator Group (2002). A randomized trial of atropine vs. patching for treatment of moderate amblyopia in children. Archives of Ophthalmology. : In 419 children under 7 with moderate amblyopia, patching and atropine produced improvement of similar magnitude (success 79% vs 74%); both were judged appropriate initial treatments.
- Pediatric Eye Disease Investigator Group; Scheiman MM, Hertle RW, Beck RW, et al. (2005). Randomized trial of treatment of amblyopia in children aged 7 to 17 years. Archives of Ophthalmology. : Among 7-12-year-olds, 53% responded (10 or more letters) to patching plus near activities plus atropine versus 25% with optical correction alone; most were left with a residual acuity deficit.
- Holmes JM, Lazar EL, Melia BM, et al.; Pediatric Eye Disease Investigator Group (2011). Effect of age on response to amblyopia treatment in children. Archives of Ophthalmology. : Pooled individual data from four PEDIG trials found children aged 7 to under 13 significantly less responsive than children aged 3-7, though some older children still responded markedly.
- Pineles SL, Aakalu VK, Hutchinson AK, et al. (2020). Binocular Treatment of Amblyopia: A Report by the American Academy of Ophthalmology. Ophthalmology. : Reviewing 20 studies, the AAO found no level I evidence that binocular (dichoptic) treatment can substitute for patching or optical treatment.
- Xiao S, Angjeli E, Wu HC, et al.; Luminopia Pivotal Trial Group (2022). Randomized Controlled Trial of a Dichoptic Digital Therapeutic for Amblyopia. Ophthalmology. : In 105 children aged 4-7, a dichoptic digital therapeutic plus glasses improved amblyopic-eye acuity 1.8 lines versus 0.8 lines with glasses alone; the comparator was not patching.
- Convergence Insufficiency Treatment Trial Study Group (2008). Randomized clinical trial of treatments for symptomatic convergence insufficiency in children. Archives of Ophthalmology. : In 221 children, 73% were successful or improved after 12 weeks of office-based vergence/accommodative therapy versus 35% with office placebo.
- Scheiman M, Kulp MT, Cotter SA, Lawrenson JG, Wang L, Li T (2020). Interventions for convergence insufficiency: a network meta-analysis. Cochrane Database of Systematic Reviews. : Across 12 trials and 1,289 participants, office-based vergence/accommodative therapy was superior to placebo in children (RR 3.04); adult evidence was weaker.
- CITT-ART Investigator Group (2019). Effect of Vergence/Accommodative Therapy on Reading in Children with Convergence Insufficiency: A Randomized Clinical Trial. Optometry and Vision Science. : In 310 children, reading comprehension improved 3.7 points with therapy and 3.8 with placebo - no reading benefit.
- Fawcett SL, Stager DR Sr, Felius J (2004). Factors influencing stereoacuity outcomes in adults with acquired strabismus. American Journal of Ophthalmology. : In a prospective series of 23 adults aged 14-85 with acquired strabismus, 96% achieved measurable stereoacuity after successful realignment; outcomes were better with strabismus of 12 months or less and precise postoperative alignment.
- Fatima T, Amitava AK, Siddiqui S, Ashraf M (2009). Gains beyond cosmesis: Recovery of fusion and stereopsis in adults with longstanding strabismus following successful surgical realignment. Indian Journal of Ophthalmology. : In 15 patients aged 12 to 40 (median 18) with longstanding strabismus and acuity of 20/60 or better, none suppressed at six weeks; 13 fused at near and 13 showed Titmus stereopsis, 10 on TNO.
- American Optometric Association (2017). Evidence-Based Clinical Practice Guideline: Comprehensive Pediatric Eye and Vision Examination. St. Louis: AOA. : Recommends a comprehensive eye examination at 6-12 months, at least once between ages 3 and 5, and before first grade and annually thereafter.
- Appelbaum LG, Erickson G (2018). Sports vision training: A review of the state-of-the-art in digital training techniques. International Review of Sport and Exercise Psychology. : Reviews digital, perceptual-learning and virtual-reality sports vision training and notes that supporting research is uneven.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.