The Vision Problem Behind School Struggles
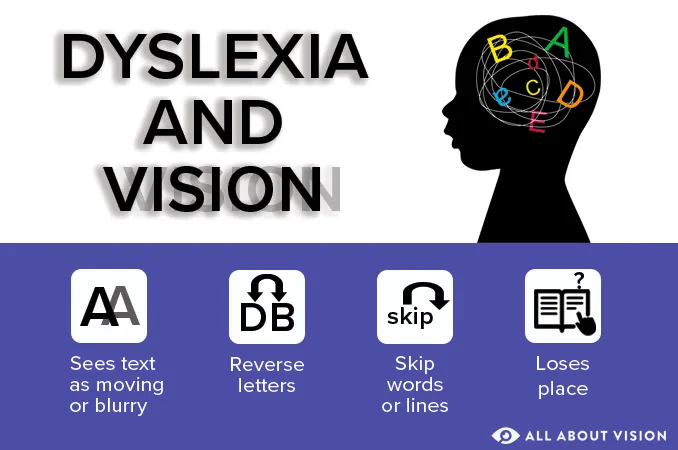
Reading, writing and math are the foundation of school. When a bright, motivated child is not performing near their potential, most parents start searching, and the first answers back are dyslexia, dysgraphia and dyscalculia. Those are real and important. But another possibility rarely makes the first page of results: a functional vision problem — a difficulty with how the eyes aim, focus, track and work together, rather than with how sharply they see.
These problems routinely slip past the vision checks done at school and in the pediatrician’s office, and they can quietly tax every part of a school day that happens at arm’s length or closer.
Key takeaways
- “Functional vision” describes how the eyes team, focus and track — not how small a letter your child can read on a chart. A child can pass a screening at 20/20 and still be uncomfortable at 16 inches.
- Convergence insufficiency, one of the more common functional problems, met a high-suspect or definite definition in about 13% of fifth- and sixth-graders in a US school-based study — that count was based on clinical signs, not on symptoms (Rouse et al., 1999).
- Vision problems do not cause dyslexia, and vision therapy is not a treatment for dyslexia or learning disabilities (AAP/AAO/AAPOS/AACO, 2009).
- The largest trial to test it found vision therapy no better than placebo for reading comprehension (CITT-ART, 2019). We treat vision problems to make near work comfortable, not to raise reading scores.
- A developmental vision evaluation answers one clear question and can run alongside tutoring, an IEP or a reading intervention.
What “functional vision” actually means
Reading is not a smooth glide across the page. The eyes move in short jumps called saccades and pause on a word for a fraction of a second, and those pauses are where the reading actually happens (Rayner, 1998). For that to work at book distance, both eyes must turn inward the same amount (convergence), hold a clear focus (accommodation), sustain both for twenty minutes or more, and hand off cleanly from line to line. Any of those can be underdeveloped while distance acuity is perfect — the part parents are almost never told.
Why screenings miss these problems
A screening is built to catch a specific set of things — mostly reduced acuity, amblyopia and its risk factors. The US Preventive Services Task Force recommends screening at least once between ages 3 and 5 for exactly that purpose (USPSTF, 2017). It is a worthwhile screen, but it is not an eye examination, and it was never built to test eye teaming or focusing at near.
The AOA’s pediatric guideline puts numbers on the gap: acuity testing alone missed 75.5% of children who turned out to have binocular and eye-movement problems on a complete examination, and only 38.7% of children who failed a school screening received any follow-up care (AOA, 2017). More detail in what school vision screenings miss.
Why your child may be struggling in reading
Functional vision problems affect reading in two ways, depending on where your child is in their development.
Learning to read. A beginning reader is building a visual memory for letters and numbers while also decoding sound. If holding the page clear and single takes effort, that effort can compete for attention the child needs elsewhere. Whether that alone is enough to slow a beginning reader down is not settled — as the research section below says plainly, most struggling readers are not struggling because of their eyes.
Reading to learn. By third or fourth grade the job changes: children read for meaning, for longer, with less support. If words go blurry or double after a few minutes, the child spends effort holding the page single and clear — effort no longer available for comprehension. They read word by word instead of in phrases, reread lines, and tire well before the assignment is done.
Clinical samples do show more of these findings in struggling readers. Children with developmental dyslexia had accommodation deficits at 55% versus 9% of typical readers and tracking deficits at 62% versus 15%, though the authors were explicit that the cause and clinical relevance are uncertain (Raghuram et al., 2018). A survey of 825 children referred for reading and writing difficulty found lower accommodative amplitude, reduced focusing and eye-teaming facility and a receded near point of convergence compared with controls (Dusek et al., 2010). More in reading difficulties and vision.
Why your child may be struggling in writing and spelling
Writing asks vision to lead the hand, and asks visual memory to supply the shape of the word. The skills below are the ones we measure when handwriting or spelling is the reason a family comes in. Read them as the clinical framework we test, not as established causes of a learning problem — the research section further down sets out where that evidence actually stands:
- Peripheral awareness — noticing the margin and the line while the eyes are busy at the pencil tip, so writing stays straight.
- Visual-spatial organization — planning how letters and words sit together. Children who struggle here squeeze words together, vary letter size and drift off the line.
- Laterality and directionality — telling apart shapes that differ only in orientation, like b, d, p and q. Reversals are common in young writers and also occur in language-based reading difficulty, so we treat them as one observation among many rather than as evidence of a vision problem.
- Visualization and visual recall — holding a mental picture of a word without looking at it, which is what spelling from memory requires.
Research supports part of that picture. In 118 elementary students, visual-motor integration predicted handwriting legibility in first grade, while eye-hand coordination and pencil stroke force predicted it in second grade (Lee et al., 2016). Broader visual-perceptual measures also track with achievement: in 155 children in grades 2 to 4, visual perception and motor coordination scores predicted math and reading achievement after partially controlling for verbal school ability and age (Sortor & Kulp, 2003).
In the office we often see where in a writing sample a child stopped looking — the letters hold together for two lines, then loosen. See handwriting and math.

Why your child may be struggling in math
Math leans on vision in its own ways. The list below describes what we look at in the examination room when a child’s math work does not match their understanding of the material. It is our clinical framework, not a demonstrated cause of math difficulty:
- Seeing detail that changes meaning. Decimal points and operation signs are small, and they are easy to lose track of when keeping the page clear is already taking effort.
- Keeping place and alignment. Columns in long multiplication or division have to line up, so a child who organizes space poorly on the page can use a correct method and still arrive at a wrong answer.
- Order and orientation. Reading 31 as 13, or mixing up b and d, is something parents and teachers report often. Reversals like these are common in early writing and also occur in language-based reading difficulty, so we record them without assuming vision is the reason.
- Visualizing quantity. Children who do not readily picture numbers tend to count on fingers or say sequences out loud. Given unlimited time they often get there; on timed tests they usually do not.
The research touching this is correlational, not causal. In 155 children in grades 2 to 4, visual perception and motor coordination scores predicted math and reading achievement after partially controlling for verbal school ability and age (Sortor & Kulp, 2003). That tells us these skills travel with achievement. It does not tell us that training them raises math scores.
A child with a functional vision problem may do better in math than in reading: math demands shorter bursts of sustained near focus than a chapter book does, so some children keep up in math and only fall behind on word problems.

What the research shows — and where it stops
The positions differ. The American Academy of Pediatrics, with the AAO, AAPOS and AACO, holds that dyslexia is a language-based disorder, that vision problems can interfere with learning but are not the cause of dyslexia, and that eye exercises, behavioral vision therapy and tinted lenses are not supported for treating learning disabilities (Joint statement, 2009; Handler & Fierson, 2011). The optometric position is that vision problems can and often do interfere with learning, and that optometric care belongs alongside educational care rather than instead of it (AAO/AOA, 1997).
The population data are sobering. In 5,822 children from a UK birth cohort, four out of five with severe reading impairment had entirely normal ophthalmic function, and no association was found with convergence, accommodation, strabismus or refractive error. The one exception was depth perception: stereoacuity worse than 60 arcseconds was somewhat more common in the severe-reading group, about 1 in 6 versus 1 in 10, a difference the authors themselves treat as of unclear meaning (Creavin et al., 2015). Most struggling readers are not struggling because of their eyes.
Treating vision does not treat reading. CITT-ART randomized 310 children with symptomatic convergence insufficiency: reading comprehension improved 3.7 points with 16 weeks of office-based therapy versus 3.8 points with placebo (CITT-ART, 2019). Vision therapy in children with learning disorders likewise improved binocular measures — the only outcomes that study assessed (Hussaindeen et al., 2018).
What treating vision does do. The same body of work shows office-based vergence and accommodative therapy is effective for the symptoms and signs of convergence insufficiency: 73% of children were successful or improved after 12 weeks versus 35% on office placebo (CITT, 2008). Discomfort at near is not academically trivial — children with symptomatic CI showed more problem behaviors on an academic behavior survey than children with normal binocular vision, even without ADHD (Rouse et al., 2009) — and uncorrected moderate farsightedness is associated with lower early-literacy scores in preschoolers (VIP-HIP, 2016).
Our clinical perspective, stated as such: we do not treat dyslexia and we do not promise better grades. What we can do is find out whether your child is fighting their own visual system to get through homework, and if so, treat it, so discomfort at near is not one more thing working against them.
How we pinpoint a functional vision problem
These categories overlap — a child may have more than one functional problem, and the ripple effect shows up across subjects. At Vision & Learning Center we test well beyond the acuity chart: near point of convergence, fusional vergence ranges, accommodative amplitude and facility, eye-movement accuracy, visual-motor integration and visual-perceptual skills, along with a full refraction and ocular health check.
If a treatable problem turns up, our vision therapy programs commonly run 18 to 24 weekly in-office sessions, with home practice 3 to 4 days a week for 15 to 20 minutes; a twice-weekly option exists for families who cannot practice consistently at home. What each program includes is set out on our vision therapy cost page. If nothing significant turns up, that is useful too — it moves the search on to reading instruction, an educational evaluation or another specialist without a year spent wondering. The bigger picture is in our guide to vision and learning.
Next steps for parents
- Watch the pattern, not just the grade — skipping lines, losing place, covering an eye, headaches after homework, avoiding reading, handwriting that degrades down the page.
- Keep the school process moving. Reading intervention, tutoring and educational testing should not pause while vision is checked.
- Have the visual question answered properly rather than left to a screening’s guess.
If your child is working harder than their classmates for less, a comprehensive eye and vision examination is a reasonable next step. Schedule an evaluation at our Boynton Beach or Boca Raton office and we will tell you plainly what we find.
Common Questions About This Topic
Can my child have 20/20 vision and still have a functional vision problem?
Yes. An acuity chart measures how small a letter your child can identify at distance. It does not measure how well the two eyes aim and sustain focus together up close. The AOA's pediatric guideline notes that Snellen acuity alone missed 75.5% of the children later found to have binocular and eye-movement problems on a complete examination.
Do functional vision problems cause dyslexia?
No. Pediatric and ophthalmology organizations state that dyslexia is language-based and that vision problems are not its cause, and we agree. A child can have dyslexia and a separate, treatable focusing or eye-teaming problem at the same time. Each needs its own care.
Will vision therapy raise my child's reading scores?
The largest trial to test that question, CITT-ART, found that 16 weeks of office-based vergence and accommodative therapy improved reading comprehension no more than placebo therapy. We treat vision problems so near work is more comfortable, not as a substitute for reading instruction.
How do I know whether to start with vision, tutoring or an educational evaluation?
You do not have to choose. A comprehensive developmental vision evaluation answers one specific question - whether the visual system is working comfortably for near work - and it can run alongside school-based testing, tutoring or reading intervention.
At what age should my child be examined?
The AOA recommends a comprehensive eye examination at 6 to 12 months, at least once between ages 3 and 5, and before first grade with annual examinations after that. If your child is already struggling, do not wait for the next scheduled visit.
Where This Information Comes From
- American Optometric Association (2017). Evidence-Based Clinical Practice Guideline: Comprehensive Pediatric Eye and Vision Examination. St. Louis: AOA. : Recommends comprehensive exams at 6-12 months, once at 3-5 and annually from first grade; reports that Snellen acuity alone missed 75.5% of children found to have binocular and oculomotor problems, and that only 38.7% of screening failures received follow-up care.
- US Preventive Services Task Force; Grossman DC, Curry SJ, Owens DK, et al. (2017). Vision Screening in Children Aged 6 Months to 5 Years: US Preventive Services Task Force Recommendation Statement. JAMA. : Recommends screening at least once at ages 3-5 to detect amblyopia and its risk factors; evidence insufficient under age 3.
- Rouse MW, Borsting E, Hyman L, et al.; CIRS Group (1999). Frequency of convergence insufficiency among fifth and sixth graders. Optometry and Vision Science. : About 13% of 453 fifth- and sixth-graders met a high-suspect or definite convergence insufficiency definition; 78.9% of three-sign CI children also had accommodative insufficiency.
- Rayner K (1998). Eye movements in reading and information processing: 20 years of research. Psychological Bulletin. : Landmark review showing reading proceeds through saccades and fixations and that eye-movement patterns reflect moment-to-moment cognitive processing.
- Raghuram A, Gowrisankaran S, Swanson E, Zurakowski D, Hunter DG, Waber DP (2018). Frequency of Visual Deficits in Children With Developmental Dyslexia. JAMA Ophthalmology. : Accommodation deficits in 55% vs 9% and tracking deficits in 62% vs 15% of children with dyslexia vs typical readers; authors call the cause and clinical relevance uncertain.
- Dusek W, Pierscionek BK, McClelland JF (2010). A survey of visual function in an Austrian population of school-age children with reading and writing difficulties. BMC Ophthalmology. : 825 children referred for reading and writing difficulty had lower accommodative amplitude, reduced accommodative and vergence facility and a receded near point of convergence versus 328 controls.
- Creavin AL, Lingam R, Steer C, Williams C (2015). Ophthalmic abnormalities and reading impairment. Pediatrics. : In 5822 children, four of five with severe reading impairment had normal ophthalmic function and no association was found with convergence, accommodation, strabismus or refractive error; stereoacuity worse than 60 arcsec was slightly more common (1 in 6 vs 1 in 10).
- Sortor JM, Kulp MT (2003). Are the results of the Beery-Buktenica Developmental Test of Visual-Motor Integration and its subtests related to achievement test scores? Optometry and Vision Science. : In 155 children in grades 2-4, visual perception and motor coordination scores predicted math and reading achievement after partially controlling for verbal school ability and age; correlational, not causal.
- Lee TI, Howe TH, Chen HL, Wang TN (2016). Predicting Handwriting Legibility in Taiwanese Elementary School Children. American Journal of Occupational Therapy. : In 118 children, visual-motor integration predicted handwriting legibility in first grade while eye-hand coordination and stroke force predicted it in second grade.
- VIP-HIP Study Group; Kulp MT, Ciner E, Maguire M, et al. (2016). Uncorrected Hyperopia and Preschool Early Literacy (VIP-HIP). Ophthalmology. : Uncorrected moderate hyperopes scored 4.3 points lower on an early-literacy test than emmetropic peers, with larger gaps when near acuity or near stereoacuity was reduced.
- Rouse M, Borsting E, Mitchell GL, et al.; CITT Study Group (2009). Academic behaviors in children with convergence insufficiency with and without parent-reported ADHD. Optometry and Vision Science. : Academic Behavior Survey scores were higher (more problems) in children with symptomatic CI without ADHD than in children with normal binocular vision.
- American Academy of Pediatrics, American Academy of Ophthalmology, AAPOS, AACO (2009). Joint statement - Learning disabilities, dyslexia, and vision. Pediatrics. : Holds that dyslexia is language-based, that vision problems can interfere with learning but do not cause dyslexia, and that evidence does not support vision therapy or tinted lenses for learning disabilities.
- Handler SM, Fierson WM; AAP, AAO, AAPOS, AACO (2011). Learning disabilities, dyslexia, and vision. Pediatrics. : Technical report stating that effective treatment for dyslexia is evidence-based reading instruction, not visual training or colored lenses.
- American Academy of Optometry; American Optometric Association (1997). Vision, learning and dyslexia: a joint organizational policy statement. Journal of the American Optometric Association. : Optometric position that vision problems can and often do interfere with learning and that optometric care is one part of a multidisciplinary approach.
- Convergence Insufficiency Treatment Trial Study Group (2008). Randomized clinical trial of treatments for symptomatic convergence insufficiency in children. Archives of Ophthalmology. : In 221 children, 73% were successful or improved after 12 weeks of office-based vergence/accommodative therapy versus 35% with office placebo.
- CITT-ART Investigator Group (2019). Effect of Vergence/Accommodative Therapy on Reading in Children with Convergence Insufficiency: A Randomized Clinical Trial. Optometry and Vision Science. : In 310 children, reading comprehension improved 3.7 points with therapy versus 3.8 with placebo - no reading benefit over placebo.
- Hussaindeen JR, Shah P, Ramani KK, Ramanujan L (2018). Efficacy of vision therapy in children with learning disability and associated binocular vision anomalies. Journal of Optometry. : Binocular vision anomalies in 62.8% of 94 children with specific learning disorders; vision therapy improved binocular measures, which were the only outcomes assessed.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.