Computer Vision Syndrome: Causes, Symptoms, Relief

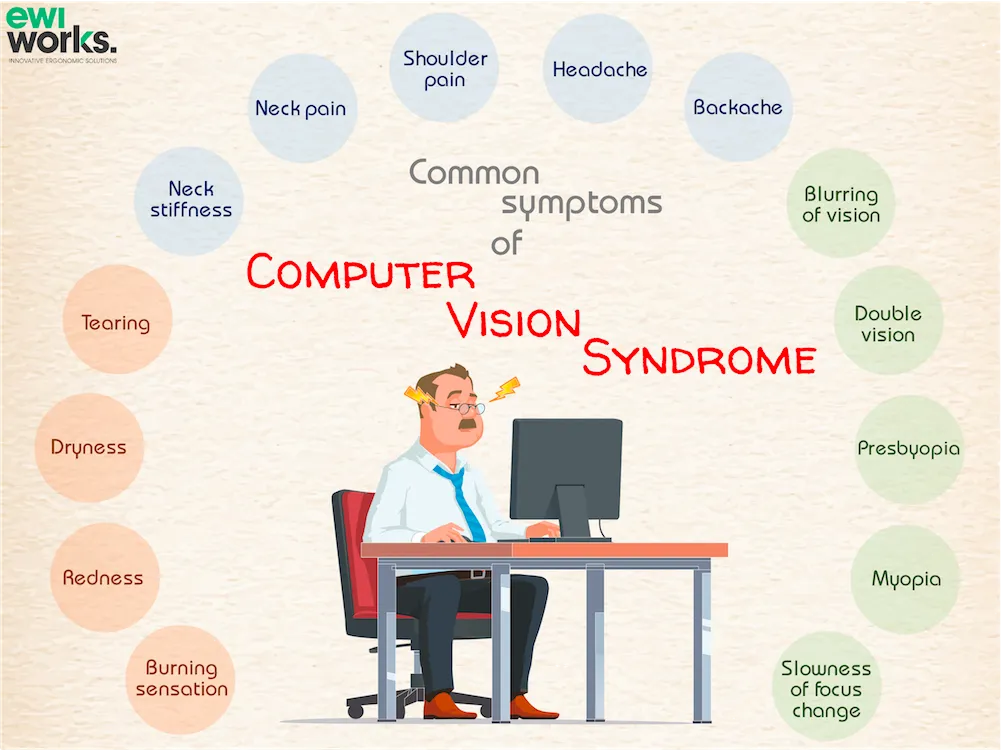
Most of us now spend the working day, and much of the evening, looking at a screen. For many people that brings tired, gritty eyes, a dull headache by mid-afternoon, and print that will not stay sharp. Eye-care professionals call this cluster computer vision syndrome (CVS), or digital eye strain. Most of it is manageable once you know which kind of eye strain you have.
Key takeaways
- Computer vision syndrome is a group of symptoms tied to prolonged screen use, not a single disease (American Optometric Association).
- Symptoms fall into two groups, focusing/eye-teaming strain and dry-eye irritation, and they are managed differently (Sheppard & Wolffsohn, 2018).
- An accurate prescription, a well-placed screen and glare control are the best-supported fixes, and complete blinking is a sensible habit. Blue-light glasses are not.
- Eye strain that persists despite good habits often traces to a treatable focusing or eye-teaming problem.
What computer vision syndrome is
The American Optometric Association describes CVS as a group of eye- and vision-related problems that result from prolonged computer, tablet, e-reader and cell phone use, and says people who spend two or more continuous hours a day on a screen are at greatest risk. The most common symptoms are eyestrain, headaches, blurred vision, dry eyes, and neck and shoulder pain (AOA). In our offices we also hear about print that swims or doubles after 20 to 30 minutes and slow refocusing from screen to room.
Researchers split the symptoms into two categories (Sheppard & Wolffsohn, 2018):
- Internal symptoms: eye strain, an ache behind the eyes, headache, blurred or doubled print. These come from the sustained focusing (accommodation) and eye-teaming (vergence) effort near work demands.
- External symptoms: burning, dryness, irritation and watering. These come from the eye’s surface drying out, largely because blinking becomes less frequent and less complete at a screen (Rosenfield, 2011).
The distinction matters because the fixes differ: artificial tears will not help a focusing problem, and a new prescription will not fix a dry eye.
How common is it?
Figures vary because studies use different questionnaires and populations. One review estimated that digital eye strain may affect 50% or more of computer users (Sheppard & Wolffsohn, 2018). A 2024 meta-analysis of 103 studies and more than 66,000 people found a pooled prevalence of 69%, higher in women and university students, though the studies were extremely varied and relied on self-report (Ccami-Bernal et al., 2024).
What causes it
Several factors usually stack up together:
- Screen quality and glare. On-screen letters are less sharply defined than print, contrast is lower, and reflections make the eyes work harder (AOA).
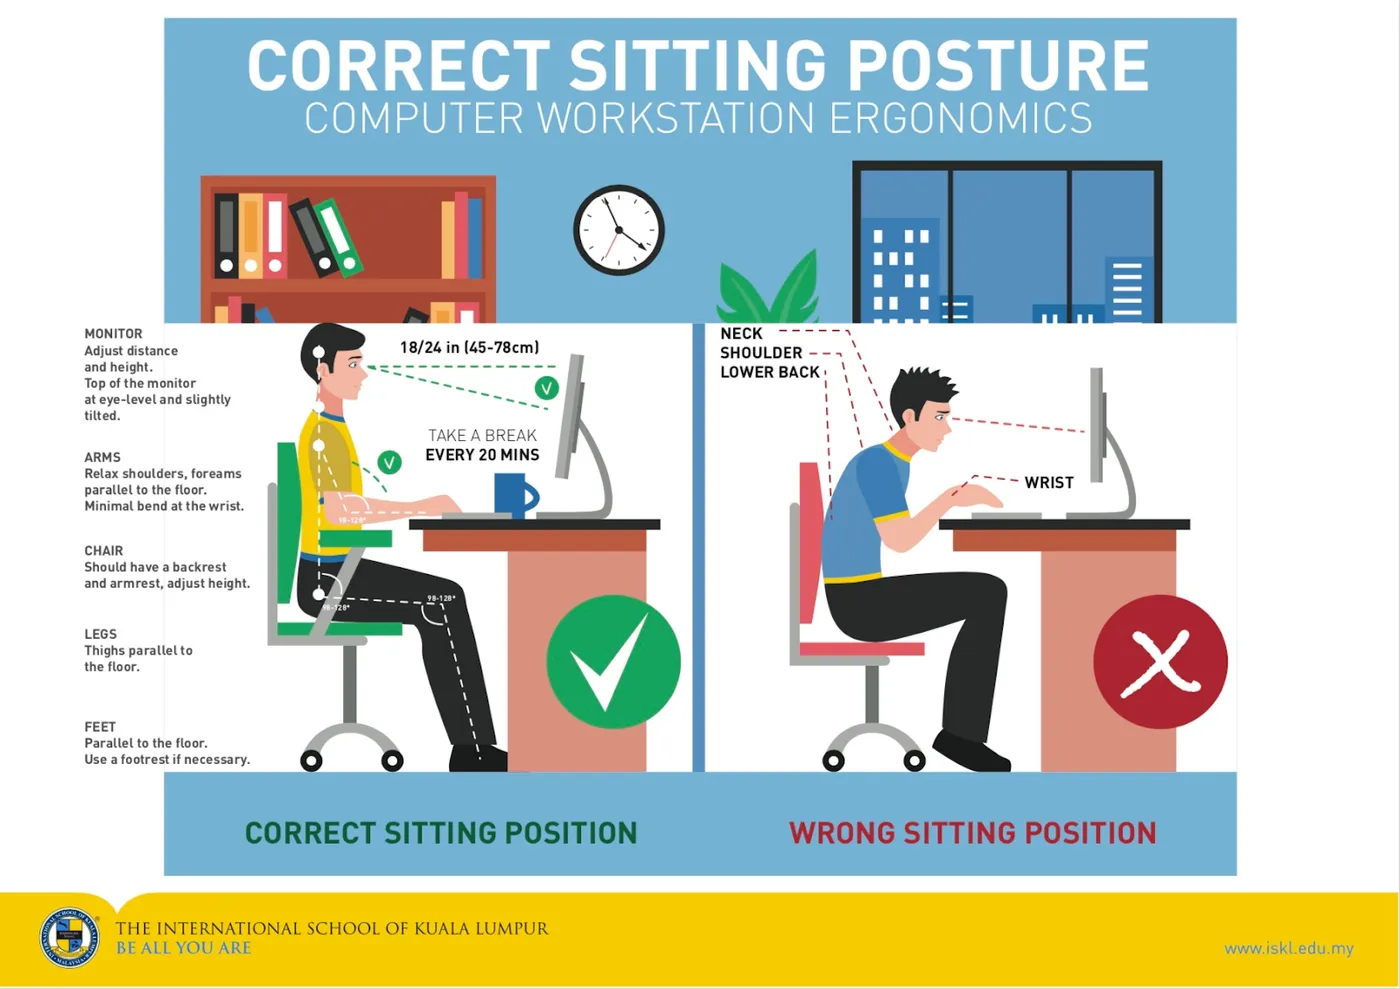
- Viewing distance and posture. A screen that is too close, too high, or placed so you keep turning your head raises the focusing and eye-teaming load and strains the neck (AOA).
- An uncorrected or under-corrected prescription. Small errors become noticeable over hours of near work; the AOA calls this a major contributing factor (AOA).
- Incomplete blinking. During computer work people blinked about 12 times a minute, 16% of blinks did not fully close the eye, and symptom scores rose with the share of incomplete blinks (Portello et al., 2013).
- Focusing and eye-teaming weakness. Alongside dry eye, accommodation and vergence anomalies are identified as the principal causes of CVS (Rosenfield, 2011).
What about blue light? Screens do emit it, but a 2023 Cochrane review of 17 randomized trials found blue-light-filtering lenses may make no difference to eye strain and probably do not improve visual acuity (Singh et al., 2023), so we do not recommend them for this purpose. We go deeper in The hype and reality of blue-light glasses.
Prevention: what is worth doing
Most screen-comfort advice is expert consensus rather than trial-proven. The most cited review of the subject concluded that the efficacy of proposed treatments for CVS is unproven (Rosenfield, 2011), so here is each step with its evidence stated plainly.
-
Get the prescription right. The AOA recommends a yearly comprehensive eye exam for computer users; that exam is also how CVS is diagnosed (AOA). Ask about lenses set for your working distance.
-
Set up the screen. Place it 15 to 20 degrees below eye level, measured from the center of the screen, and 20 to 28 inches from your eyes, with your feet flat on the floor (AOA).
-
Control glare. Keep the screen away from windows and overhead lights, and consider an anti-glare filter (AOA).
-
Blink fully, not just more often. Symptoms tracked the share of incomplete blinks, while prompting people to blink twice as often did not reduce symptoms (Portello et al., 2013). A few deliberate, complete blinks every page is a cheap habit we suggest to every screen worker.
-
Take breaks, but do not count on the magic numbers. The 20-20-20 rule (every 20 minutes, look into the distance for 20 seconds) is a sensible reminder (AOA).
The numbers themselves are not proven. A 2023 experiment gave young adults 20-second breaks every 5, 10 or 20 minutes during a 40-minute tablet task, and none of those schedules reduced symptoms compared with taking no breaks at all. The authors concluded that brief scheduled breaks are not a treatment (Johnson & Rosenfield, 2023). Take them if they help you. But if you need constant breaks to get through the day, that is a reason to have your focusing and eye teaming checked.
-
For children, the same principles apply, plus the question of total screen time. See our complete guide to how much screen time is too much and Screen time and kids.
When eye strain points to a focusing or eye-teaming problem
If you have done the basics and still get blur, doubling or headaches after 20 minutes at the screen, the problem is often not the screen. In a randomly sampled group of 175 university students, about 13% had a symptomatic accommodative or binocular problem, with convergence insufficiency the most common single diagnosis (Garcia-Munoz et al., 2016).
What the evidence says about treating these problems, honestly stated:
-
In children, office-based vergence and accommodative therapy has the strongest evidence.
In the Convergence Insufficiency Treatment Trial, 73% of children were successful or improved after 12 weeks, against 35% with placebo therapy (CITT Study Group, 2008). Focusing amplitude improved far more than with placebo as well, 9.9 D versus 2.2 D (Scheiman et al., 2011). The larger follow-up trial tempers that picture. In 311 children treated for 16 weeks, the eye-teaming measurements improved much more with therapy than with placebo, while symptom scores improved about as much in both groups (11.8 versus 10.4 points, p = .21) (CITT-ART, 2019). That is one reason we measure signs as well as symptoms.
-
In adults, the evidence is smaller and less clear (Scheiman et al., 2020). In one trial, 42% of therapy patients met symptom-elimination criteria, against 31% with placebo (Scheiman et al., 2005).
Adults over 45 have another option. In a small crossover trial of 29 presbyopic adults with convergence insufficiency, base-in prism reading lenses eased symptoms more than placebo reading lenses (Teitelbaum et al., 2009).
-
For isolated accommodative insufficiency, there is no high-quality evidence for a standard treatment; plus lenses and vision therapy have each shown benefit but have never been compared (Hussaindeen & Murali, 2020).
Our clinical perspective at Vision & Learning Center: when screen symptoms persist despite good habits and an accurate prescription, we measure how the eyes focus, converge and track, not just how well they read the chart. The plan may involve updated lenses, prism, dry-eye care, or vision therapy; we are candid that the strongest trial evidence is in children with convergence insufficiency and that adult results are more modest. Learn more on our computer vision syndrome and adult binocular vision dysfunction pages.
If screen work leaves your eyes tired, blurry or aching most days, a comprehensive vision evaluation is the right next step. Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
Do blue-light glasses help with computer eye strain?
Probably not. A 2023 Cochrane review of 17 randomized trials found that blue-light-filtering lenses may not reduce eye strain compared with standard lenses and probably have little or no effect on visual acuity. An accurate prescription and a well-positioned screen are better investments.
Does the 20-20-20 rule work?
It is a reasonable reminder to rest your eyes, but the specific numbers are not well supported. In a 2023 study, 20-second breaks every 5, 10 or 20 minutes did not reduce symptoms compared with no breaks during a 40-minute tablet task. Breaks are fine; they are not a treatment for persistent eye strain.
How far away should my computer screen be?
The American Optometric Association recommends placing the screen 20 to 28 inches from your eyes and 15 to 20 degrees below eye level, measured from the center of the screen, with glare from windows and overhead lights kept to a minimum and your feet flat on the floor.
Is computer vision syndrome the same as dry eye?
Not quite. Dry-eye irritation (burning, grittiness, watering) is one of the two symptom groups in computer vision syndrome. The other group (eye strain, headache, blur, doubled print) comes from the focusing and eye-teaming effort that screen work demands. Many people have both, and they are managed differently.
Can vision therapy help computer vision syndrome?
It depends on the cause. If an evaluation finds a convergence or accommodative problem, office-based vergence and accommodative therapy has the strongest trial evidence in children: it clearly improves the eye-teaming measurements, though the largest trial found symptom scores improved about as much with placebo therapy. Adult evidence is more limited and mixed. For dry-eye symptoms, blinking habits and lubrication matter more. A comprehensive evaluation sorts out which applies to you.
Where This Information Comes From
- American Optometric Association. Computer Vision Syndrome (patient information page). : Defines CVS/digital eye strain, lists the five most common symptoms and causes, and recommends a screen 15-20 degrees below eye level and 20-28 inches away, glare control, frequent blinking, 20-20-20 breaks and a yearly comprehensive eye exam; greatest risk with 2+ continuous hours of daily screen use.
- Sheppard AL, Wolffsohn JS (2018). Digital eye strain: prevalence, measurement and amelioration. BMJ Open Ophthalmology. : Review estimating digital eye strain may affect 50% or more of computer users; symptoms divide into accommodative/binocular (internal) and dry-eye (external) types; blue-light lens evidence mixed.
- Rosenfield M (2011). Computer vision syndrome: a review of ocular causes and potential treatments. Ophthalmic and Physiological Optics. : 64-90% of computer users report visual symptoms; principal causes are oculomotor (accommodation/vergence) anomalies and dry eye from reduced blink rate and amplitude; efficacy of proposed treatments described as unproven.
- Ccami-Bernal F, Soriano-Moreno DR, Romero-Robles MA, et al. (2024). Prevalence of computer vision syndrome: A systematic review and meta-analysis. Journal of Optometry. : Pooled prevalence of CVS 69.0% across 103 studies and 66,577 participants, higher in women (71.4%) and university students (76.1%); extreme heterogeneity and self-report questionnaires.
- Portello JK, Rosenfield M, Chu CA (2013). Blink rate, incomplete blinks and computer vision syndrome. Optometry and Vision Science. : During computer work mean blink rate was 11.6 per minute and 16.1% of blinks were incomplete; symptom score correlated with the percentage of incomplete blinks; raising blink rate to 23.5 per minute with an audible cue did not significantly reduce symptoms.
- Singh S, Keller PR, Busija L, et al. (2023). Blue-light filtering spectacle lenses for visual performance, sleep, and macular health in adults. Cochrane Database of Systematic Reviews. : Across 17 randomized trials, blue-light-filtering lenses may not reduce eye-strain symptoms versus standard lenses (low certainty), probably have little or no effect on visual acuity, and sleep evidence is indeterminate.
- Johnson S, Rosenfield M (2023). 20-20-20 Rule: Are These Numbers Justified? Optometry and Vision Science. : In 30 young adults doing a 40-minute tablet task, 20-second breaks every 5, 10 or 20 minutes had no significant effect on symptoms versus no breaks (P = .70); the authors conclude the results do not support 20-second scheduled breaks as a therapeutic intervention.
- Garcia-Munoz A, Carbonell-Bonete S, Canto-Cerdan M, Cacho-Martinez P (2016). Accommodative and binocular dysfunctions: prevalence in a randomised sample of university students. Clinical and Experimental Optometry. : In 175 randomly sampled university students aged 18-35, 13.15% had a symptomatic accommodative and/or binocular dysfunction; convergence insufficiency was the most common single diagnosis (3.43%).
- Convergence Insufficiency Treatment Trial Study Group (2008). Randomized clinical trial of treatments for symptomatic convergence insufficiency in children. Archives of Ophthalmology. : In 221 children aged 9-17, office-based vergence/accommodative therapy produced a successful or improved outcome in 73% after 12 weeks versus 35% with office placebo therapy.
- CITT-ART Investigator Group (2019). Treatment of Symptomatic Convergence Insufficiency in Children Enrolled in the Convergence Insufficiency Treatment Trial-Attention & Reading Trial. Optometry and Vision Science. : In 311 children treated over 16 weeks, near point of convergence and fusional vergence improved far more with office-based therapy than with placebo, but symptom scores improved about as much in both groups (11.8 versus 10.4 points, p = .21).
- Scheiman M, Cotter S, Kulp MT, et al.; CITT Study Group (2011). Treatment of accommodative dysfunction in children: results from a randomized clinical trial. Optometry and Vision Science. : 74% of CITT children also had accommodative dysfunction; accommodative amplitude rose 9.9 D with office-based therapy versus 2.2 D with placebo after 12 weeks.
- Scheiman M, Kulp MT, Cotter SA, Lawrenson JG, Wang L, Li T (2020). Interventions for convergence insufficiency: a network meta-analysis. Cochrane Database of Systematic Reviews. : Across 12 trials (1,289 participants), office-based vergence/accommodative therapy was more effective than placebo in children (RR 3.04); in adults the evidence for non-surgical treatment is less clear.
- Scheiman M, Mitchell GL, Cotter S, et al. (2005). A randomized clinical trial of vision therapy/orthoptics versus pencil pushups for the treatment of convergence insufficiency in young adults. Optometry and Vision Science. : In 46 adults aged 19-30, only office-based therapy significantly improved near point of convergence and fusional vergence, but symptom-elimination criteria were met by 42% with therapy versus 31% with placebo.
- Teitelbaum B, Pang Y, Krall J (2009). Effectiveness of base in prism for presbyopes with convergence insufficiency. Optometry and Vision Science. : Randomized crossover trial of 29 presbyopic adults: symptom score fell from 30.2 to 13.4 with base-in prism progressive lenses versus 23.6 with placebo progressives.
- Hussaindeen JR, Murali A (2020). Accommodative Insufficiency: Prevalence, Impact and Treatment Options. Clinical Optometry. : Reported prevalence of accommodative insufficiency ranges from under 1% to 61.6% depending on criteria; no high-quality evidence supports a standard treatment, and plus lenses and vision therapy have never been compared head-to-head.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.