Are Letter Reversals Always a Sign of Dyslexia?
A parent watches a six-year-old write her name, sees the b come out as a d, and a quiet worry starts: is this dyslexia? It is one of the most common questions we hear at Vision & Learning Center, and the honest answer surprises most families. Reversals are a normal part of learning to read and write, and on their own they are not a marker of dyslexia. Here is what is happening in your child’s brain, what the research shows, and when reversals are worth a closer look.
Key takeaways
- Letter reversals are typical in five- and six-year-olds and fade with reading and writing practice.
- Reading asks the brain to override a rule it uses everywhere else, so a period of confusion is expected.
- Dyslexia is language-based. Reversals alone do not diagnose it, and treating vision does not treat dyslexia.
- Reversals that persist well past age seven to eight, especially with other signs, are worth evaluating.
- A developmental vision evaluation rules visual problems in or out; it does not replace a reading evaluation.
Reading borrows a brain system built for something else
Spoken language comes naturally; children absorb it using brain regions that evolved for the job. Writing is only a few thousand years old, far too recent for evolution to have built a reading center. So the brain improvises: learning to read partially repurposes a patch of cortex that evolved to recognize objects and faces (Dehaene & Cohen, 2011).
That borrowed system comes with habits, and one of them is why your child writes backwards.
Object recognition has a rule that letters break
Look at these chairs.

Every one looks different, and you recognize all of them as chairs. A child who has never seen a rocking chair still calls it a chair. Now the same object from different angles.

Tilted, rotated, flipped left to right, it is still a chair. Vision researchers call the left-right part of this mirror invariance: the primate visual system deliberately ignores whether something faces left or right, because a tiger is a tiger from either side (Pegado et al., 2014).
Then a child meets b and d.
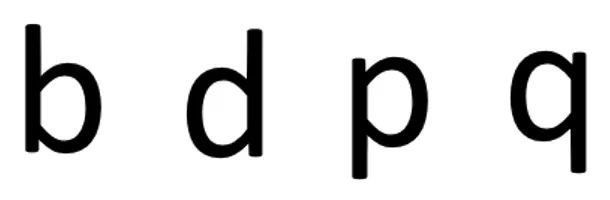
Same loop, same stick, different orientation. To a visual system doing exactly what it evolved to do, these are one object. To a reader, they are four letters. Learning to read means discovering that the rule your child has applied to every object in her life suddenly does not apply.
What the research shows about reversals
Reversals are not random and they are not rare. In a study of 300 typically developing five- and six-year-olds, mirror writing of digits and capital letters was common and followed a predictable pattern (Fischer, 2011). Children pick up on the fact that most characters in our alphabet face right, so they flip the ones that face left. In another study of 130 children the same age, left-facing forms such as d and J were reversed 57 percent of the time, while right-facing forms were reversed only 5 percent of the time (Treiman et al., 2014).
That same study followed the children for nearly three years. Children who turned out to be weaker readers made more letter-writing errors overall, but they were no more likely than their peers to make reversal errors specifically, and a child’s reversal pattern did not predict later reading skill.
Telling b from d is not something the brain learns once and files away, either. First, third and fifth graders all showed the same measurable cost of suppressing the mirror rule, and that cost did not shrink with age or reading skill (Ahr et al., 2016). The authors’ conclusion is that fluent reading does not erase the mirror rule; it overrides it, every time.
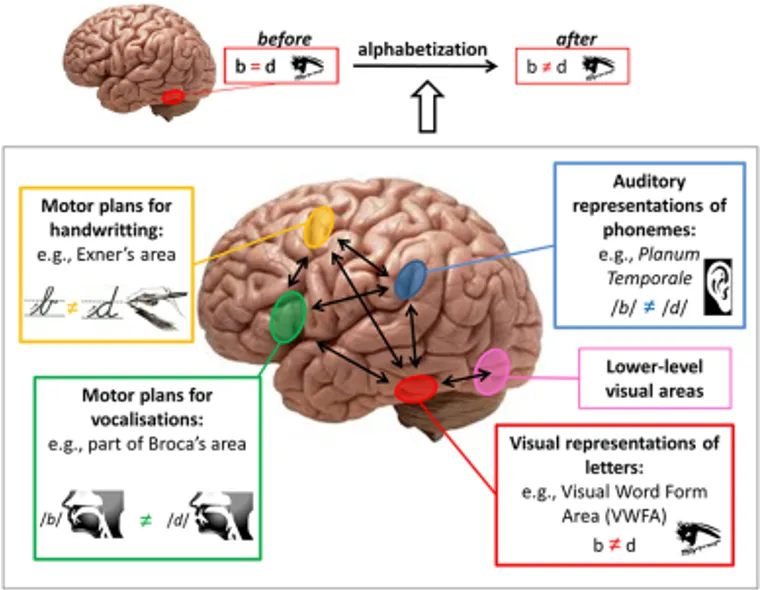
Brain pathways in literacy acquisition. Figure from Pegado, Nakamura & Hannagan (2014), Frontiers in Psychology. Sound, handwriting and speech regions all feed the visual word form area, which is how it eventually learns to keep b and d apart.
So what is dyslexia?
Dyslexia is a language-based learning difficulty. It sits in how the brain processes the sounds inside words, not in how the eyes take in their shapes. The joint statement of the American Academy of Pediatrics, the American Academy of Ophthalmology, AAPOS and AACO puts it plainly: vision problems can interfere with learning, but they do not cause dyslexia (AAP et al., 2009; reaffirmed 2014). Their technical report adds that children with dyslexia have the same visual function and ocular health as children without it, and that the treatment that works is structured, evidence-based reading instruction (Handler & Fierson, 2011).
We agree, and we say so to every family who walks in worried about dyslexia. We do not treat dyslexia, and vision therapy is not a substitute for reading instruction.
Where vision does fit in
The joint position of the American Academy of Optometry and the American Optometric Association is that vision problems can and often do interfere with learning, and that optometric care belongs alongside education and other therapies rather than in place of them (American Academy of Optometry & AOA, 1997). That is the frame we work in, and the data supports a modest, specific claim.
In a cohort of 5,822 children, four of every five with severe reading impairment had entirely normal ophthalmic function (Creavin et al., 2015) — vision is not the explanation for most struggling readers. At the same time, smaller clinical samples find focusing and tracking problems more often in children with dyslexia (any visual deficit in 79 percent versus 33 percent of typical readers), with the authors noting the clinical meaning is uncertain (Raghuram et al., 2018). Visual perception and motor coordination scores also track with both math and reading achievement in second through fourth graders after partially controlling for verbal ability and age, while the visual-motor integration score itself tracked with math and only trended with reading (Sortor & Kulp, 2003) — an association, not a cause.
We are equally careful about what treatment can promise. In CITT-ART, a randomized trial of 310 children with convergence insufficiency, reading comprehension improved 3.7 points with 16 weeks of office-based therapy and 3.8 points with placebo therapy (CITT-ART, 2019). Therapy makes near work more comfortable. It does not teach reading.
Laterality and directionality: our clinical lens
Beyond eye teaming and focusing, we look at laterality — a child’s internal sense of left and right on her own body — and directionality, the ability to project that sense onto the page. A letter is a directional object, so a child without a stable left-right map has no anchor for which way the loop on a b belongs. In our experience this travels with handwriting and math-column struggles, reversed number sequences and visual-spatial confusion. This is a developmental framework we use clinically; the pediatric-ophthalmology literature does not endorse it, so we offer it as our clinical perspective rather than settled evidence.
When reversals are worth evaluating
Our practical guidance to parents: reversals in kindergarten and first grade are expected. What earns a closer look is persistence past roughly age seven to eight, after a year or two of formal reading and writing instruction, especially with any of these:
- Confusing left and right on her own body, or on the page
- Skipping lines, losing her place, or using a finger long after peers stopped
- Handwriting that stays laborious and disorganized (more on that here)
- Headaches, eye rubbing, or avoiding reading altogether
- Reading that is accurate but slow and exhausting
The next step depends on the pattern. Reversals with slow, effortful decoding point toward a reading and language evaluation. Reversals with discomfort, place-losing and visual-spatial confusion point toward a developmental vision evaluation. Plenty of children need both. Our post on milestones for visual-spatial development lays out the typical sequence, and our overview of vision and learning covers the broader picture.
One caution: a school screening will not answer this question. The AOA’s pediatric guideline recommends a comprehensive eye examination before first grade and annually after, and reports that acuity screening alone missed about three-quarters of children later found to have binocular and eye-movement problems (AOA, 2017).
The short version
A backwards b in first grade is a brain doing exactly what it should: wrestling an ancient visual rule into a new shape. Give it time and practice. If the reversals are still there in third grade, or if they arrive with discomfort, avoidance or left-right confusion, that is the moment to look closer — not to panic, but to find out what is going on.
If that sounds like your child, we would be glad to take a look. Learn what is involved in a comprehensive eye and vision examination, or Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
At what age should letter reversals stop?
Reversals are common in five- and six-year-olds and fade as children get more reading and writing practice. Our clinical rule of thumb at Vision & Learning Center is that reversals still showing up frequently after a year or two of formal instruction, roughly age seven to eight, are worth a closer look, especially alongside left-right confusion, messy handwriting or slow, effortful reading.
Does writing letters backwards mean my child has dyslexia?
No. Dyslexia is a language-based difficulty with processing the sounds inside words. In one study that followed 130 five- and six-year-olds, children who later became weaker readers made more letter-writing errors overall but were no more likely than their peers to make reversal errors specifically, and reversal patterns did not predict reading skill nearly three years later.
Can vision therapy treat dyslexia?
No, and we do not present it that way. The American Academy of Pediatrics and the American Academy of Ophthalmology state that vision problems do not cause dyslexia and do not endorse vision therapy for learning disabilities. Our role is to find and treat vision problems that make reading uncomfortable, while structured literacy instruction does the work of teaching reading.
What is the difference between laterality and directionality?
Laterality is knowing left from right on your own body. Directionality is projecting that sense out onto the page, so you know which way a letter faces and which direction a line of print runs. Letters are directional objects, so a shaky sense of left and right leaves a child without an anchor for telling b from d.
Which letters do children reverse the most?
Left-facing characters such as d and J. Young children pick up on the fact that most letters and digits in our alphabet face right, so they tend to flip the ones that face left. In one study, left-facing forms were reversed 57 percent of the time versus 5 percent for right-facing forms.
Where This Information Comes From
- Treiman R, Gordon J, Boada R, Peterson RL, Pennington BF (2014). Statistical Learning, Letter Reversals, and Reading. Scientific Studies of Reading; 18(6):383-394. : In 130 five- and six-year-olds, left-facing letters were reversed far more often than right-facing ones; children who became weaker readers made more errors overall but were no more prone to reversals, and reversal patterns did not predict reading skill 2.75 years later.
- Fischer JP (2011). Mirror writing of digits and (capital) letters in the typically developing child. Cortex; 47(6):759-762. : Across 300 typically developing five- and six-year-olds, mirror writing of digits and capitals was common and followed an implicit right-facing rule.
- Pegado F, Nakamura K, Hannagan T (2014). How does literacy break mirror invariance in the visual system? Frontiers in Psychology; 5:703. : The primate visual system is mirror-invariant; literacy breaks that invariance for letters, and spontaneous mirror writing is a normal feature of early alphabetization.
- Dehaene S, Cohen L (2011). The unique role of the visual word form area in reading. Trends in Cognitive Sciences; 15(6):254-262. : Learning to read partially recycles a stretch of cortex that evolved for object and face recognition.
- Ahr E, Houde O, Borst G (2016). Inhibition of the mirror generalization process in reading in school-aged children. Journal of Experimental Child Psychology; 145:157-165. : First, third and fifth graders all had to actively inhibit mirror generalization to tell b from d, regardless of reading proficiency.
- American Academy of Pediatrics Section on Ophthalmology and Council on Children with Disabilities; American Academy of Ophthalmology; AAPOS; AACO (2009). Joint statement - Learning disabilities, dyslexia, and vision. Pediatrics; 124(2):837-844. : Dyslexia is language-based; vision problems can interfere with learning but do not cause dyslexia, and evidence does not support eye exercises, behavioral vision therapy or tinted lenses for learning disabilities.
- Handler SM, Fierson WM; AAP Section on Ophthalmology, Council on Children with Disabilities, AAO, AAPOS, AACO (2011). Learning disabilities, dyslexia, and vision. Pediatrics; 127(3):e818-e856. : Technical report - dyslexia stems from phonologic-processing deficits, children with dyslexia have the same visual function and ocular health as peers, and the effective treatment is evidence-based reading instruction.
- American Academy of Ophthalmology, American Academy of Pediatrics, AAPOS, AACO (2014). Joint Statement - Learning Disabilities, Dyslexia, and Vision, reaffirmed 2014. AAO Clinical Statement. : Reaffirms that vision problems are not the cause of primary dyslexia and that vision therapy is not endorsed for improving long-term educational performance.
- American Academy of Optometry; American Optometric Association (1997). Vision, learning and dyslexia. A joint organizational policy statement. Journal of the American Optometric Association; 68(5):284-286. : Optometric position - vision problems can and often do interfere with learning, and optometric care is one part of a multidisciplinary approach.
- Creavin AL, Lingam R, Steer C, Williams C (2015). Ophthalmic abnormalities and reading impairment. Pediatrics; 135(6):1057-1065. : In 5,822 children aged 7-9, four of every five with severe reading impairment had normal ophthalmic function and no association was found with convergence or accommodation.
- Raghuram A, Gowrisankaran S, Swanson E, Zurakowski D, Hunter DG, Waber DP (2018). Frequency of Visual Deficits in Children With Developmental Dyslexia. JAMA Ophthalmology; 136(10):1089-1095. : Any visual deficit was found in 79% of 29 children with dyslexia versus 33% of 33 typical readers; the authors state the cause and clinical relevance are uncertain.
- Sortor JM, Kulp MT (2003). Are the results of the Beery-Buktenica Developmental Test of Visual-Motor Integration and its subtests related to achievement test scores? Optometry and Vision Science; 80(11):758-763. : In 155 second- to fourth-graders, the visual perception and motor coordination subtests were significantly related to both math and reading achievement after partially controlling for verbal school ability and age; the visual-motor integration score itself was significantly related to math and showed only a trend for reading (p = 0.050).
- CITT-ART Investigator Group (2019). Effect of Vergence/Accommodative Therapy on Reading in Children with Convergence Insufficiency. Optometry and Vision Science; 96(11):836-849. : In 310 children, reading comprehension improved 3.7 points with 16 weeks of office-based therapy versus 3.8 points with placebo therapy.
- American Optometric Association (2017). Evidence-Based Clinical Practice Guideline - Comprehensive Pediatric Eye and Vision Examination. : Recommends a comprehensive eye examination before first grade and annually thereafter, and reports that acuity screening alone missed 75.5% of children later found to have binocular and oculomotor problems.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.