How Much Screen Time Is Too Much? A Parent's Guide

Screens are part of childhood now: schoolwork, video calls with grandparents, games, and the ten minutes of quiet a parent sometimes needs. The question families ask us is rarely “should my child use a screen?” It is “how much is too much?”
The honest answer has changed. Health bodies still give firm numbers for children under five; for older children the emphasis has moved from counting hours to noticing what screens displace. Here is where the guidance stands, what eye research does and does not show, and what we suggest to families at our four South Florida offices.
Key takeaways
- The World Health Organization gives real numbers only for children under 5: no screen time for infants under 1, no sedentary screen time at age 1, then no more than 1 hour a day at ages 2 to 4, less being better (WHO, 2019).
- The American Academy of Pediatrics has moved away from a fixed hourly rule toward its “5 Cs” — child, content, calm, crowding out and communication (Munzer et al., 2026).
- Screens and nearsightedness are linked, but weakly and inconsistently: pooled odds ratios run from 1.02, which was not statistically significant, to 1.77 (Lanca & Saw, 2020; Foreman et al., 2021).
- Time outdoors has stronger evidence for preventing nearsightedness from starting than any screen rule does (Xiong et al., 2017).
- Digital eye strain is common (Ccami-Bernal et al., 2024), and the randomized trials of blue-light glasses — all of them in adults — do not support them as the fix (Singh et al., 2023).
What the official guidance actually says
Under 5: the WHO gives real numbers
For the youngest children the guidance is specific. The WHO’s 2019 guidelines on physical activity, sedentary behaviour and sleep for children under 5 state that screen time is not recommended for infants under 1 year, and that sedentary screen time is not recommended for 1-year-olds. At ages 2 and 3 to 4, sedentary screen time should be no more than 1 hour a day, and less is better (WHO, 2019). When a small child is sitting still, WHO suggests reading and storytelling with a caregiver instead.
The AAP’s 2016 statement for this age group adds a point that matters more than any number. What a young child gets from a screen depends heavily on watching it with an adult who talks about it (AAP Council on Communications and Media, 2016).
Ages 6 to 18: there is no official hour limit
This surprises parents, because the “two-hour rule” is still repeated everywhere. AAP guidance now says plainly that “there isn’t enough evidence demonstrating a benefit from specific screen time limitation guidelines” and asks families to weigh the quality of media interactions, not just the quantity (AAP Center of Excellence). Its 2026 policy statement concludes that media and children cannot be addressed through usage time limits alone (Munzer et al., 2026).
What replaced the clock is the 5 Cs (AAP; HealthyChildren.org):
- Child — who is this particular child, and what draws them to certain media?
- Content — what are they actually watching or playing?
- Calm — is a screen their only strategy for settling big feelings or falling asleep?
- Crowding out — what is media pushing aside: sleep, movement, outdoor time, face-to-face play?
- Communication — do you talk about media early and often?
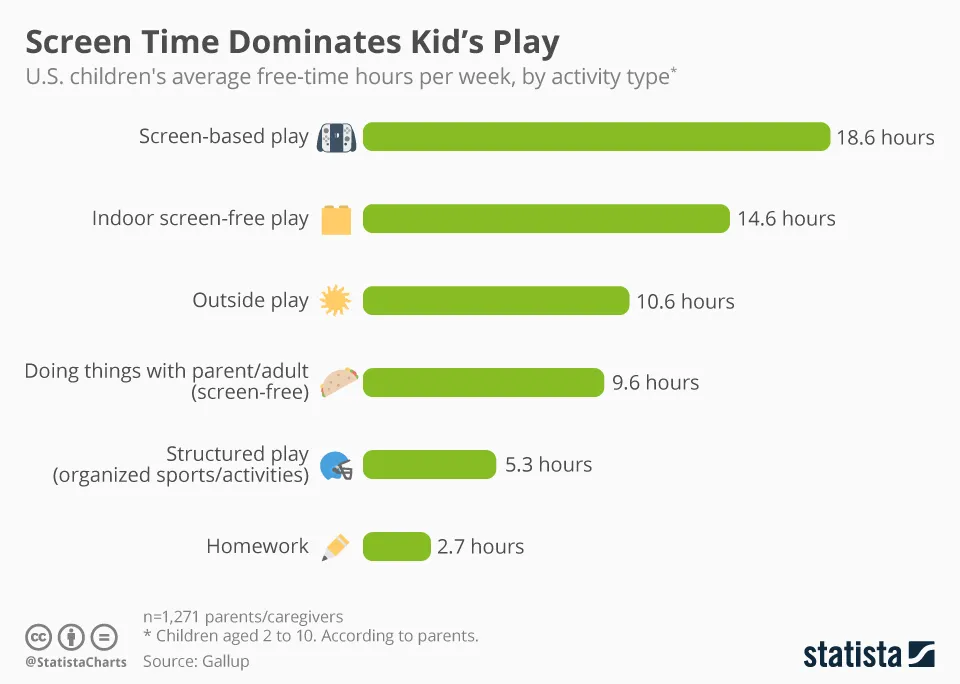
“Crowding out” is the one we find most useful, because it is measurable in a way that “too much” is not. In a 2017 Gallup survey of 1,271 US parents and caregivers, children aged 2 to 10 averaged 18.6 hours a week of screen-based play against 14.6 hours of indoor screen-free play (Gallup via Statista, 2017). That is a commercial survey rather than a peer-reviewed study, so treat it as a snapshot of how families spend time, not as a finding about eyes.
The practical tool for all of this is a written family media plan, which the AAP has recommended since 2016 (AAP Council on Communications and Media, 2016).
Screen time by age: guidance, and what we suggest

| Age | Published guidance | What we suggest for the eyes |
|---|---|---|
| Under 1 | WHO: screen time is not recommended | Face-to-face play, books, floor time. A video call with family is a conversation, not content |
| 1 year | WHO: sedentary screen time is not recommended | Same. Reading and storytelling for sitting-still time |
| 2 to 4 years | WHO: no more than 1 hour a day, less is better | Short sittings of roughly 15 to 20 minutes, with movement in between |
| 5 years | No WHO number past age 4 (the WHO guideline stops at under-5s); AAP: build a family media plan | Around an hour of recreational screen use, in short sittings, alongside plenty of outdoor play |
| 6 to 12 years | No official hour limit; AAP 5 Cs and a family media plan | Homework and recreation broken into 20 to 30 minute stretches; screens out of the bedroom |
| 13 to 18 years | No official hour limit; AAP: watch what media crowds out | 30 to 45 minute stretches, devices out of the bedroom overnight, protected sleep |
Read the right-hand column for what it is. Those session lengths are our clinical suggestion at Vision & Learning Center, based on what we see in the exam room. They are not a published guideline, and no trial has tested those specific numbers.
Why we ask about screens at an eye exam
Screens and nearsightedness (myopia)
Nearsightedness is becoming far more common: a pooled analysis of 145 studies estimated 22.9% of the world was myopic in 2000, projected to reach 49.8% by 2050 (Holden et al., 2016).
Screens get most of the blame, and the evidence is more modest than that. A 2020 systematic review covered 15 studies and 49,789 children, and seven of those studies reported an association. But when five of them (20,889 children) were pooled, the odds ratio came out at 1.02 (95% CI 0.96–1.08, p = 0.48) — not a statistically significant association (Lanca & Saw, 2020). A larger 2021 meta-analysis found a modest signal: an odds ratio of 1.26 for smart-device use alone, with the lower confidence bound touching 1.00, and 1.77 when computer use was included. Heterogeneity was high, and the authors concluded only that device exposure “might be associated” with myopia (Foreman et al., 2021).
Home confinement offered a natural experiment. Photoscreenings of 123,535 Chinese children aged 6 to 13 showed a myopic shift of about -0.3 D in 2020, and myopia prevalence at age 6 roughly tripled (21.5% versus 5.7%) (Wang et al., 2021). Two cautions: the screenings were non-cycloplegic, which the authors themselves list as a limitation, and confinement changed many things at once, including outdoor time, so the study does not isolate screens.
Our reading: near work of any kind is one plausible contributor among several, not the single lever parents are told it is. If your child is already nearsighted, our page on refractive error explains what that means for their vision, and we are glad to talk through management options at a visit.
Outdoor time is the better-evidenced lever
Here the evidence is clearer. Across 25 articles, time outdoors significantly reduced the risk of becoming myopic — a risk ratio of about 0.54 in clinical trials and 0.57 in cohort studies — and produced a smaller myopic shift over three years. Outdoor time did not slow progression in eyes that were already myopic (Xiong et al., 2017). So swapping indoor screen time for outdoor time is worth doing, and the benefit is mainly prevention in children who are not yet nearsighted.
Digital eye strain
Long sessions do produce real symptoms. A review estimates digital eye strain may affect 50% or more of computer users. It splits symptoms into two groups: accommodative and binocular stress (aching eyes, headache, blur, doubled print) and dry-eye symptoms (burning, grittiness, watering) (Sheppard & Wolffsohn, 2018). A 2024 meta-analysis of 103 studies and 66,577 participants put pooled prevalence at 69%, with extreme heterogeneity and questionnaire-only measurement (Ccami-Bernal et al., 2024). The drivers are focusing and eye-teaming demand plus a reduced blink rate (Rosenfield, 2011).
The familiar 20-20-20 rule — every 20 minutes, look at something 20 feet away for 20 seconds — is promoted by the American Optometric Association (Sheppard & Wolffsohn, 2018). The specific numbers have not held up in testing. When 30 participants did a 40-minute tablet reading task, 20-second breaks every 5, 10 or 20 minutes made no significant difference to symptoms, reading speed or accuracy (Johnson & Rosenfield, 2023). Breaks are a sensible, free habit — not a treatment for persistent eye strain. More detail is in our post on computer vision syndrome and on our computer vision syndrome service page.
What about blue-light glasses?
We are asked about these constantly. A 2023 Cochrane review pooled 17 randomized trials, all in adults. It found that blue-light-filtering lenses may not reduce eye-strain symptoms compared with standard lenses, probably have little or no effect on visual acuity, and gave indeterminate evidence for sleep (Singh et al., 2023). That review covers adults only, and no comparable trials have been run in children, so there is no evidence that these lenses help a child either. We do not recommend them for eye strain. We unpack the marketing in the hype and reality of blue light glasses.
Habits that are worth the effort

- Keep bedrooms screen-free overnight. Sleep is one of the things media most reliably crowds out (AAP, 2016).
- Write a family media plan with your children, so the rules are shared rather than imposed.
- Crowd activities back in: outdoor time, movement, sleep, in-person play. That is the AAP’s framing, and for eyes it is where the better evidence sits.
- Co-view with young children and talk about what is on the screen.
- Set up homework properly: comfortable viewing distance, screen slightly below eye level, glare controlled, and a reminder to blink.
- Model it. Children read your habits faster than your rules.
Our companion post on protecting your child’s eyes in the digital age has the day-to-day version.
When screen time is not the whole story
Sometimes screens are not causing the problem; they are revealing one. Watch for headaches after 15 or 20 minutes of near work, print that blurs or doubles, losing place while reading, covering one eye, or avoidance of reading and homework whether it is on paper or a screen. That last detail matters. In our clinical experience, strain that follows a child onto the printed page can point to a focusing or eye-teaming difficulty rather than to the device. That is our observation in the exam room rather than a research finding, and it is a reason to have the visual system checked.
These are worth checking properly, because a letter-chart screening measures how clearly your child sees at distance, not how comfortably their two eyes work together up close. Our symptom checklist is a starting point, not a diagnosis.
If your child’s screen habits are reasonable and they are still uncomfortable, tired or avoiding near work, we would be glad to take a proper look. See what is involved in our comprehensive and developmental evaluations, or Schedule an evaluation at our Boynton Beach or Boca Raton office.
Common Questions About This Topic
How much screen time is too much for a toddler or preschooler?
The World Health Organization is specific for this age group: no screen time for infants under 1, sedentary screen time not recommended at age 1, and no more than 1 hour a day at ages 2 through 4, with less being better. WHO suggests reading and storytelling with a caregiver as the alternative when a young child is sitting still.
Is there an official screen time limit for school-age children and teens?
No. The American Academy of Pediatrics states there is not enough evidence to support a specific hourly limit for older children, and its 2026 policy statement says media and children cannot be addressed through screen limits alone. The AAP now asks families to look at the child, the content, whether media is the only calming strategy, what it is crowding out, and how openly you talk about it.
Does screen time cause nearsightedness?
The link is real but weaker than headlines suggest. A 2020 systematic review identified 15 studies and pooled five of them, and that pooled odds ratio was 1.02 (95% CI 0.96–1.08, p = 0.48) — not a statistically significant association. A 2021 Lancet Digital Health meta-analysis found a modest association for smart devices (OR 1.26, lower bound touching 1.00) that rose to 1.77 when computer use was included, with high heterogeneity. Time spent outdoors has better evidence than screen time as a factor you can act on.
Do blue-light glasses protect my child's eyes from screens?
Probably not for eye strain, though the trial evidence is in adults rather than children. A 2023 Cochrane review of 17 randomized trials in adults found blue-light-filtering lenses may not reduce eye-strain symptoms compared with standard lenses and probably have little or no effect on visual acuity; no comparable trials have been done in children. An accurate prescription, a well-placed screen and regular breaks are better investments.
My child gets headaches doing homework on a laptop. Is that just too much screen time?
Not always. Digital eye strain has two parts: dry-eye irritation from reduced blinking, and focusing or eye-teaming effort. If headaches, blur, doubled print, losing your place or covering one eye happen with books as well as screens, that pattern is worth checking: it can reflect a focusing or eye-teaming problem that a comprehensive developmental vision evaluation can identify.
Where This Information Comes From
- World Health Organization (2019). To grow up healthy, children need to sit less and play more (news release accompanying the guidelines). : States that screen time is not recommended for infants under 1 year, that sedentary screen time is not recommended for 1-year-olds, and that sedentary screen time should be no more than 1 hour for ages 2 and 3-4, less being better.
- World Health Organization (2019). Guidelines on physical activity, sedentary behaviour and sleep for children under 5 years of age. : The underlying WHO guideline document covering how much of a 24-hour day children under 5 should spend active, asleep, and at most on screen-based sedentary activity.
- Munzer T, Parga-Belinkie J, Milkovich LM, et al.; AAP Council on Communications and Media (2026). Digital Ecosystems, Children, and Adolescents: Policy Statement. Pediatrics. : AAP policy statement using a socioecological framework and concluding that media and children cannot be addressed through individual child behaviour or usage time limits alone.
- American Academy of Pediatrics. The 5 Cs of Media Use (Center of Excellence on Social Media and Youth Mental Health). : Sets out the five components of AAP media guidance: child, content, calm, crowding out and communication.
- American Academy of Pediatrics. Kids and Screen Time: How to Use the 5 C's of Media Guidance. HealthyChildren.org. : Parent-facing AAP article describing the 5 C's as a replacement for the outdated 2-hour rule and defining each C.
- American Academy of Pediatrics. Screen Time Guidelines (Center of Excellence Q&A Portal). : States there is not enough evidence demonstrating a benefit from specific screen time limitation guidelines and directs families to quality of media interactions rather than quantity.
- AAP Council on Communications and Media (2016). Media Use in School-Aged Children and Adolescents. Pediatrics. : Reviews benefits and risks of media for ages 5-18, including effects on weight and sleep, and recommends a Family Media Use Plan tailored to the individual child.
- AAP Council on Communications and Media (2016). Media and Young Minds. Pediatrics. : Policy statement on media for children 0-5 addressing content and duration and emphasising the importance of parent-child shared media use.
- Gallup / Statista (2017). Screen Time Dominates Kid's Play (chart of US children's average free-time hours per week). : Gallup survey of 1,271 US parents and caregivers of children aged 2 to 10: 18.6 hours a week of screen-based play versus 14.6 hours of indoor screen-free play; a commercial survey reported through a chart aggregator, not a peer-reviewed study.
- Lanca C, Saw SM (2020). The association between digital screen time and myopia: A systematic review. Ophthalmic and Physiological Optics. : Across 15 studies of 49,789 children aged 3-19, seven reported an association; a meta-analysis of five of them (n = 20,889) gave a pooled odds ratio of 1.02 (95% CI 0.96-1.08; p = 0.48), so the screen-myopia evidence is mixed.
- Foreman J, Salim AT, Praveen A, et al. (2021). Association between digital smart device use and myopia: a systematic review and meta-analysis. Lancet Digital Health. : Smart device screen time was associated with myopia at OR 1.26 (95% CI 1.00-1.60), rising to 1.77 (1.28-2.45) when combined with computer use, with high heterogeneity.
- Xiong S, Sankaridurg P, Naduvilath T, et al. (2017). Time spent in outdoor activities in relation to myopia prevention and control: a meta-analysis and systematic review. Acta Ophthalmologica. : Outdoor time protected against incident myopia (risk ratio 0.536 in trials, 0.574 in cohorts) but did not slow progression in eyes that were already myopic.
- Holden BA, Fricke TR, Wilson DA, et al. (2016). Global Prevalence of Myopia and High Myopia and Temporal Trends from 2000 through 2050. Ophthalmology. : Myopia affected 22.9% of the world in 2000 and is projected to reach 49.8% by 2050, with high myopia rising from 2.7% to 9.8%.
- Wang J, Li Y, Musch DC, et al. (2021). Progression of Myopia in School-Aged Children After COVID-19 Home Confinement. JAMA Ophthalmology. : In photoscreenings of 123,535 children aged 6-13, 2020 showed a myopic shift of about -0.3 D and myopia prevalence at age 6 roughly tripled (21.5% vs 5.7%); non-cycloplegic screening, authors urge caution.
- Sheppard AL, Wolffsohn JS (2018). Digital eye strain: prevalence, measurement and amelioration. BMJ Open Ophthalmology. : Estimates digital eye strain may affect 50% or more of computer users, splits symptoms into accommodative/binocular and dry-eye types, and notes the AOA promotes the 20-20-20 rule.
- Ccami-Bernal F, Soriano-Moreno DR, Romero-Robles MA, et al. (2024). Prevalence of computer vision syndrome: A systematic review and meta-analysis. Journal of Optometry. : Pooled prevalence of computer vision syndrome was 69.0% across 103 studies and 66,577 participants, with extreme heterogeneity and self-report questionnaires.
- Rosenfield M (2011). Computer vision syndrome: a review of ocular causes and potential treatments. Ophthalmic and Physiological Optics. : Reports 64-90% of computer users experience visual symptoms, attributed mainly to oculomotor anomalies and dry eye from reduced blink rate and amplitude.
- Johnson S, Rosenfield M (2023). 20-20-20 Rule: Are These Numbers Justified? Optometry and Vision Science. : In 30 young subjects doing a 40-minute tablet reading task, 20-second breaks every 5, 10 or 20 minutes had no significant effect on symptoms (P = .70), reading speed (P = .93) or accuracy (P = .55).
- Singh S, Keller PR, Busija L, et al. (2023). Blue-light filtering spectacle lenses for visual performance, sleep, and macular health in adults. Cochrane Database of Systematic Reviews. : Across 17 randomized trials in adults, blue-light-filtering lenses may not reduce eye-strain symptoms and probably have little or no effect on visual acuity; the review is restricted to adults and there is no comparable trial evidence in children.
Care We Provide
More From the Blog
Wondering If This Sounds Like Your Family?
A developmental vision evaluation measures the skills a routine eye exam does not. Our team sees children and adults in Coconut Creek, Boynton Beach, Boca Raton and West Palm Beach.